

- Fluid 選擇:Crystalloids > colloids(1B);Buffered crystalloid > 0.9% NaCl(無 TBI 時,1B);嚴重 metabolic acidosis(pH <7.20)優先 IV bicarbonate 而非立即上 RRT(2C)。
- Liberal > restrictive fluid(elective major abdominal surgery 成人,24h 正平衡 1–2 kg,1B)— RELIEF trial 翻案。
- MAP 目標:>65 mmHg(重症成人高 AKI 風險,2C);對長期高血壓病人可考慮 higher target。
- 強烈反對 low-dose dopamine 保腎(1A)。
- Multicomponent kidney-protection strategy(Figure 9)對 cardiac surgery 等高風險成人 1B。
- Cardiac surgery 兩個新介入:IV amino acids(2A,PROTECTION trial 2024)+ Remote ischemic preconditioning(無 propofol 麻醉時 2B 成人 / 2D 兒童,Fig 10)。
- HRS-AKI:明確建議 vasoconstrictor(1C),首選 terlipressin 或 norepinephrine。
- TLS:高風險或已 TLS 用 rasburicase > allopurinol/febuxostat(除非 G6PD 缺乏,1B)。
- Diuretic:在臨床顯著 volume overload 用 diuretic(2B),且優於 extracorporeal fluid removal(無其他 RRT 適應症時 1C)。
3.1 Fluid Management — 拿掉 colloid、拿掉 NS 過量
| Recommendation | 內容 | Grade | 關鍵試驗 |
|---|---|---|---|
| 3.1.1 | Crystalloids > colloids(albumin、gelatin、starch)作為 volume expansion 初始選擇 | 1B | SAFE、CRYSTMAS、VISEP、6S、CHEST — starch 增加 AKI/RRT;albumin 無優勢 |
| 3.1.2 | Buffered crystalloid > 0.9% NaCl(無 TBI 時) | 1B | SPLIT、SMART、PLUS、BaSICS — buffered(lactated Ringer、Plasma-Lyte)降低 MAKE-30 |
| 3.1.3 | 嚴重 metabolic acidosis with acidemia(pH <7.20)→ IV bicarbonate 優於立即上 RRT(除非有其他 RRT 急性適應症) | 2C | BICAR-ICU(Lancet 2018)— stage 2-3 AKI + acidemia 用 bicarb 降 90-day mortality |
| 3.1.4 | Elective major abdominal surgery 成人 → Liberal IV fluid(24h 正平衡 1–2 kg) 優於 restrictive(net zero) | 1B | RELIEF(NEJM 2018)— restrictive 反增 AKI 8.6% vs 5.0% |
Practice Point 3.1.1:資源受限地區無法 IV → 用 oral rehydration(ISN 0by25 共識也支持)。
關鍵眉角
- Starch(HES)絕對禁忌:所有 starch 都被排除 — 不要再開 Voluven 給 critical care 病人
- NS 不是必死:SMART 與 PLUS 顯示 buffered 略優但差距不大;TBI 病人仍用 NS(避免低 osmolality 加重腦水腫)
- Liberal ≠ overload:1–2 kg 正平衡 ≈ 8–15 ml/kg/h 維持 + 失血補充;不是無上限 fluid resuscitation
- Albumin 在 HRS-AKI 仍有角色(見 3.6) — 這條只在「initial volume expansion」階段排除
3.2 Hemodynamic Management — MAP 目標、反對 dopamine、Multicomponent Strategy
MAP 目標
Recommendation 3.2.1(2C):重症成人高 AKI 風險或已 AKI → MAP 目標 >65 mmHg 指導 fluid + vasopressor。
Practice Point 3.2.3:對 chronic hypertension 病人可考慮 higher target(如 80–85 mmHg)以維持 renal perfusion;對 chronic hypotension(如老人、嚴重 cirrhosis)可考慮 lower target 避免 excessive vasopressor。
SEPSISPAM trial(NEJM 2014) 是這條建議的主要支撐:chronic HTN 病人 high MAP(80–85)vs standard(65–70)— high target 降 RRT 38.9% vs 31.7%。
反對 dopamine
Recommendation 3.2.2(1A):強烈反對使用 low-dose dopamine(renal dose)保腎。證據等級從 2012 的「不建議」升到 2026 的「強烈反對 1A」。長期累積 RCT 與 meta-analysis 都顯示無腎保護效果,反而增加心律不整、腸缺血。
Multicomponent kidney-protection strategy(Figure 9 — 核心圖)
Recommendation 3.2.3(1B):對由 clinical factors + biomarkers 識別出的高 AKI 風險 surgical 成人,使用 multicomponent 腎保護策略(Figure 9)。
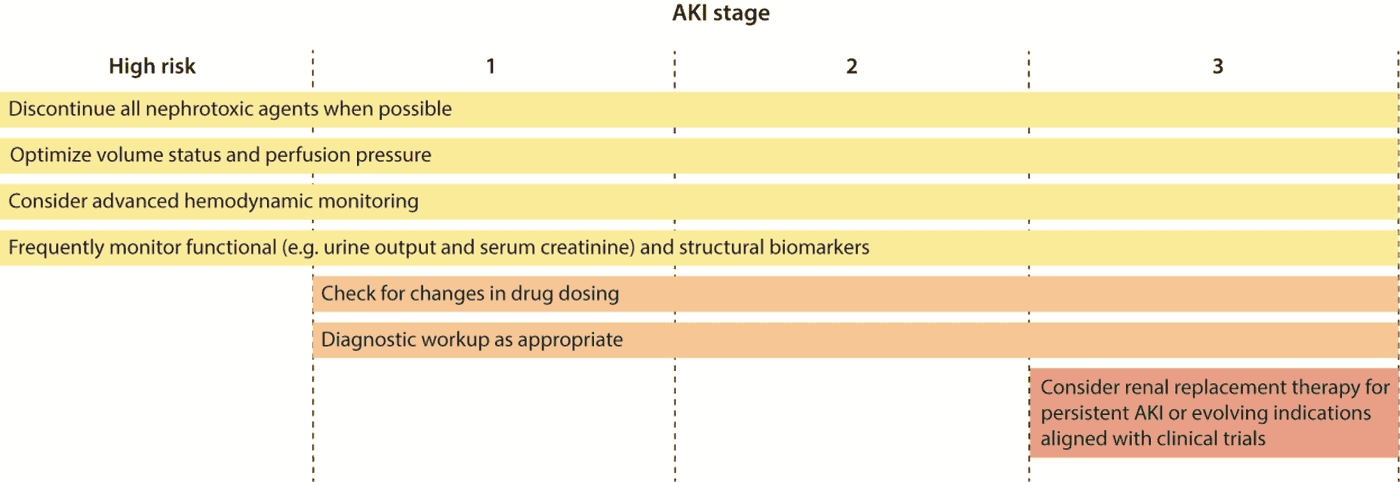
來源:KDIGO 2026 Clinical Practice Guideline for AKI and AKD (Public Review Draft, March 2026) — 個人教學使用,原始版權屬 KDIGO。
🧭 圖表逐步解析:Figure 9(Multicomponent kidney protection strategy)
這張圖在回答什麼問題:對 high-risk 或已 AKI 病人,系統性該做什麼 bundle?這是整份指引的 central illustration,把 PrevAKI / BigpAK 試驗中證實有效的介入打包成一份核對清單。
逐步走完(依 AKI stage 縱向 escalation):
- Discontinue all nephrotoxic agents when possible — NSAID、aminoglycoside、IV contrast、ACEi/ARB(情境性)
- Optimize volume status and perfusion pressure — fluid 與 vasopressor 並用,MAP >65(chronic HTN 可更高)
- Consider advanced hemodynamic monitoring — POCUS、TEE、PiCCO、Swan-Ganz
- Frequently monitor functional (UO + SCr) and structural biomarkers — 每 6–12h 重新評估
- Check for changes in drug dosing — KeGFR 計算、抗生素 / sedative dose 重新評估
- Diagnostic workup as appropriate — urine sediment、imaging、考慮 biopsy
- Consider RRT for persistent AKI or evolving indications aligned with clinical trials — 跟著 AKIKI / IDEAL-ICU / STARRT-AKI 的 deferred timing 原則(見 Article V)
容易踩雷的地方:
- 把這個 bundle 當「stage 3 才做」 — 圖的精髓是「high risk 就開始做」,不是 AKI 才介入。 PrevAKI/BigpAK 介入是 post-op 12h 內 biomarker(+) 就啟動,不等 SCr 上升。
- 「Discontinue nephrotoxin」當作 default 而不考慮替代方案 — 例如 HF 病人 ACEi 是 mortality benefit 藥,停了就要有再啟動計畫;NSAID 對 post-op pain 也有功能性角色。決策要 case-by-case。
- 「Optimize volume」變成 give more fluid — 「optimize」可能是 give 也可能是 remove。POCUS 與 dynamic parameter(PPV、SVV、PLR)是必要的;fluid overload 本身就是 AKI 與 mortality 風險。
- 不做 biomarker 重複 — Single biomarker 可能是 transient stress;連續上升才是真正進展訊號。bundle 包含「frequently monitor」是有原因的。
3.3 Diuretics — 用,但有規則
| Recommendation / PP | 內容 | Grade |
|---|---|---|
| 3.3.1 | 有 clinically significant volume overload 的 AKI/AKD 兒童與成人 → 用 diuretic | 2B |
| PP 3.3.1 | 初始用 intermittent IV bolus(不要 continuous infusion)— 較好監測反應、較少電解質波動 | PP |
| 3.3.2 | Diuretic 優於 extracorporeal fluid removal(無其他 RRT 急性適應症時,避免 unnecessary RRT) | 1C |
劑量階梯(Table 22 改寫):
| 階段 | 策略 |
|---|---|
| 1. 試探 | Furosemide 20–40 mg IV bolus;或 home dose 1–2.5× |
| 2. 倍增 | 若 1h 內 UO <100 ml → double 劑量(max 200–400 mg) |
| 3. Combination | 仍無反應 → 加 thiazide(metolazone 5–10 mg PO / chlorothiazide 250–500 mg IV)— sequential nephron blockade |
| 4. Continuous infusion | 多次 bolus 失敗才考慮,避免 over-diuresis |
| 5. 評估 ultrafiltration(UF) | 3-step 都失敗 + 持續 fluid overload → 考慮 RRT/UF(但 KDIGO 2026 強調此為 last resort,不是 first line) |
3.4 Glucose Control
Practice Point 3.4.1:重症兒童與成人 AKI/AKD → 目標 plasma glucose 140–180 mg/dl(7.8–10 mmol/l),不要更積極(如 80–110 mg/dl)。NICE-SUGAR 與 Leuven trials 已確立此 target。
3.5 Cardiac Surgery-Associated AKI(CSA-AKI)— 兩個新介入
3.5.1 IV Amino Acids 預防 — PROTECTION trial
Recommendation 3.5.1(2A):無 advanced CKD 的成人 cardiac surgery → 預防性 IV amino acid infusion 可預防 AKI。
PROTECTION trial(JAMA 2024):3,511 名 elective cardiac surgery 病人,randomized to amino acid(2 g/kg/day × 3 day)vs placebo — AKI(任何 stage)26.9% vs 31.7%,stage 3 AKI 1.6% vs 3.0%。NNT ~22。機轉:amino acid 經 hyper-filtration 增加 GFR、提升 renal reserve、改善 medullary oxygenation。
3.5.2 Remote Ischemic Preconditioning (RIPC)
Recommendation 3.5.2:高 AKI 風險 cardiac surgery 病人,無 propofol 麻醉時 RIPC(成人 2B、兒童 2D)。
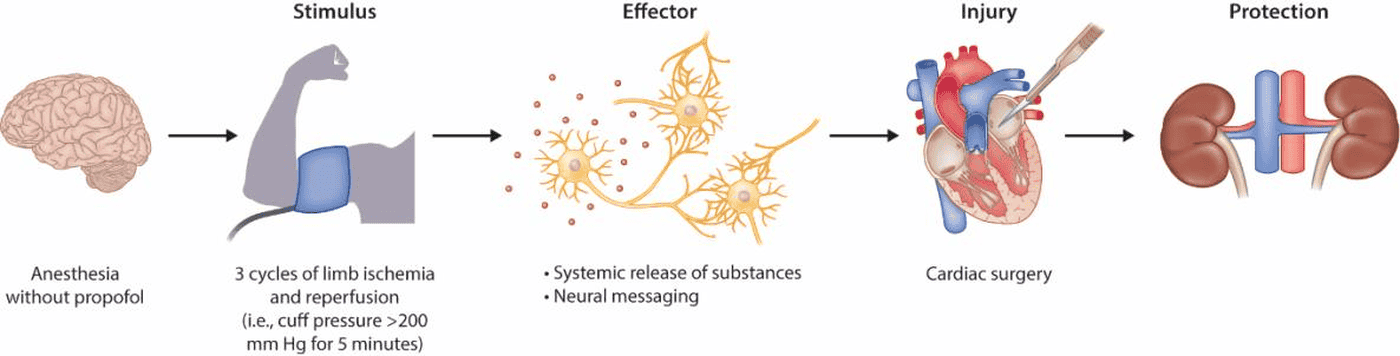
來源:KDIGO 2026 Clinical Practice Guideline for AKI and AKD (Public Review Draft, March 2026) — 個人教學使用,原始版權屬 KDIGO。
機轉:在 induction 後、surgery 前,於遠端肢體(通常上肢)做反覆 ischemic episode(cuff inflate 至 200 mmHg × 5 分鐘 + 5 分鐘 release,× 3–4 次循環)→ 釋放循環中的 protective factor → 全身(含腎臟)organ tolerance 提升。
關鍵眉角:propofol 會抵銷 RIPC — Eur Heart J 與多項 meta-analysis 確認。所以這個建議綁定「無 propofol 麻醉」前提。實務上:用 volatile anesthetic(sevoflurane / isoflurane)的中心可以做 RIPC;全靜脈 propofol-based TIVA 中心做了等於白做。
3.6 Hepatorenal Syndrome-Associated AKI(HRS-AKI)
Recommendation 3.6.1(1C):成人 HRS-AKI → 使用 vasoconstrictor 治療。
Practice Point 3.6.1:首選 terlipressin 或 norepinephrine;無這兩者可用時,midodrine + octreotide 作為 alternative。
關鍵試驗:CONFIRM(NEJM 2021) — terlipressin(+ albumin)vs placebo(+ albumin),HRS-AKI reversal 32% vs 17%(HR 1.91)。注意:terlipressin 在 ACLF grade 3 或 baseline SCr >5 mg/dl 的病人 respiratory failure 風險升高,需謹慎。Norepinephrine 在 ICU 環境是合理替代。
標準劑量:
- Terlipressin:1–2 mg IV bolus q4–6h,或 continuous infusion 2–12 mg/day;持續到 HRS reversal 或 14 天
- Norepinephrine:0.5–3 mg/h IV,目標 MAP 上升 ≥10 mmHg
- Albumin:1 g/kg day 1(max 100 g),之後 20–40 g/day
3.7 Tumor Lysis Syndrome (TLS)-Associated AKI
Practice Point 3.7.1:高風險或已 TLS 的兒童成人 → 用 IV crystalloid volume expansion,但不要 urinary alkalinization(之前用 bicarb 鹼化尿液現已不建議 — 反而促進 calcium phosphate 沉積)。
Recommendation 3.7.1(1B):高 TLS 風險或已 TLS → rasburicase 優於 allopurinol / febuxostat,除非 G6PD 缺乏(rasburicase 會誘發溶血)。
機轉:rasburicase(recombinant urate oxidase)直接分解 uric acid 為 allantoin(可溶),數小時內降 uric acid >90%;allopurinol 與 febuxostat 只阻擋新合成、降速慢。
Practice Point 3.7.2:低風險、無法取得 rasburicase、或禁忌時 → xanthine oxidase inhibitor(allopurinol 或 febuxostat)。
3.8 Rhabdomyolysis / Hemolysis-Associated AKI
Practice Point 3.8.1:用 IV crystalloid 大量補液(早期、積極)是基石。Target:UO ≥200 ml/h(成人)/3 ml/kg/h(兒童)。
過去的「鹼化尿液 + mannitol」做法已無強證據支持,不再常規建議;嚴重 hyperkalemia / refractory acidosis / oliguria 仍需 RRT。
3.9 Nutrition in AKI/AKD
| PP | 建議 |
|---|---|
| 3.9.1 | 優先 enteral nutrition(兒童 + 成人) |
| 3.9.2 | 不要為了延後 RRT 而限制 protein intake |
| 3.9.3 | 避免成人 excessive protein intake(一般 1.2–1.5 g/kg/day,CRRT 上 1.5–2.0 g/kg/day) |
| 3.9.4 | Caloric target 不因 AKI 改變(除非上 RRT) |
| 3.9.5 | CRRT 中要常規補 water-soluble vitamins(thiamine、folate、B6、C)與 micronutrients(會被 dialysate 洗掉) |
| 3.12.2.1 | 兒童 AKI 維持 age-recommended protein target;CRRT 中至少 2.5 g/kg/day |
3.10 Pregnancy AKI
Practice Point 3.10.1:孕婦 AKI/AKD 需要 specialty-specific 治療,包含考慮 early delivery(HELLP、pre-eclampsia、AFLP、acute fatty liver of pregnancy)。Corticosteroid 用於 HELLP 並未證實腎保護(Table S117)。
3.11 Environmental / Tropical AKI
- PP 3.11.1:熱帶/亞熱帶地區 → 評估 region-specific 感染性與環境性原因(dengue、leptospirosis、malaria、scrub typhus、snake bite)並早期啟動 disease-specific therapy
- PP 3.11.2:地區性傳統醫藥/毒物使用區 → 把 traditional medicine 列入 differential
- PP 3.11.3:高溫暴露後 AKI → 考慮 heat-related kidney injury(Mesoamerican nephropathy 等)
3.12 兒童專用
- 用 age-appropriate BP target 指導 hemodynamic management
- Theophylline 單一劑量於 severe perinatal asphyxia 預防 AKI(1A) — 罕見的 1A 級兒童建議
- 反對 inhaled NO 常規預防 pediatric cardiac surgery AKI(無 PAH/RV dysfunction 的低複雜度 CHD 手術,1C)
- Cardiac surgery:把 IV amino acid 與 RIPC 列入 high-risk 病人的 routine。PROTECTION trial NNT 22 對 high-risk 群體有意義;RIPC 跟麻醉科溝通「avoid propofol」是先決條件。
- 術後 12h 內 [TIMP2]*[IGFBP7](biomarker bundle)→ >0.3 即啟動 Figure 9 全套 bundle(不等 SCr 上升)。
- CCU 病人的 fluid 選擇:buffered crystalloid(Lactated Ringer 或 Plasma-Lyte)優於 NS;HF acute decompensation 仍用 IV diuretic(bolus > infusion),不要直接上 UF。
- HF / cardiorenal 病人的 diuretic strategy:3 步驟階梯(試探 → bolus 倍增 → metolazone combination),無效才考慮 CRRT/UF — 跟 KDIGO 3.3.2 一致。
- HRS-AKI 在 advanced HF 病人(liver congestion from RV failure / Fontan):vasoconstrictor 選 norepinephrine 而非 terlipressin(後者 vasoconstriction 可能加重 cardiogenic shock)。Albumin 1 g/kg + diuretic 仍是基礎。
- MAP target:CCU/cardiogenic shock 病人若有 chronic HTN,考慮 MAP 80–85(SEPSISPAM 概念延伸)— 但要在 vasopressor 安全範圍內,且避免 over-vasoconstriction 加重 cardiogenic shock。
- SGLT2i / RASi 在 AKI 急性期:急性 hospitalization 暫停符合 sick day rules;resolution 後 7–14 天內重啟(除非新發 hyperkalemia 或 SCr >30%)— Chapter 6 詳述。
📋 Chapter 3 關鍵 Recommendations 總表
| # | Recommendation | Grade |
|---|---|---|
| 3.1.1 | Crystalloids > colloids(volume expansion 初始) | 1B |
| 3.1.2 | Buffered crystalloid > 0.9% NaCl(無 TBI) | 1B |
| 3.1.3 | 嚴重 acidemia (pH<7.20) → IV bicarbonate > RRT | 2C |
| 3.1.4 | Elective major abdominal surgery → liberal fluid(24h +1–2 kg) | 1B |
| 3.2.1 | MAP >65 mmHg(重症高風險 AKI 成人) | 2C |
| 3.2.2 | 反對低劑量 dopamine 保腎 | 1A |
| 3.2.3 | 高 AKI 風險 surgical 成人 → multicomponent kidney-protection bundle(Fig 9) | 1B |
| 3.3.1 | 顯著 volume overload AKI/AKD → diuretic | 2B |
| 3.3.2 | Diuretic > extracorporeal fluid removal(無其他 RRT 適應症時) | 1C |
| 3.5.1 | Cardiac surgery 成人(無 advanced CKD)→ prophylactic IV amino acids 預防 AKI | 2A |
| 3.5.2 | RIPC 預防 cardiac surgery-associated AKI(無 propofol 麻醉) | 2B 成人 / 2D 兒童 |
| 3.6.1 | HRS-AKI 用 vasoconstrictor | 1C |
| 3.7.1 | 高 TLS 風險或已 TLS → rasburicase > allopurinol/febuxostat(除非 G6PD 缺乏) | 1B |
| 3.12.4.1 | Neonates 嚴重 perinatal asphyxia 單一劑量 theophylline 預防 AKI | 1A |
| 3.12.5.1 | 反對常規 inhaled NO 預防低複雜度 pediatric CHD 手術 AKI | 1C |
- Buffered crystalloid 取代 NS(除 TBI);starch 禁用;abdominal surgery 改 liberal。
- MAP >65 + 反對 dopamine 1A;chronic HTN 可考慮更高。
- Figure 9 是 central illustration:high risk 就啟動 bundle,不是等 stage 3。
- Cardiac surgery 兩個新介入:IV amino acid(PROTECTION)+ RIPC(無 propofol)。
- HRS:terlipressin 或 norepinephrine + albumin;TLS:rasburicase 首選(非 G6PD 缺乏)。
📖 References(精選)
- KDIGO 2026 AKI/AKD Public Review Draft — Chapter 3.
- Semler MW, Self WH, Wanderer JP, et al. Balanced Crystalloids versus Saline in Critically Ill Adults (SMART). N Engl J Med 2018;378:829–839. PMID: 29485925.
- Finfer S, Micallef S, Hammond N, et al. Balanced Multielectrolyte Solution versus Saline in Critically Ill Adults (PLUS). N Engl J Med 2022;386:815–826. PMID: 35041780.
- Myles PS, Bellomo R, Corcoran T, et al. Restrictive versus Liberal Fluid Therapy for Major Abdominal Surgery (RELIEF). N Engl J Med 2018;378:2263–2274. PMID: 29742967.
- Asfar P, Meziani F, Hamel JF, et al. High versus Low Blood-Pressure Target in Septic Shock (SEPSISPAM). N Engl J Med 2014;370:1583–1593. PMID: 24635770.
- Landoni G, Monaco F, Ti LK, et al. A Randomized Trial of Intravenous Amino Acids for Kidney Protection (PROTECTION). N Engl J Med 2024;391:687–698. PMID: 38804512.
- Zarbock A, Schmidt C, Van Aken H, et al. Effect of remote ischemic preconditioning on kidney injury among high-risk patients undergoing cardiac surgery: a randomized clinical trial. JAMA 2015;313:2133–41. PMID: 26025377.
- Wong F, Pappas SC, Curry MP, et al. Terlipressin plus Albumin for the Treatment of Type 1 Hepatorenal Syndrome (CONFIRM). N Engl J Med 2021;384:818–828. PMID: 33657294.
- Jaber S, Paugam C, Futier E, et al. Sodium bicarbonate therapy for patients with severe metabolic acidaemia in the intensive care unit (BICAR-ICU). Lancet 2018;392:31–40. PMID: 29910040.
本文以教學為目的整理 KDIGO 2026 AKI/AKD Clinical Practice Guideline(Public Review Draft),所有原文 Figure 之版權屬 KDIGO;商業使用請洽 KDIGO 取得授權。最終版指引發布前,本文內容可能與 final guideline 有差異,臨床決策請以 KDIGO 屆時公告為準。
