

🎯 Take-home Message
- Valvular HD(Fig 20):總圖列 4 個瓣膜的 stenosis / regurgitation 風險 + red flag。Mitral stenosis(rheumatic)+ 嚴重 AS 是 mWHO IV;Severe regurgitation 多在 well-tolerated 範圍但要密切評估 LV function。
- Mechanical Heart Valve(MHV)抗凝決策(Fig 21):依 high-risk vs low-risk valve thrombosis 與 trimester 切。VKA dose ≤5 mg/day 可整孕期繼續;>5 mg/day 第一 trimester 需轉 LMWH(嚴密 anti-Xa)。最後 2 週前一定轉 LMWH/UFH 等待 delivery。
- Acute HF / 心因性休克(Fig 22):嚴格分流(severe HF/CS vs no severe);PPCM 特殊路徑 — bromocriptine + prophylactic anticoagulation;LMWH 預防 thromboembolic events;MCS(VA-ECMO / LVAD)作 bridge to recovery / transplant。
- Cardio-oncology + pregnancy:PHT + cardio-onco team 共管 I C;不可因為孕期延誤 essential cardiotoxic 治療,依 trimester 與藥物個別調整。
- Heart transplantation:產後再懷孕 → postpone ≥1 年 after Tx I C;immunosuppression level 4-2-1 週監測 I C;mycophenolate 強制 pre-conception 換 azathioprine。
💗 §12.5 Valvular Heart Disease — Figure 20 速覽
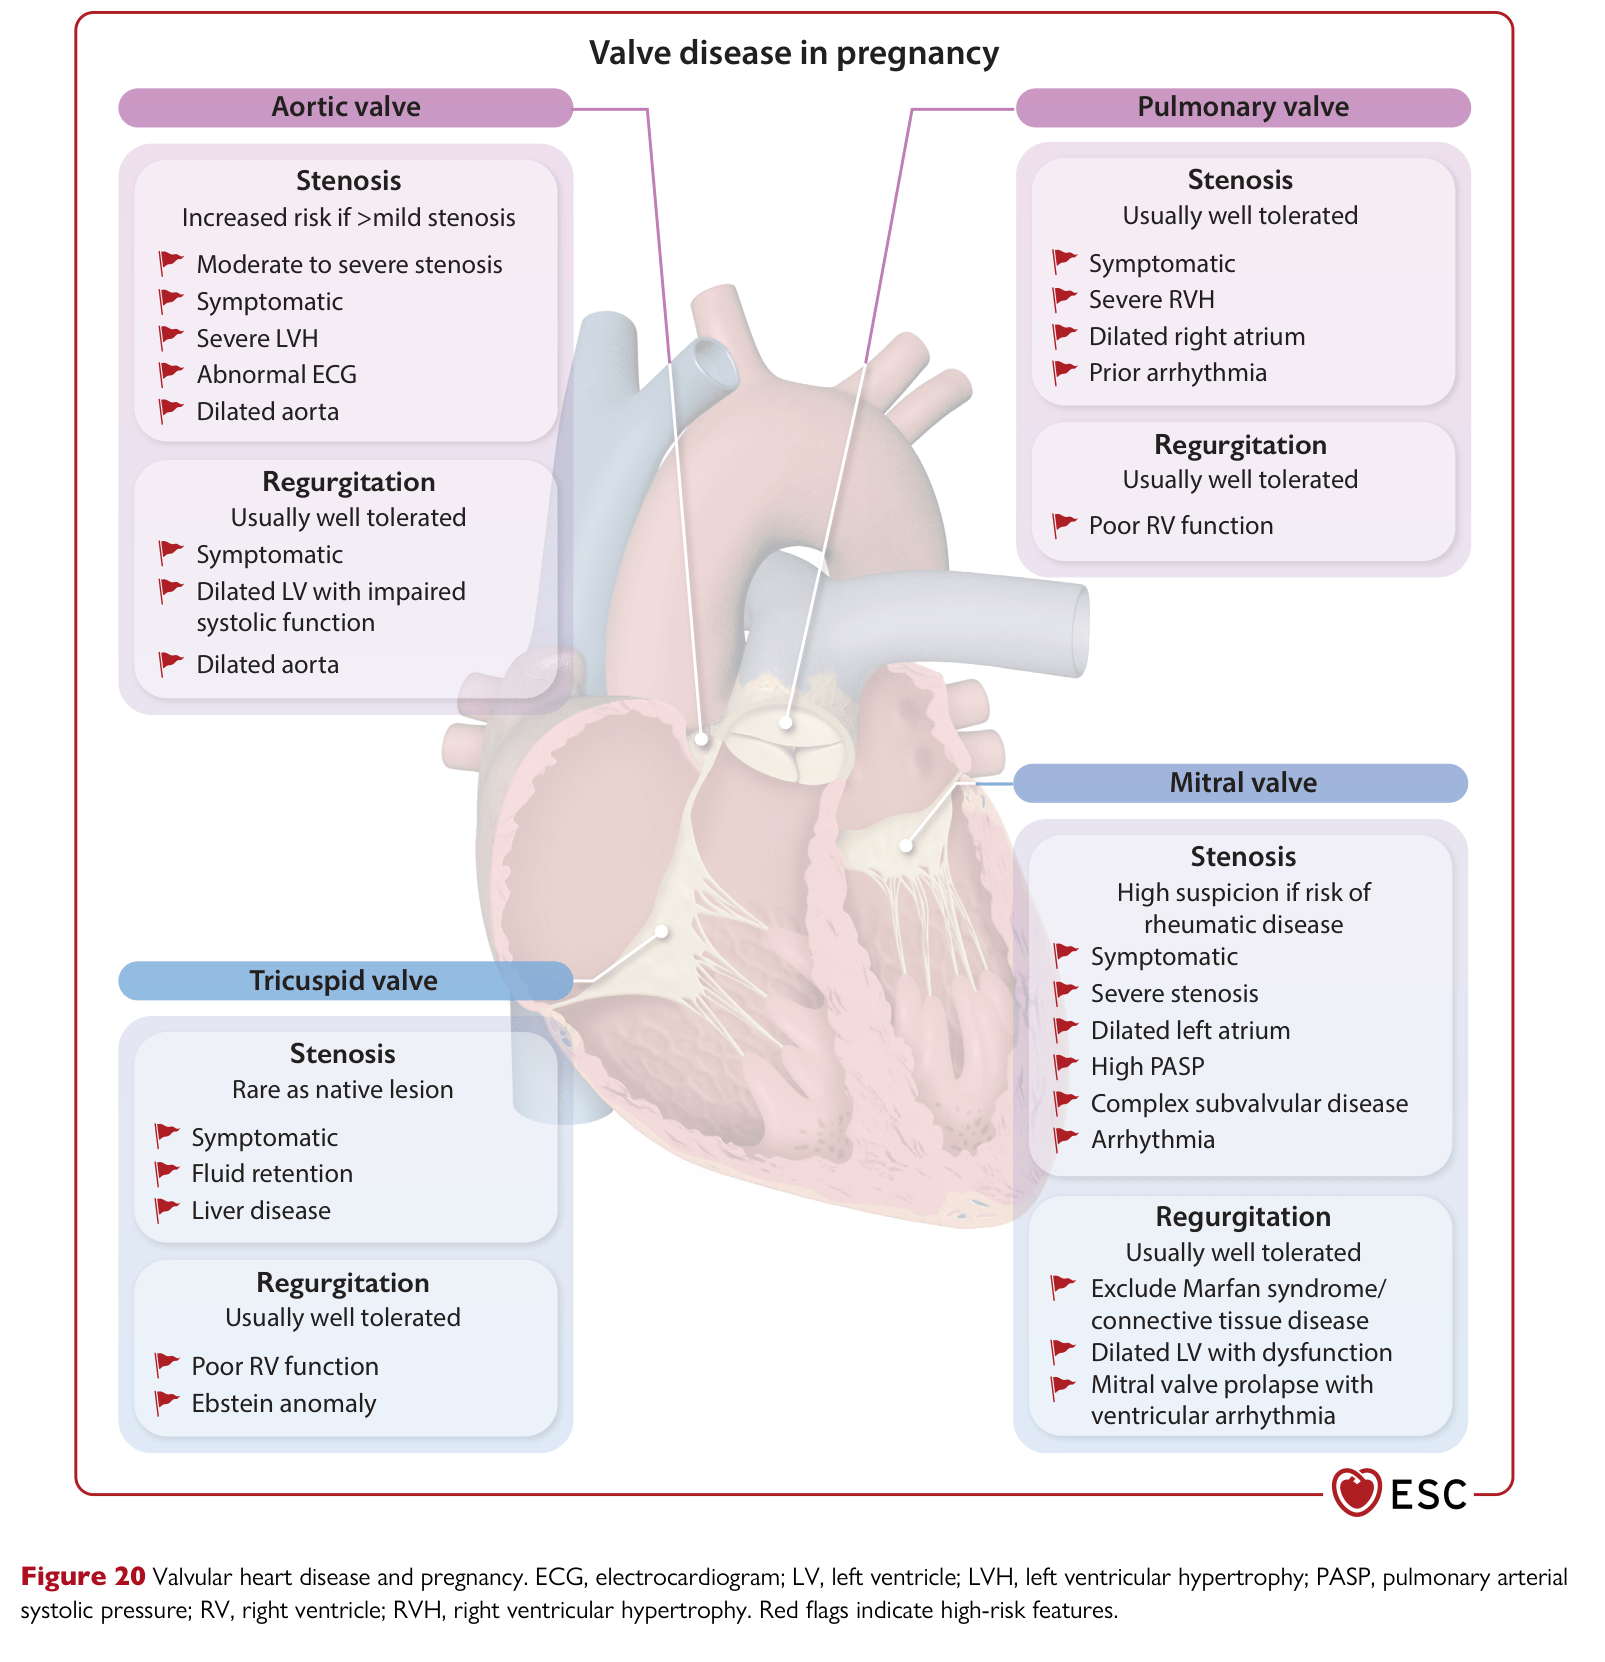
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 20
這張圖在回答什麼問題:各瓣膜病在妊娠中的風險樣態(red flags),一張圖看完。
四個瓣膜 × stenosis / regurgitation 的結構:
| 瓣膜 | Stenosis 重點 | Regurgitation 重點 |
|---|---|---|
| Aortic valve | Increased risk if >mild stenosis;moderate to severe stenosis;symptomatic;severe LVH;abnormal ECG;dilated aorta | Usually well tolerated;symptomatic;dilated LV with impaired systolic function;dilated aorta |
| Pulmonary valve | Stenosis usually well tolerated;symptomatic;severe RVH;dilated right atrium;prior intervention | Usually well tolerated;poor RV function |
| Tricuspid valve | Stenosis rare as native lesion;symptomatic;fluid retention;liver disease | Usually well tolerated;poor RV function;Ebstein anomaly |
| Mitral valve | High suspicion if risk of rheumatic disease;symptomatic;severe stenosis;dilated left atrium;high PASP;complex subvalvular disease;arrhythmia | Usually well tolerated;exclude Marfan syndrome / connective tissue disease;dilated LV with dysfunction;mitral valve prolapse with ventricular arrhythmia |
實務意涵:
- Mitral stenosis(rheumatic)是孕期最棘手的瓣膜疾病:volume + HR 上升 → PAH 急性惡化。MS valve area <1.5 cm² = mWHO IV;<1.0 cm² 強烈 caution。
- Aortic stenosis:severe symptomatic AS(Vmax ≥4 m/s 或 mean gradient ≥40 mmHg + symptoms)= mWHO IV;asymptomatic moderate-severe AS = mWHO II-III。
- Severe regurgitation(AR、MR、TR):多數 well-tolerated,因 SVR 下降 → afterload 降。但 dilated LV with impaired systolic function 或 Marfan AR 是 caution flag。
- Ebstein ‘s anomaly with severe TR:可 well-tolerated 妊娠,注意 right HF 與 SVT。
瓣膜病 acute management 原則
- Severe symptomatic MS:beta-blocker(降 HR、延長 LV filling)+ diuretic(降 PCWP);不行 → percutaneous mitral valvotomy(Class IIa,2nd trimester)。
- Severe AS with HF:避免 vasodilators(會 worsen LVOT pressure gradient);preload 用 diuretic 謹慎;severe symptomatic → balloon valvuloplasty(IIa)或 valve surgery(last resort, IIa C — 只當其他選項失敗,胎兒風險 20-30%)。
- Severe AR / MR with HF:diuretic、digoxin、hydralazine(無 ACEi/ARB),urgent surgery 通常可推遲到產後。
🩸 §12.5 MHV 抗凝決策 — Figure 21
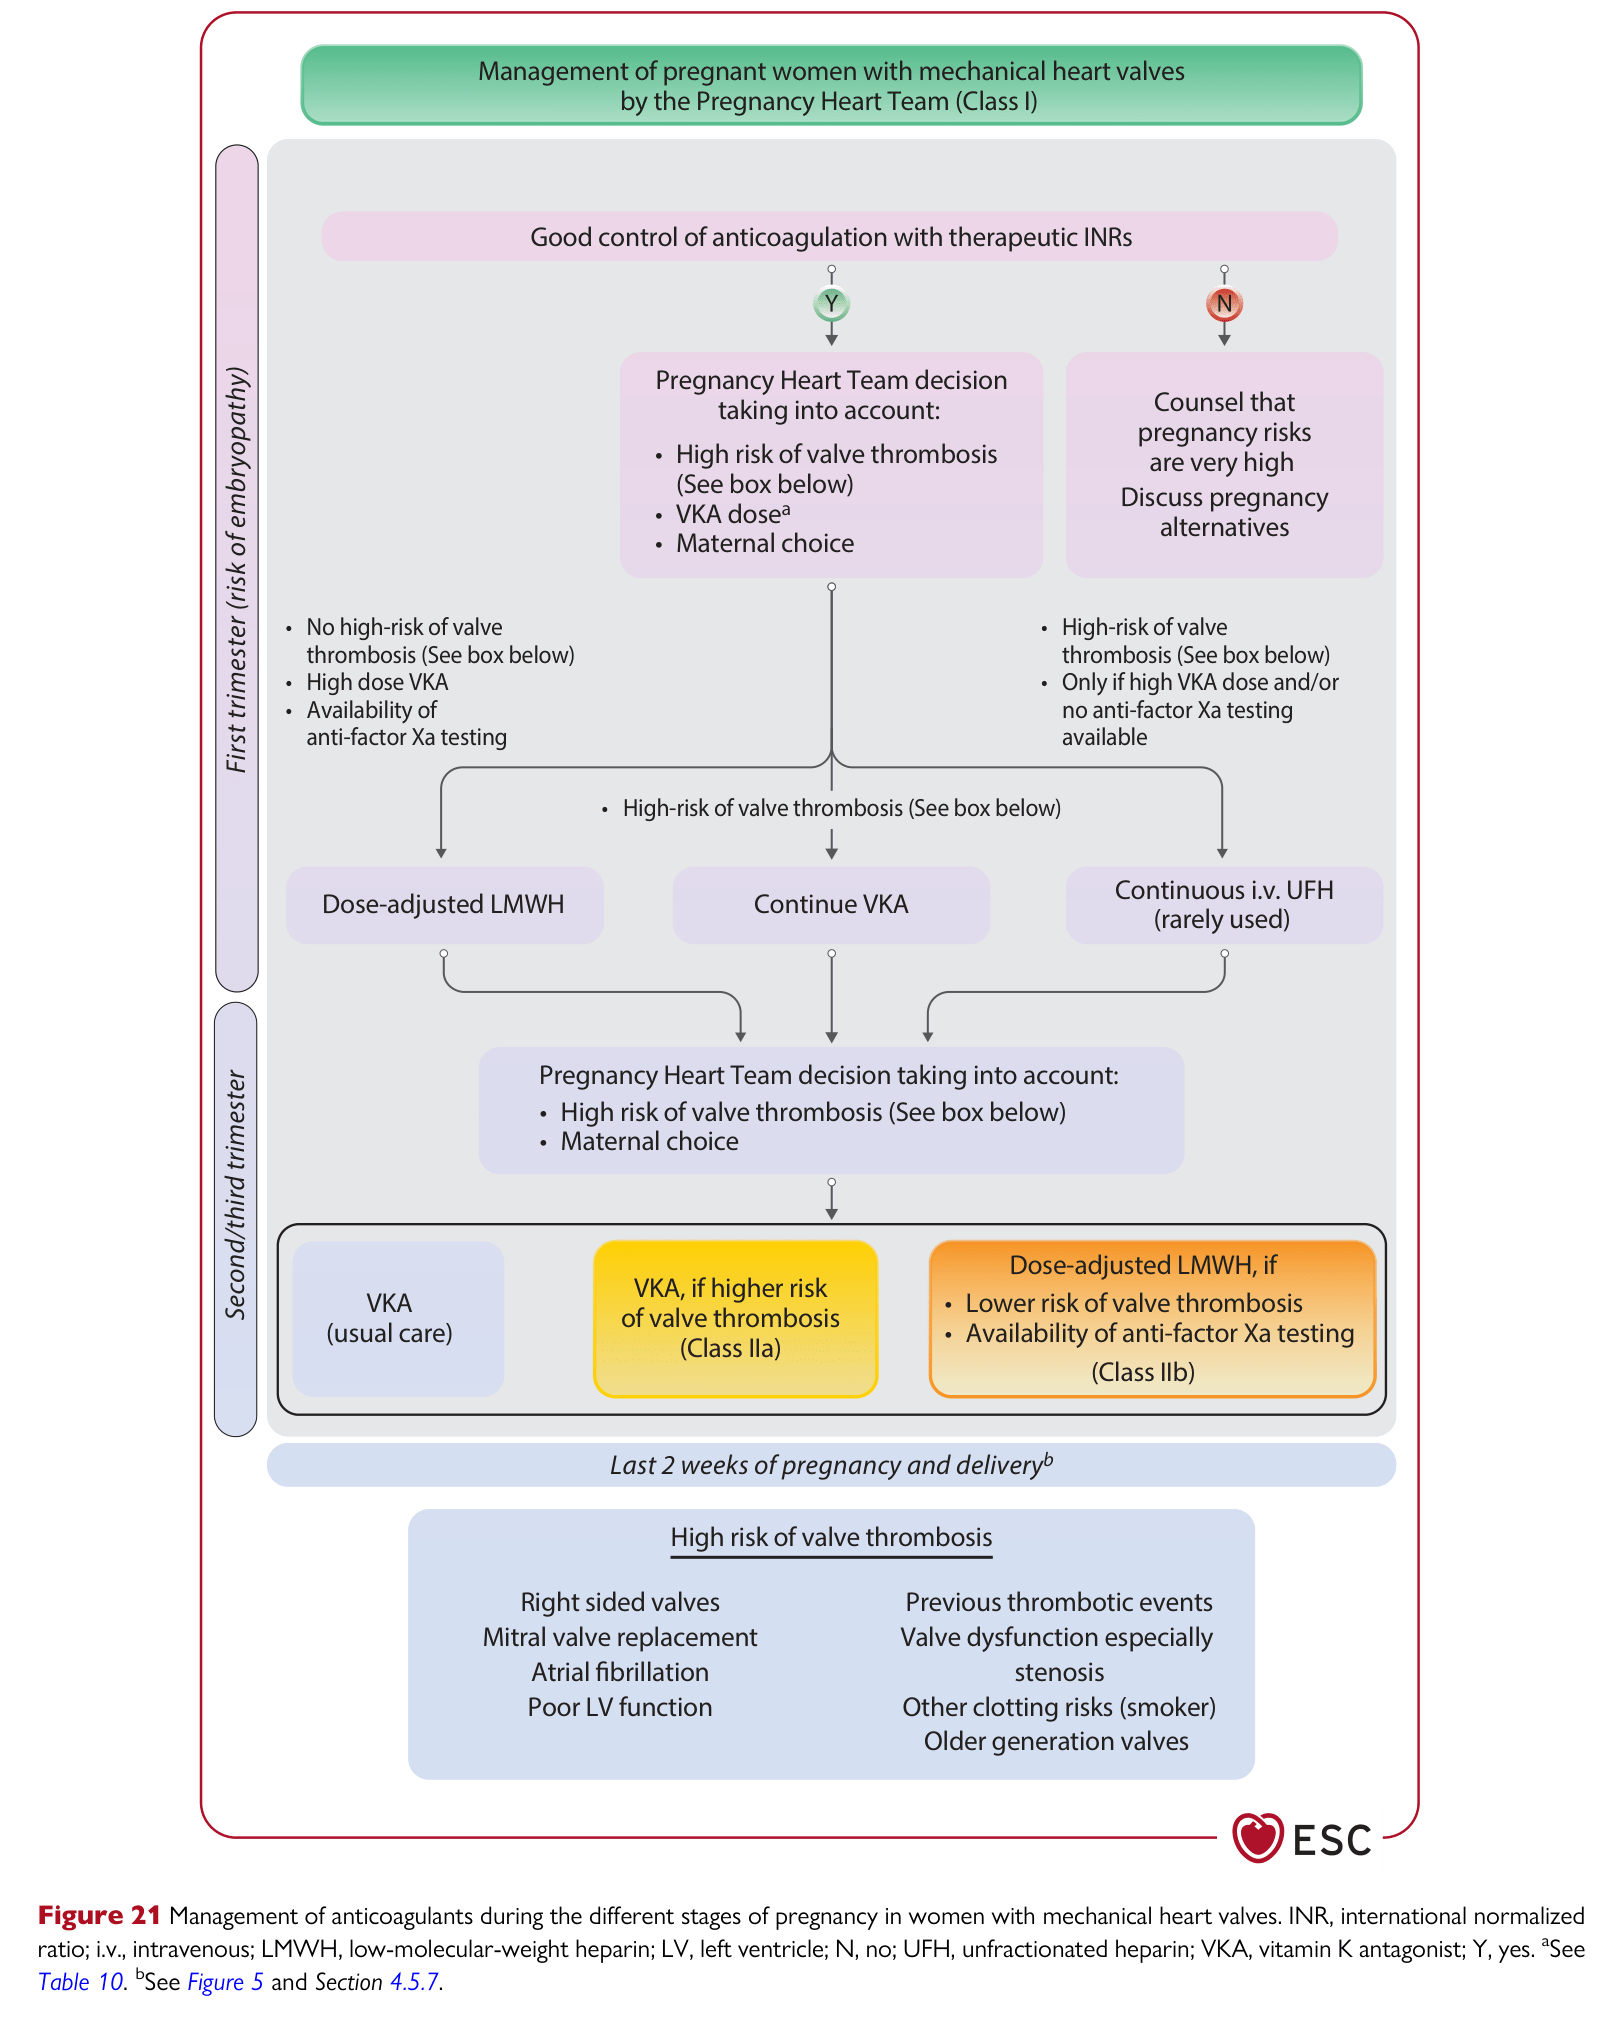
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 21
這張圖在回答什麼問題:MHV 孕婦怎麼跨三孕期 + delivery 切換抗凝?依「valve thrombosis 高 vs 低風險」分流。
Step 1:Management of pregnant women with mechanical heart valves by the Pregnancy Heart Team (Class I)。
Step 2:Good control of anticoagulation with therapeutic INRs。
Step 3 — Pregnancy Heart Team decision taking into account:
- High risk of valve thrombosis(See box below)
- VKA dosea(<5 mg/day vs >5 mg/day warfarin equivalent)
- Maternal choice
Step 4:Counsel that pregnancy risks are very high;discuss pregnancy alternatives。
Step 5 — First trimester(risk of embryopathy)分流:
- No high-risk of valve thrombosis(See box below):
- High dose VKA(>5 mg/day)→ Switch to Dose-adjusted LMWH
- Availability of anti-factor Xa testing
- High dose VKA(>5 mg/day)→ Switch to Dose-adjusted LMWH
- High-risk of valve thrombosis(See box below)+ No high VKA dose OR no anti-factor Xa testing available:
- Continue VKA(<5 mg/day)
- Continuous i.v. UFH(rarely used,只在 special cases)
Step 6 — Second / third trimester:Pregnancy Heart Team decision taking into account:
- High risk of valve thrombosis(See box below)
- Maternal choice
| VKA(usual care) | VKA, if higher risk of valve thrombosis | Dose-adjusted LMWH, if |
|---|---|---|
| 標準 | Class IIa | Lower risk of valve thrombosis;Availability of anti-factor Xa testing;Class IIb |
Step 7 — Last 2 weeks of pregnancy and deliveryb:
強制切換到 LMWH 或 UFH(VKA 不能在分娩前 2 週用,否則 fetal intracranial hemorrhage 風險高)。Delivery 規劃在 controlled inpatient setting。
High risk of valve thrombosis(圖下方 box):
- Right sided valves
- Mitral valve replacement
- Atrial fibrillation
- Poor LV function
- Previous thrombotic events
- Valve dysfunction especially stenosis
- Other clotting risks (smoker)
- Older generation valves
標註:aSee Figure 5 and Section 4.5.7;bSee Figure 5。
容易踩雷的地方:
陷阱 1 — 把 LMWH 當「無 anti-Xa 測也可」:LMWH 對 MHV 是高風險選擇,必須有 anti-Xa monitoring(peak 1.0-1.2 IU/mL anti-Xa)才能 substitute VKA。沒 anti-Xa 設施就要繼續 VKA(即使 >5 mg/day)。
陷阱 2 — Mitral valve replacement 用低劑量 VKA:MVR 是 high-risk valve thrombosis,target INR 通常 2.5-3.5(不是 standard 2-3)。Pre-conception 確認 target INR。
陷阱 3 — Last 2 weeks 不切換:分娩時 VKA 殘留 → fetal/maternal intracranial hemorrhage。一律切換到 LMWH(last 36h 改 UFH for delivery flexibility)。
陷阱 4 — DOAC 用於 MHV:絕對禁忌!RE-ALIGN trial 顯示 dabigatran in MHV inferior to warfarin。妊娠 + MHV 一律 VKA 或 LMWH,不可 DOAC。
💔 §12.6 Acute Heart Failure / Cardiogenic Shock — Figure 22
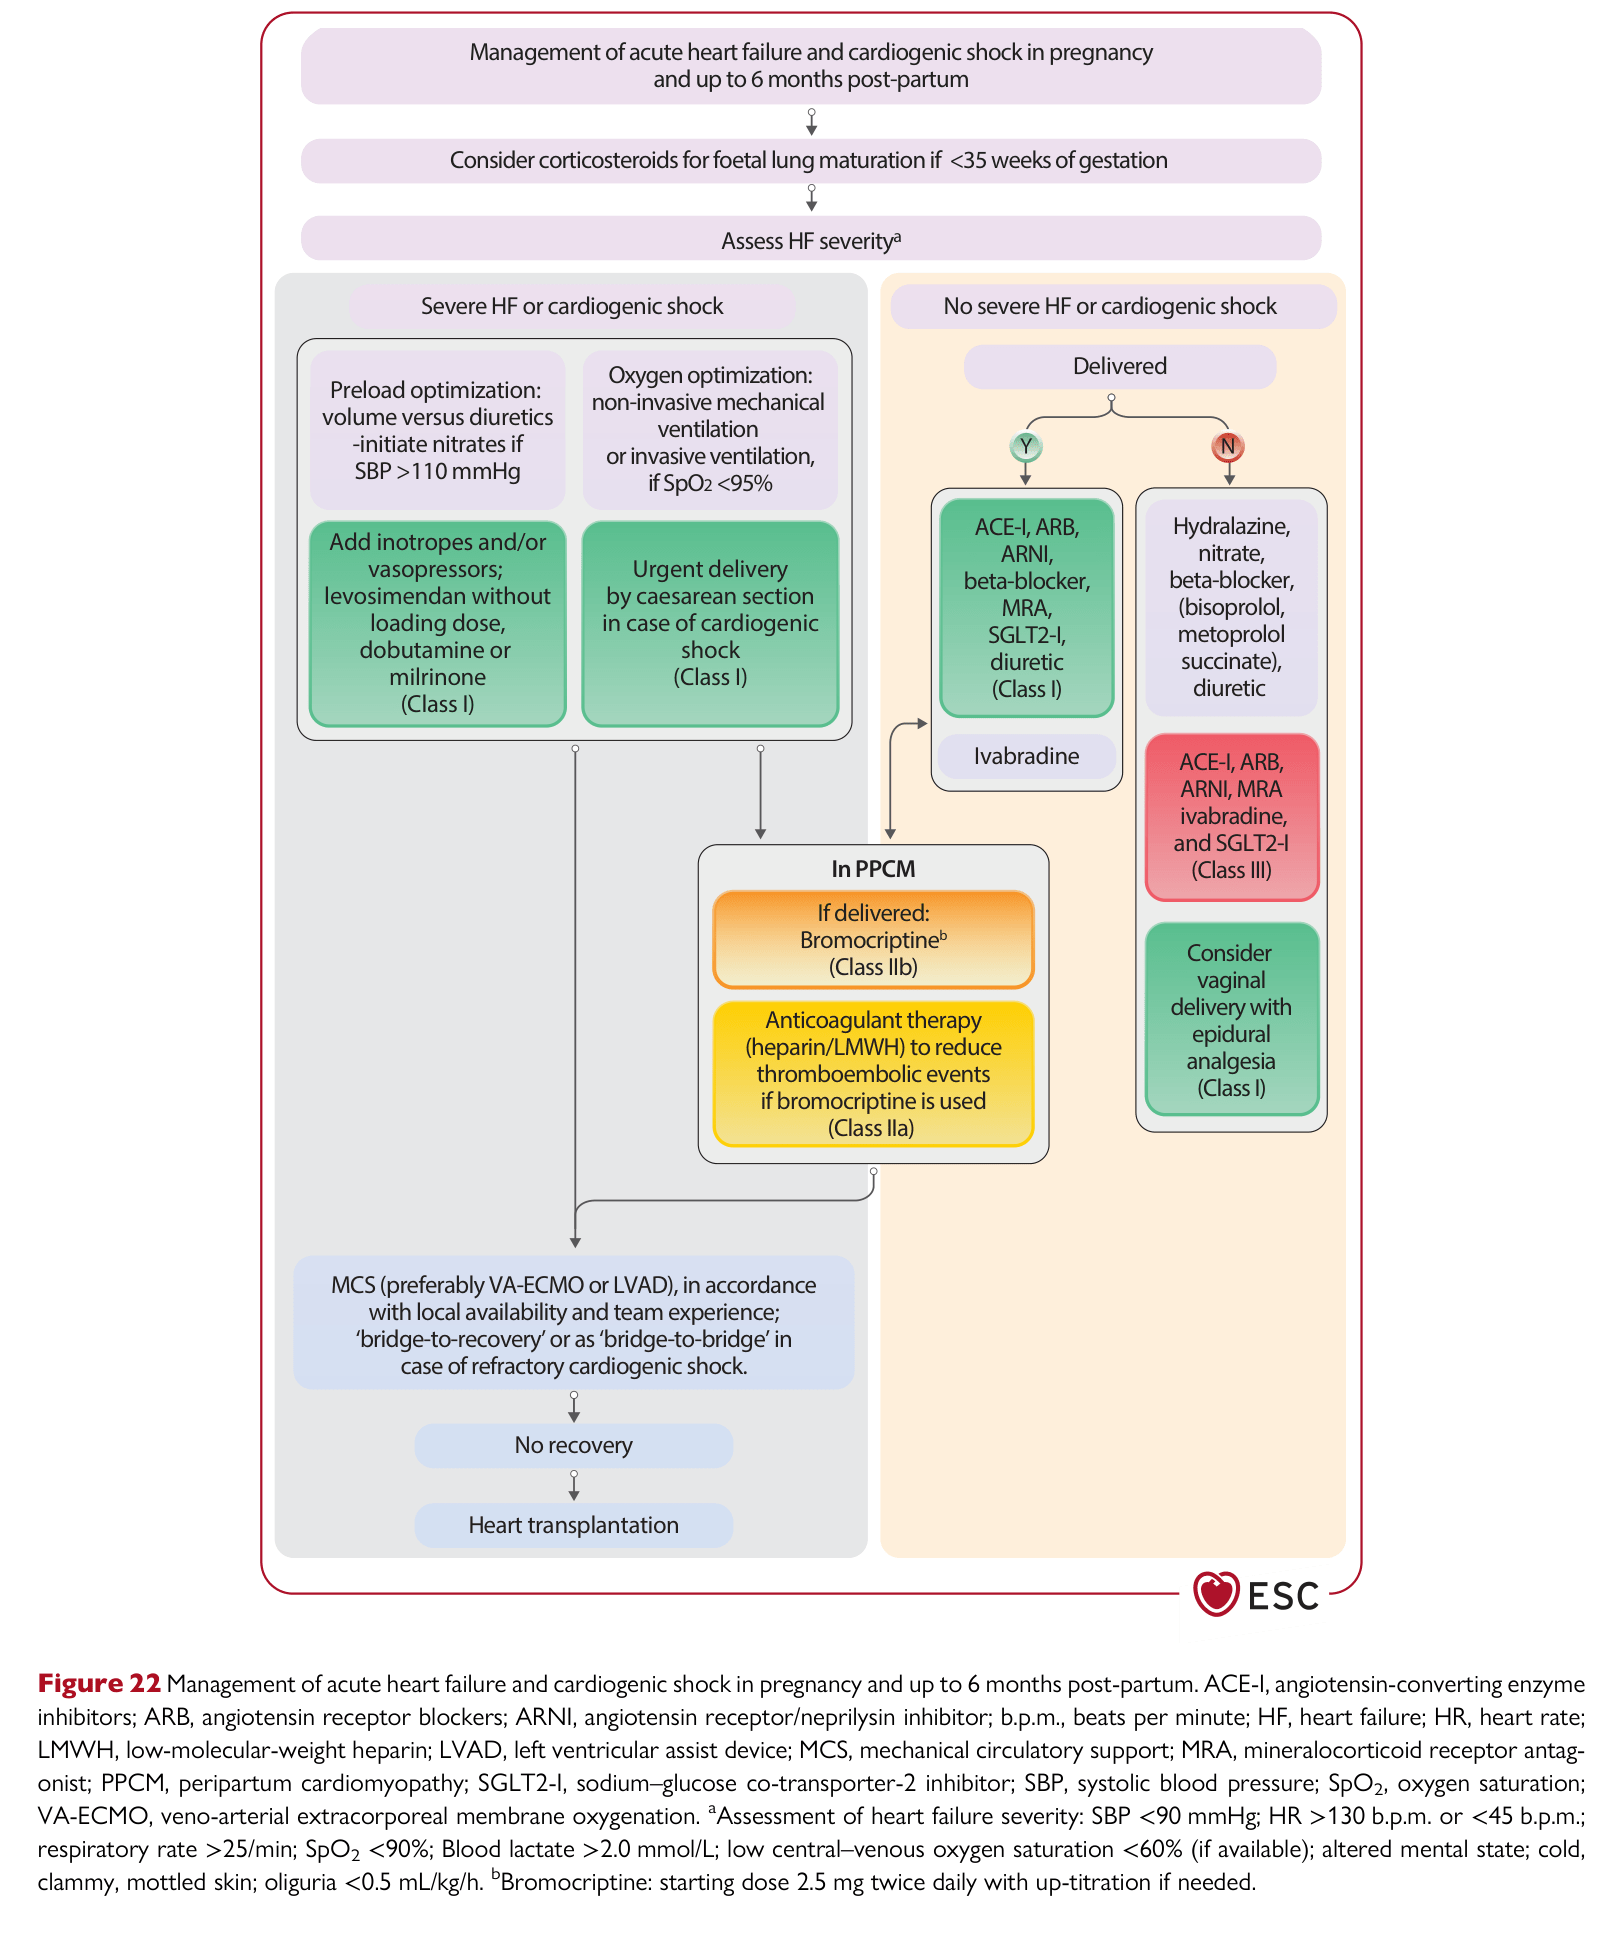
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 22
這張圖在回答什麼問題:孕期 / 產後 6 個月內的 acute HF / cardiogenic shock 怎麼分流?
Step 1:Management of acute heart failure and cardiogenic shock in pregnancy and up to 6 months post-partum。
Step 2:Consider corticosteroids for foetal lung maturation if <35 weeks of gestation。
Step 3 — Assess HF severity:分 Severe HF or cardiogenic shock 與 No severe HF or cardiogenic shock 兩條。
Step 4a — Severe HF or cardiogenic shock(左):
- Preload optimization:volume versus diuretics;initiate nitrates if SBP >110 mmHg
- Oxygen optimization:noninvasive mechanical ventilation;urgent delivery,if SpO2 <90%
- Add inotropes and/or vasopressors:levosimendan without loading dose、dobutamine 或 milrinone(Class I)
- Urgent delivery by caesarean section in case of cardiogenic shock(Class I)
Step 5a — In PPCM(subset of Severe):
- If delivered:Bromocriptinea(Class IIb)
- Anticoagulation therapy(heparin/LMWH)to avoid thromboembolic events if bromocriptine is used(Class IIa)
Step 6a — Persistent shock:
- MCS(preferably VA-ECMO or LVAD)—in accordance with local availability and team experience;’bridge-to-recovery’ or ‘bridge-to-bridge’ in case of refractory cardiogenic shock
- If no recovery → Heart transplantation
Step 4b — No severe HF or cardiogenic shock(右):分 Delivered vs Not delivered。
- Delivered (post-partum, no severe HF):start ACE-I、ARB、ARNI、BB、MRA、SGLT2i、diuretic(regular HF GDMT),加 ivabradine(若 HR 持續)。Bromocriptine 可考慮 for PPCM with persistent dysfunction。
- Not delivered (pregnancy, no severe HF):Hydralazine、nitrate、beta-blocker、bisoprolol、metoprolol succinate、diuretic(PPCM peripartum management);Consider vaginal delivery with epidural analgesia。
標註:aBromocriptine: starting dose 2.5 mg twice daily with up-titration if needed
容易踩雷的地方:
陷阱 1 — Cardiogenic shock 不立即 deliver:CS in pregnancy → 立即 caesarean(Class I)。延後 = 母體與胎兒雙輸。
陷阱 2 — Levosimendan 用 loading dose:在妊娠 / 產後 levosimendan 不用 loading dose(避免 hypotension)。Continuous infusion 6-12 µg/kg/min。
陷阱 3 — Dobutamine + bromocriptine 不抗凝:bromocriptine 促血栓;inotropic support + bromocriptine 同步 → 強制 prophylactic anticoagulation。
陷阱 4 — 沒 deliver 就用 ACEi:ACEi/ARB/ARNI/MRA/SGLT2i 都是妊娠禁忌。Not delivered 期間用 hydralazine、nitrate、metoprolol、bisoprolol、digoxin。Delivered 後才能恢復 GDMT。
陷阱 5 — 嚴重 PPCM 不送 MCS:refractory CS in PPCM 結果差。早期 VA-ECMO(bridge to recovery)顯著改善 survival;不要等 multi-organ failure 才考慮。
🧬 §12.7.1 Cardio-oncology + Pregnancy
整體立場
| 建議 | COR/LOE |
|---|---|
| 需要 cardiotoxic 治療的 cancer 孕婦 → PHT + cardio-oncology team 共管 | I C(新加) |
常見 cardiotoxic 化療在妊娠
| 藥物 | 妊娠期 | Trimester 注意 |
|---|---|---|
| Anthracyclines(doxorubicin) | 避免 1st trimester;2nd/3rd 可在 cardio-onco 監測下用 | 監測 cardiac biomarker + echo before / after each cycle |
| Trastuzumab | 禁忌全程(oligohydramnios、neonatal renal failure) | Delay 到產後 |
| Cyclophosphamide | 避免 1st trimester | 2nd/3rd 可在限制劑量下用 |
| Tyrosine kinase inhibitors | 多數禁忌或 limited data | 個別與 onco discuss |
| Methotrexate | 絕對禁忌(畸胎) | — |
| Hormonal therapy(tamoxifen) | 禁忌 | — |
| Radiation | 避免 with abdominal shielding;breast / head/neck/extremity OK with shielding | — |
Cardio-onco monitoring schedule
- Pre-pregnancy:baseline LVEF + GLS + cardiac biomarker;CV risk factor optimize。
- Pregnancy(若 cardiotoxic 治療):每 cycle 前後 LVEF + GLS + cTn + BNP。
- Post-partum:6 週、6 個月、1 年;之後 annual surveillance(看具體 anthracycline cumulative dose)。
🫀 §12.7.2 Heart Transplantation + Pregnancy
核心建議(新加 Class I)
| 建議 | COR/LOE |
|---|---|
| 產後再懷孕:postpone ≥1 年 after heart Tx,individual risk factors 納入考慮 | I C |
| Immunosuppression serum drug levels 監測:4 週直到 32w、2 週直到 36w、每週直到 delivery、6-12 個月 post-partum | I C |
Immunosuppression 的 pregnancy-safe 換藥
| 不行 | 替代 |
|---|---|
| Mycophenolate mofetil(強致畸 — first-trimester loss、cleft lip/palate) | Switch to azathioprine(pre-conception 6 個月) |
| Sirolimus / Everolimus(teratogenic) | Switch to tacrolimus 或 cyclosporine |
| Methotrexate(強致畸) | 避免 ≥3 個月 pre-conception |
實務:Heart Tx 後想懷孕的女性,pre-conception 6-12 個月就要由 transplant team + PHT 開始 review immunosuppression、stabilize 在 azathioprine + tacrolimus + prednisone。
Heart Tx 妊娠的特殊風險
- Allograft rejection:immunosuppression level fluctuation 是 trigger,定期 EMB(個別評估)
- Pre-eclampsia 與 HDP 風險升高(calcineurin inhibitor effect on renal)
- Vasculopathy 進展與 ischaemic events
- Preterm 與 SGA 風險升高
- Infection(CMV reactivation 等)
📋 §12.5-12.7 重點 Recommendations 整理
| 主題 | 2025 建議 | COR/LOE | vs 2018 |
|---|---|---|---|
| Severe MS / AS pre-conception evaluation | mWHO IV → PHT counselling | I C | 確認 |
| Severe MS with HF | Beta-blocker + diuretic → percutaneous valvotomy | IIa C | 確認 |
| MHV anticoagulation:care plan documented pre-pregnancy | Pre-pregnancy 或 pregnancy detected 後立即 PHT 制定計畫 | I C | 新加 |
| Valve surgery during pregnancy | Only if maternal mortality risk + other treatment failed | IIa C | 明確化(從 IIb → IIa) |
| Acute HF / CS in pregnancy:inotropes | Levosimendan / dobutamine / milrinone | I C | 新加 |
| ACEi/ARB/ARNI/MRA/ivabradine/SGLT2i in pregnancy | 禁忌 | III C | 明確化(共識) |
| Cardio-onco + pregnancy | PHT + cardio-onco team 共管 | I C | 新加 |
| Heart Tx + pregnancy:postpone ≥1 年 | Allograft 穩定後 ≥1 年 | I C | 新加 |
| Heart Tx + pregnancy:IS monitoring | 4 週 → 2 週 → 每週 → post-partum 6-12 個月 | I C | 新加 |
✅ 重點回顧
- Valvular HD(Fig 20):Mitral stenosis + 嚴重 AS 是高危;severe regurgitation 通常 well-tolerated;MS / AS 急性處置 → BB + diuretic ± percutaneous valvotomy。
- MHV anticoagulation(Fig 21):依 valve thrombosis 風險與 VKA 劑量分流;<5 mg/day VKA 可整孕期;>5 mg/day 1st trimester 換 LMWH(anti-Xa 監測);last 2 週改 LMWH/UFH;DOAC 絕對禁忌。
- Acute HF / CS(Fig 22):分 severe vs no severe;severe → preload optimization + inotropes + 立即 caesarean;PPCM 特殊 → bromocriptine + 強制抗凝;refractory shock → MCS(VA-ECMO / LVAD)→ Tx。
- Cardio-onco:PHT + cardio-onco 共管 I C;trastuzumab、methotrexate、tamoxifen 全程禁忌;anthracycline、cyclophosphamide 在 2nd/3rd trimester 可在 monitor 下用。
- Heart Tx:postpone ≥1 年 after Tx I C;mycophenolate → azathioprine pre-conception;IS level 4-2-1 週監測。
📖 References
- De Backer J, Haugaa KH, Hasselberg NE, et al. 2025 ESC Guidelines for the management of cardiovascular disease and pregnancy. Eur Heart J 2025;46(43):4462–4568. doi:10.1093/eurheartj/ehaf193
- Vahanian A, Beyersdorf F, Praz F, et al. 2025 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J 2025;46(45):4635-4796.
- Bauersachs J, Konig T, van der Meer P, et al. Pathophysiology, diagnosis and management of peripartum cardiomyopathy: ESC HFA position statement. Eur J Heart Fail 2019;21:827-843.
- Eikelboom JW, Connolly SJ, Brueckmann M, et al. Dabigatran versus warfarin in patients with mechanical heart valves (RE-ALIGN). N Engl J Med 2013;369:1206-1214.
- Lyon AR, Lopez-Fernandez T, Couch LS, et al. 2022 ESC Guidelines on cardio-oncology. Eur Heart J 2022;43:4229-4361.
- Acuna SA, Lin AE, Patel JK, et al. Pregnancy outcomes after heart transplantation: A systematic review. J Heart Lung Transplant 2022;41:S147.
本文以教學為目的整理 2025 ESC Guidelines for the management of cardiovascular disease and pregnancy;所有原文 Figure 之版權屬 ESC。商業使用請洽 ESC 取得授權。
