

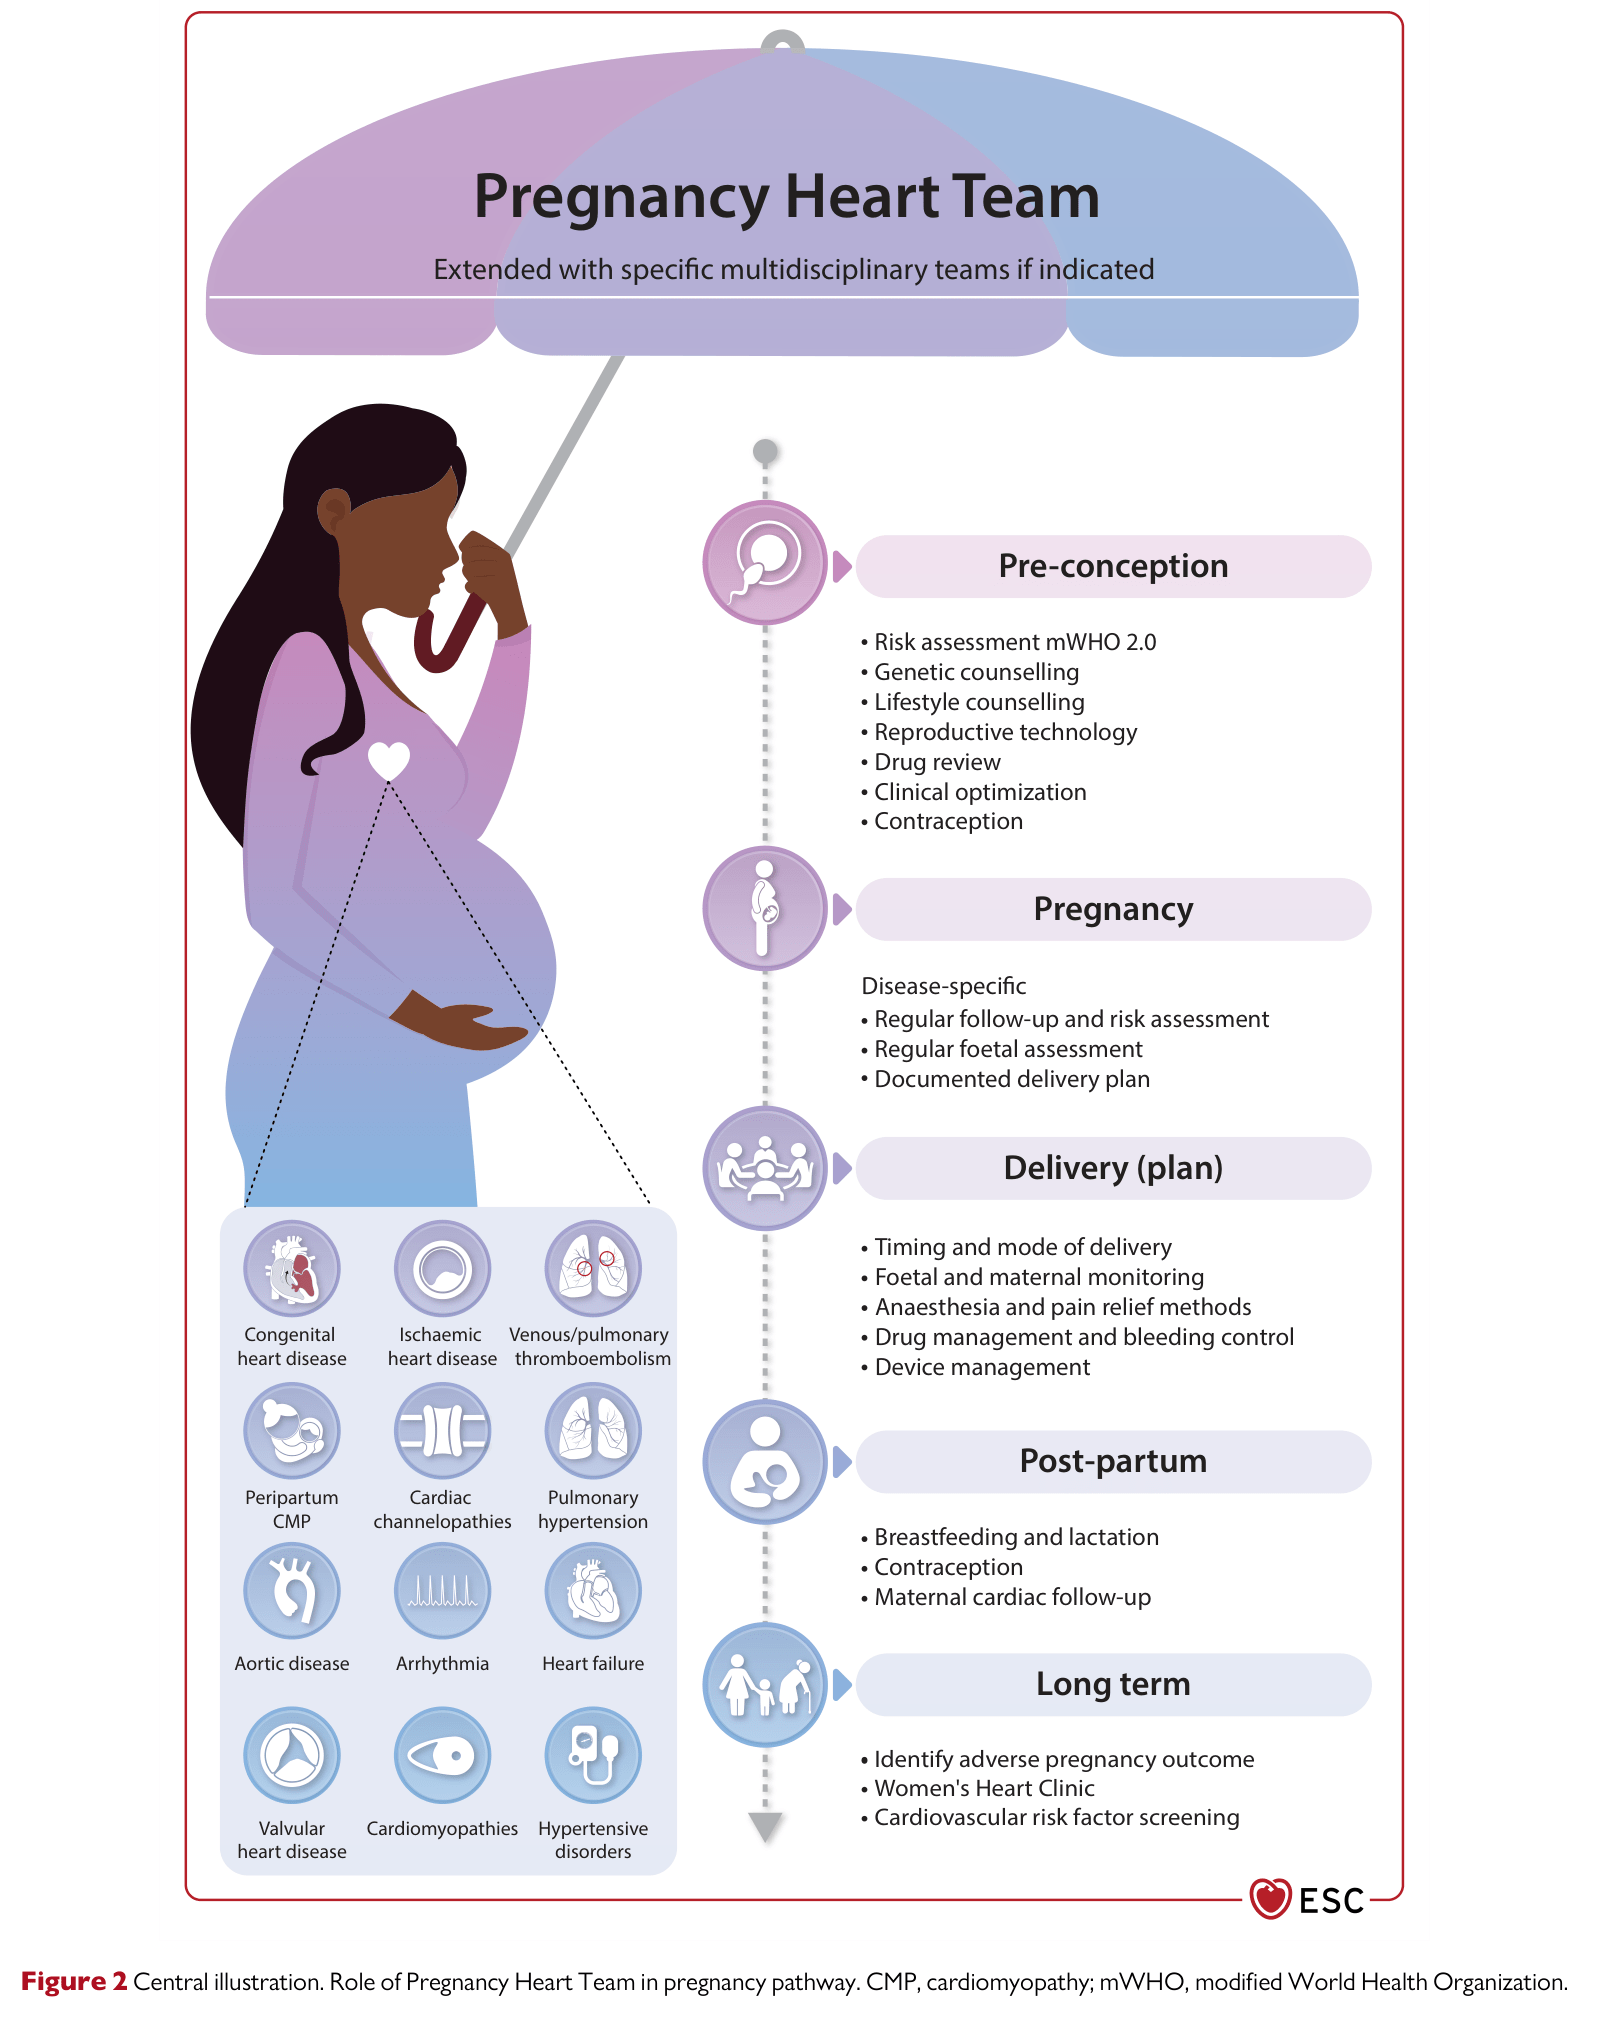
- 2025 版把 Pregnancy Heart Team (PHT) 推到一個全新獨立章節(§4),跨越 pre-conception → pregnancy → delivery → post-partum → long term 五個階段;mWHO 2.0 class II–III 以上強制由 PHT 評估 (I C)。
- mWHO IV 的處理大改:2018 是 COR III(pregnancy contraindicated);2025 把它變成「PHT 主導的 shared decision-making」(I C),強調 woman autonomy 與透明 counselling,不再單方面禁止。
- §13 「Adverse Pregnancy Outcomes (APO) 與長期管理」是全新章節—把 HDP、GDM、SGA、preterm delivery、pregnancy loss、placental abruption 統稱為 CV 風險 modifier,要求所有有 APO 史的女性都該做 CV 風險評估 + 長期 lifestyle counselling (I B),建立 Women’s Heart Clinic 制度。
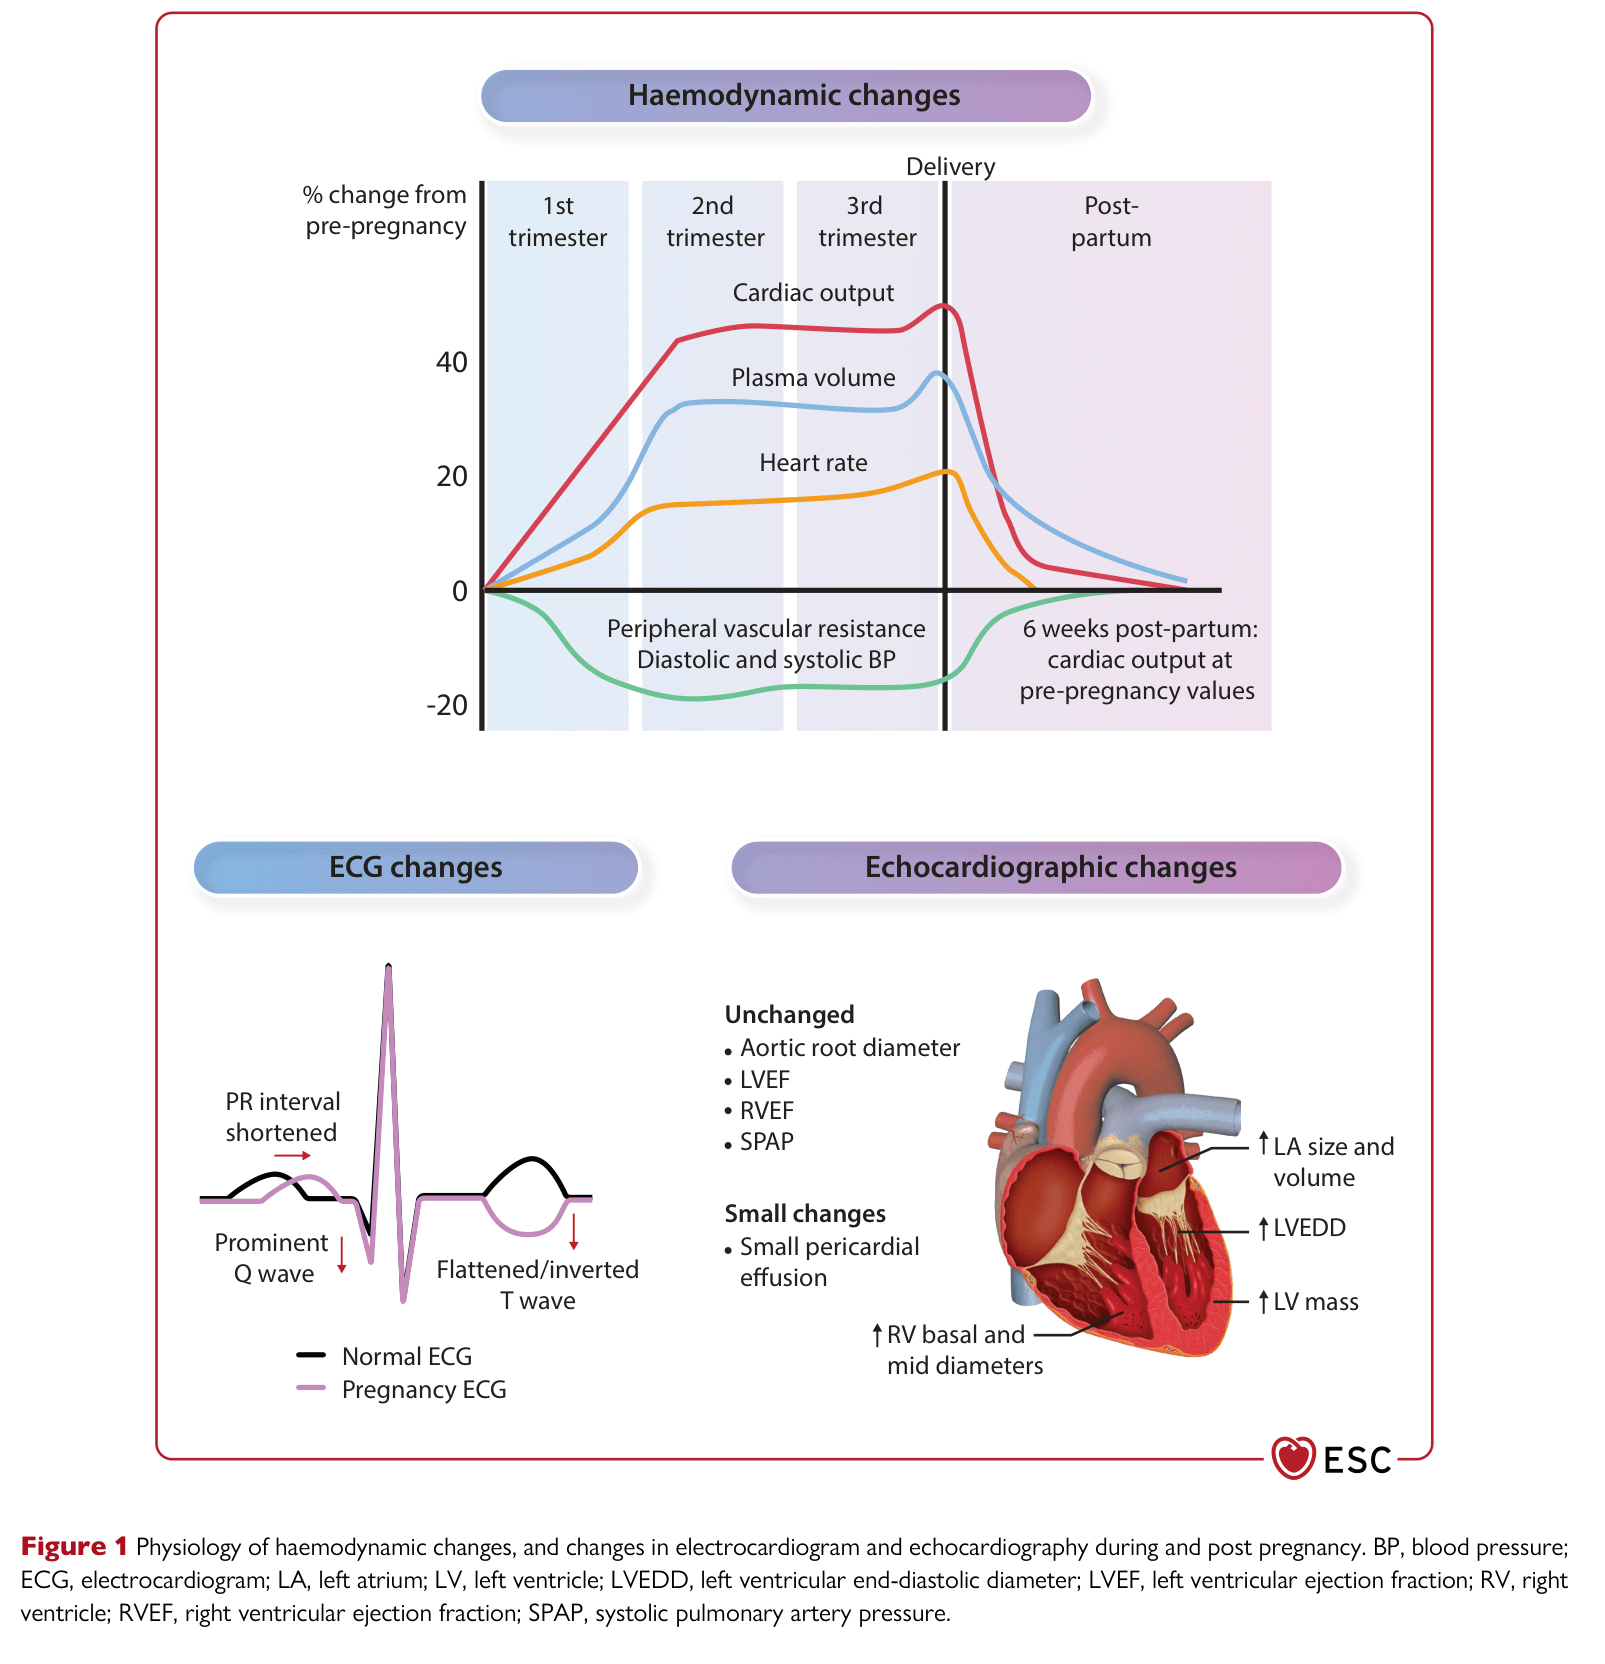
懷孕是對心臟的生理性壓力測試,理解這些變化,就懂哪些病灶危險、哪個時間點最危險:
- 血量與心輸出大增:到中孕期血漿容積增約 40–50%、心輸出增 30–50%(心率↑+每搏量↑),全身血管阻力下降。對固定狹窄病灶(嚴重二尖瓣/主動脈瓣狹窄、肺高壓),心臟無法因應增加的流量 → 肺鬱血、右心衰竭、暈厥甚至猝死。
- 高凝狀態:凝血因子上升、靜脈鬱滯 → VTE 與瓣膜血栓風險大增(機械瓣抗凝是難題)。
- 三個最危險的時間點:(1) 中孕期(容積負荷峰值);(2) 生產/分娩(每次宮縮把 ~300–500 mL 血擠回循環、用力時的 Valsalva);(3) 產後即刻(子宮收縮把大量血液送回中央循環+下腔靜脈壓迫解除 → 「自體輸血」可誘發肺水腫)。所以監測不能在產後立刻放鬆。
🌟 三大 Highlight
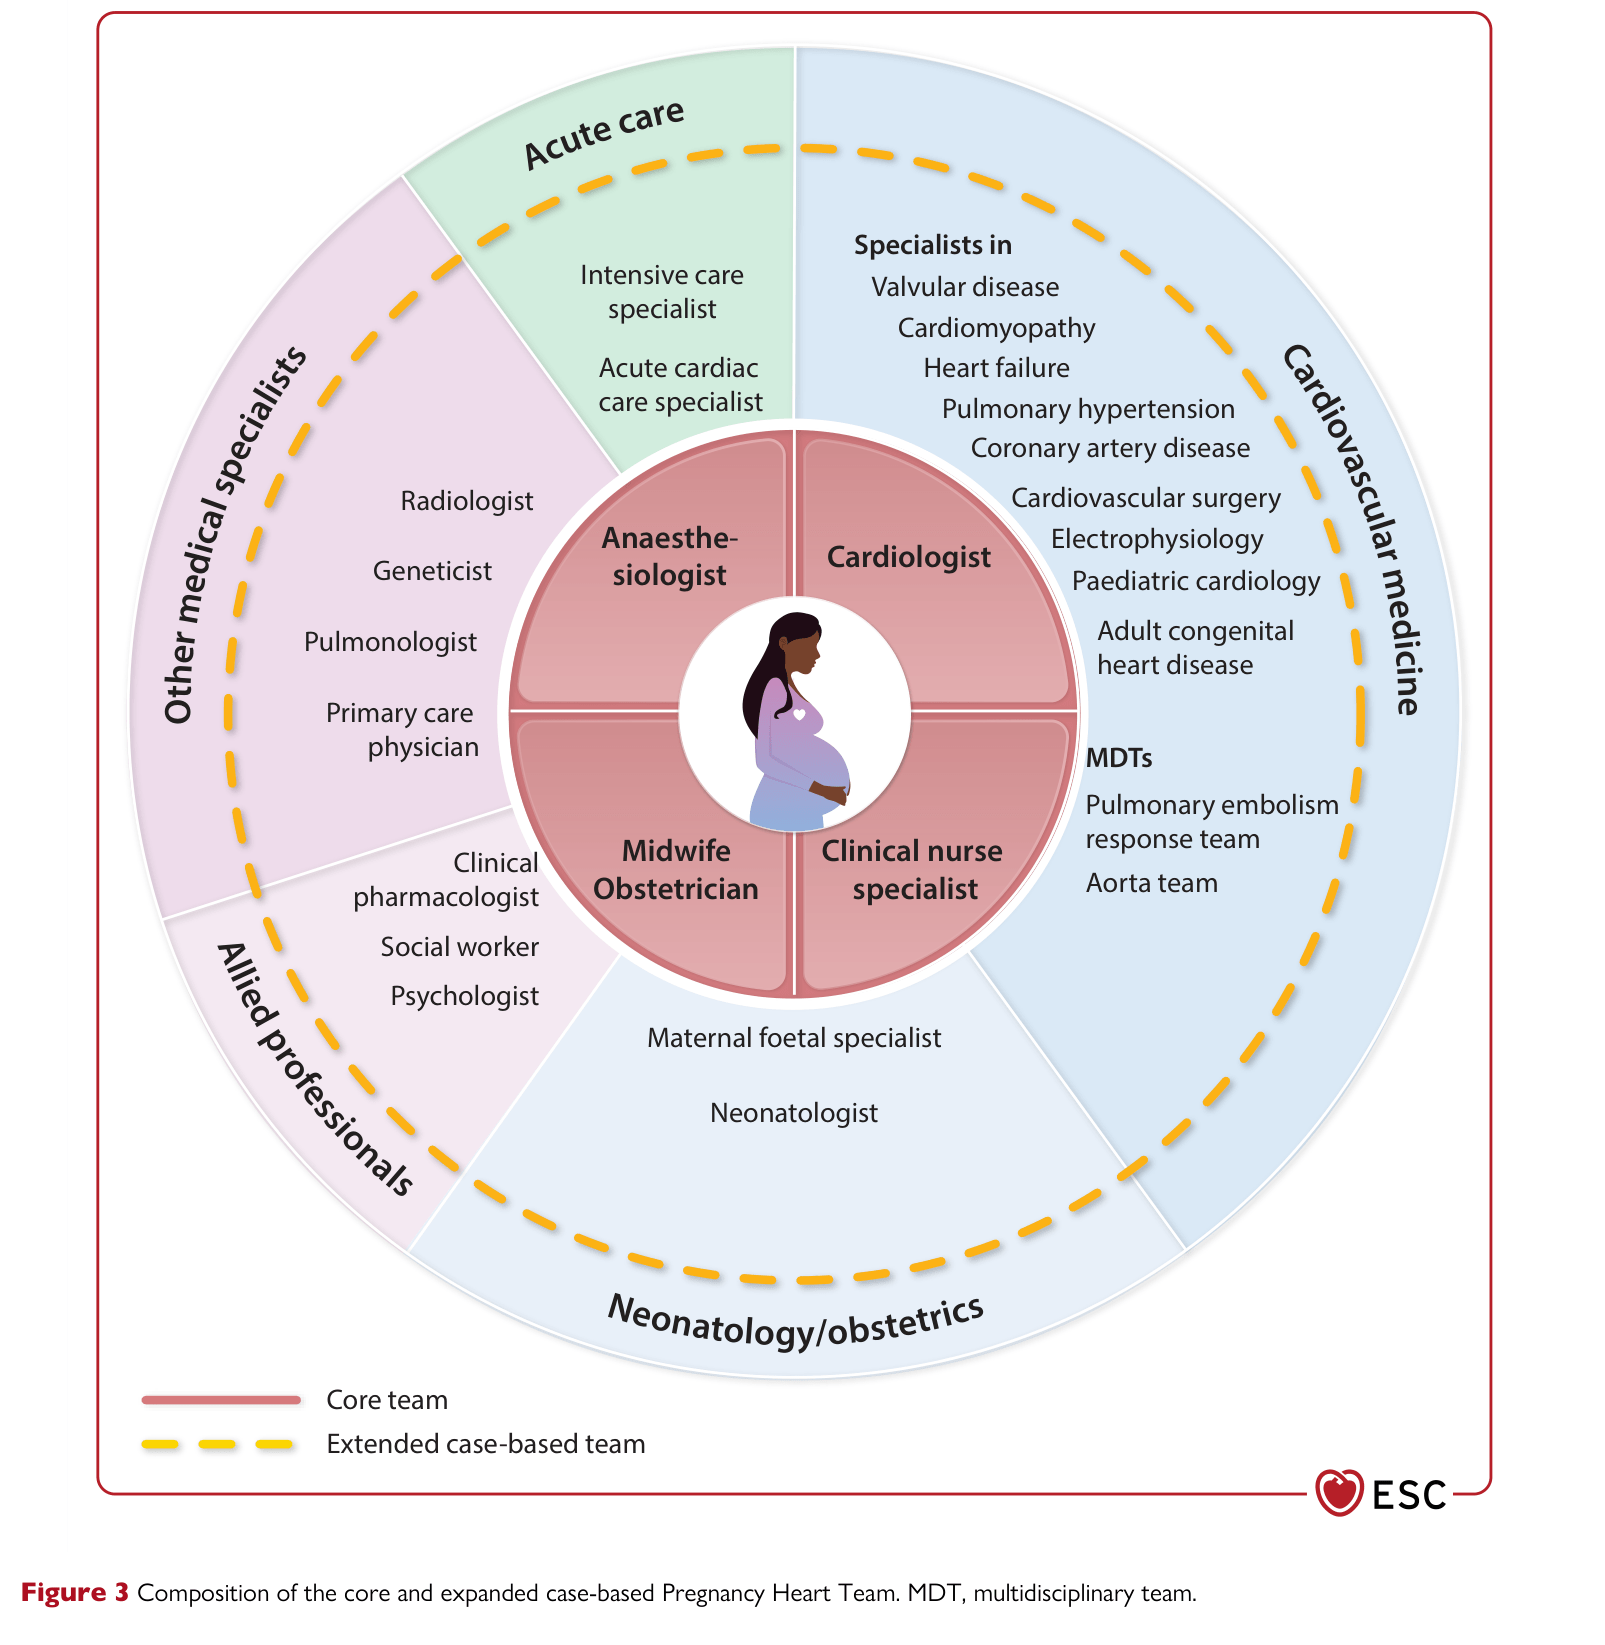
2018 版有 PHT 概念但散落於各個 disease section,沒有獨立規範。2025 版給 PHT 一個專屬章節(§4),明確定義「核心團隊」(cardiologist、obstetrician、cardiac/midwife nurse、anaesthesiologist)與「擴充團隊」(imaging、EP、CT surgery、neonatology、genetics、social work…依疾病配置 — Figure 3)。任務涵蓋 5 階段:pre-conception counselling → pregnancy follow-up → 規劃 delivery → post-partum monitoring → long-term。對應 mWHO 2.0 class II–III 以上者強制由 PHT 管理(I C)。
2018 版對 mWHO IV(如嚴重 PAH、systemic RV、Eisenmenger、severe MS with symptoms 等)標記為「pregnancy contraindicated, COR III」。2025 版改寫:仍承認這群風險極高,但移除「禁止」的單方面立場,改為「PHT 主導的全面 counselling + 共享決策」I C,含意涵:(1) 尊重 woman autonomy;(2) 強調風險透明溝通;(3) 若決定繼續懷孕,需有完整的 termination 選項討論與心理支持。這對應 ESC 整體把 shared decision-making 提升到指引核心的趨勢。
2025 版承認過去被忽略的事實:不良妊娠結局是後續 CVD 的強力預測因子。HDP(hypertensive disorders of pregnancy)使 future CV event 風險 2-4 倍、GDM 使 T2DM 風險 7 倍、SGA / preterm 與 ischaemic heart disease 連動;累積證據(CALIBER、AHA Scientific Statement 2021)支持把 APO 史列入 CV 風險評估。新章節給 4 件 actionable items:(a) 所有 APO 史女性都該 risk assessment I B;(b) 把 APO 寫入 CVD 風險文件;(c) 提供 lifestyle counselling;(d) 建立 Women’s Heart Clinic 整合 multidisciplinary 追蹤(Fig 25)。這是把妊娠當「壓力測試」的概念第一次正式入指引。
📊 重大變更摘要表
| 主題 | 2018 舊版 | 2025 新版 | 為什麼改 |
|---|---|---|---|
| Pregnancy Heart Team | 概念,散見各章節 | 獨立章節 §4;mWHO II–III 以上 PHT 管理 I C | ROPAC 等 registry 顯示 PHT 管理改善 outcome;標準化各國照護 |
| mWHO IV 處置 | Pregnancy contraindicated III | PHT 主導 shared decision-making(含 termination 選項與心理支持)I C | 尊重 patient autonomy;提升 counselling 品質;對齊現代 SDM 框架 |
| mWHO 分類 | 原 mWHO | mWHO 2.0:refined 與 expanded categories(含 APOL1 等基因標記) | 10 年新證據累積,原分類顆粒度不夠 |
| BNP / NT-proBNP pre-pregnancy | 未明確 | HF 任何病因 / PPCM / CMP / ACHD / PAH 患者 pre-pregnancy 測 IIa B | baseline 數值有助於妊娠中辨識惡化趨勢 |
| 藥物表呈現 | 大表(單篇主圖) | 移到 Supplementary;用 Figure 6(一張)總結首選 / 次選 / 禁忌 | 實務臨床決策需要視覺化 single page reference |
| HTAD(heritable thoracic aortic disease) | 固定 diameter 閾值 | Gene/variant-based:MFS(FBN1)、LDS-TGFBR1/2、LDS-TGFBR1/2 + SMAD2/3、nsHTAD、BAV 各有不同閾值(Figure 8) | HTAD III ROPAC 數據;基因型對 dissection 風險有顯著差異 |
| PPCM 治療 | HF GDMT 為主 | Bromocriptine 可考慮(IIb),若用 bromocriptine → 強制 prophylactic anticoagulation IIa;Fig 7 summary | EHJ 2017 / PPCM 多中心研究;BB-EFFECT 試驗 |
| HDP BP target | 不明確或 <150/100 | 目標 BP <140/90 mmHg I B | CHAP trial(NEJM 2022):active treatment 對胎兒無不利、改善 maternal outcome |
| Cardiac arrest 三新建議 | 未具體 | (1) Manual left uterine displacement(≥20w)I C;(2) IV access above diaphragm I C;(3) 不可因為 teratogenicity 顧慮停藥 I C | Maternal cardiac arrest 累積案例與機轉證據;2015 AHA pregnancy CA 指引導入 |
| Resuscitative caesarean section | 有提 | 明確 ROSC 4 min 後仍未恢復 + 胎兒可救 → 立即 caesarean IIa(Fig 19) | 降低 aortocaval compression、提高 maternal survival 與胎兒救援機會 |
| VTE 診斷流程 | 散落各章 | DVT(Fig 9)與 PE(Fig 10)專用 algorithm;anticipated diagnostic delay → empiric LMWH IIa | 避免診斷拖延造成 CV / 母體死亡 |
| Chest pain in pregnancy | 無 algorithm | Figure 11:ACS / SCAD / PE / acute aortic syndrome 鑑別 algorithm | SCAD 是孕期年輕女性 ACS 主因(佔 ≥40%);過去常被誤診 |
| Heart transplantation | Pregnancy 後 ≥1 年沒明確 | 建議 postpone ≥1 年 after heart Tx I C;immunosuppression level 4-2-1 週監測 I C | Tx 後妊娠累積案例分析;給明確 timing 與 monitoring schedule |
| Cardio-oncology + pregnancy | 無 | 需要 cardiotoxic 治療的 cancer 妊娠 → PHT + cardio-onco team 共管 I C | 反映 2022 ESC cardio-oncology guidelines 與新趨勢 |
| §13 APO 長期管理 | 無此章節 | 全新章節:APO 史 → CV 風險評估 + lifestyle counselling I B;新發 post-partum HTN algorithm(Fig 24);APO 長期 algorithm(Fig 25);Women’s Heart Clinic 概念 | 累積 cohort 證據(HDP→ CV event RR 2-4,GDM→T2DM RR 7);性別差異 CV care 改革 |
| Pre-conception genetic testing | 有提 | Figure 4 結構化:Yield 與 impact 分四群(aortic disease / channelopathies / CMP / CHD & PAH);新增 pre-implantation 選項討論 | genetic counselling 標準化、PGT-M 等技術普及 |
| Breastfeeding rules | 散落 | 明確列入 §13.2;藥物 lactation 對照(Fig 6 右側);breastfeeding 可能對母體 CV 有保護作用 | ROPAC III: breastfeeding 與 MACE 減少相關(HTAD subgroup) |
🧭 Central Illustration — Pregnancy Heart Team 全週期角色(Figure 2)
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
這張圖在回答什麼問題:Pregnancy Heart Team 不是「孕期才開始的事」,要從 pre-conception 延伸到 long term。圖把5 個照護階段串成一條「保護傘」,並列出每階段 PHT 該執行的具體 tasks。
逐步走完(圖上由上而下的紫色保護傘):
左下的 disease cluster 圖示列出 PHT 涵蓋的疾病範圍:CHD、ischaemic HD、VTE/pulmonary thromboembolism、PPCM、cardiac channelopathies、PAH、aortic disease、arrhythmia、HF、valvular HD、CMP、hypertensive disorders。從 pre-pregnancy 一路追到 long-term,覆蓋整個 cardiovascular spectrum 的女性。
容易踩雷的地方:
🧠 Figure 1 — 妊娠生理變化(為什麼妊娠對心血管是「壓力測試」)
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
三個面向、五個時期(1st / 2nd / 3rd trimester / delivery / post-partum):
- Haemodynamic changes:CO(cardiac output)↑ 30-50%(peak 第 2 trimester)、plasma volume ↑ 30-50%、HR ↑ 10-20 bpm、peripheral vascular resistance ↓、diastolic + systolic BP 在第 2 trimester 微降、第 3 trimester 回升。產後 6 週恢復 pre-pregnancy。
- ECG changes:PR interval 縮短、Q wave 變明顯、T wave 變平或倒置(非缺血)。
- Echo changes:aortic root diameter / LVEF / RVEF / SPAP 通常 unchanged;可能 small pericardial effusion、small changes in LA size / mass / RV diameter。
臨床意涵:妊娠相當於 4-6 個月的慢性 volume + CO 負荷測試。原本邊緣性的心臟病會在妊娠 expressed,這就是為什麼 mWHO IV 的患者在妊娠期惡化的可預測性如此高。
🩺 Figure 3 — Pregnancy Heart Team 組成
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
Figure 3 內圈是核心團隊(Core team — 紅色虛線內):cardiologist、anaesthesiologist、obstetrician、midwife、clinical nurse specialist。外圈是case-based extended team(黃色虛線):依疾病動態納入相應 subspecialist。
外圈四個 quadrant:
- Acute care:intensive care specialist、acute cardiac care specialist
- Cardiovascular medicine:valvular HD、CMP、HF、PAH、coronary、cardiovascular surgery、EP、paediatric cardiology、ACHD;外加 MDT(pulmonary embolism response team、aorta team)
- Neonatology / obstetrics:maternal foetal specialist、neonatologist
- Other medical specialists:radiologist、geneticist、pulmonologist、primary care physician
- Allied professionals:clinical pharmacologist、social worker、psychologist
實務意涵:PHT 不是固定 5 人,是動態的問題解決組合。指引明確列出「每個情境誰該加入」,避免「漏了重要 expert」。
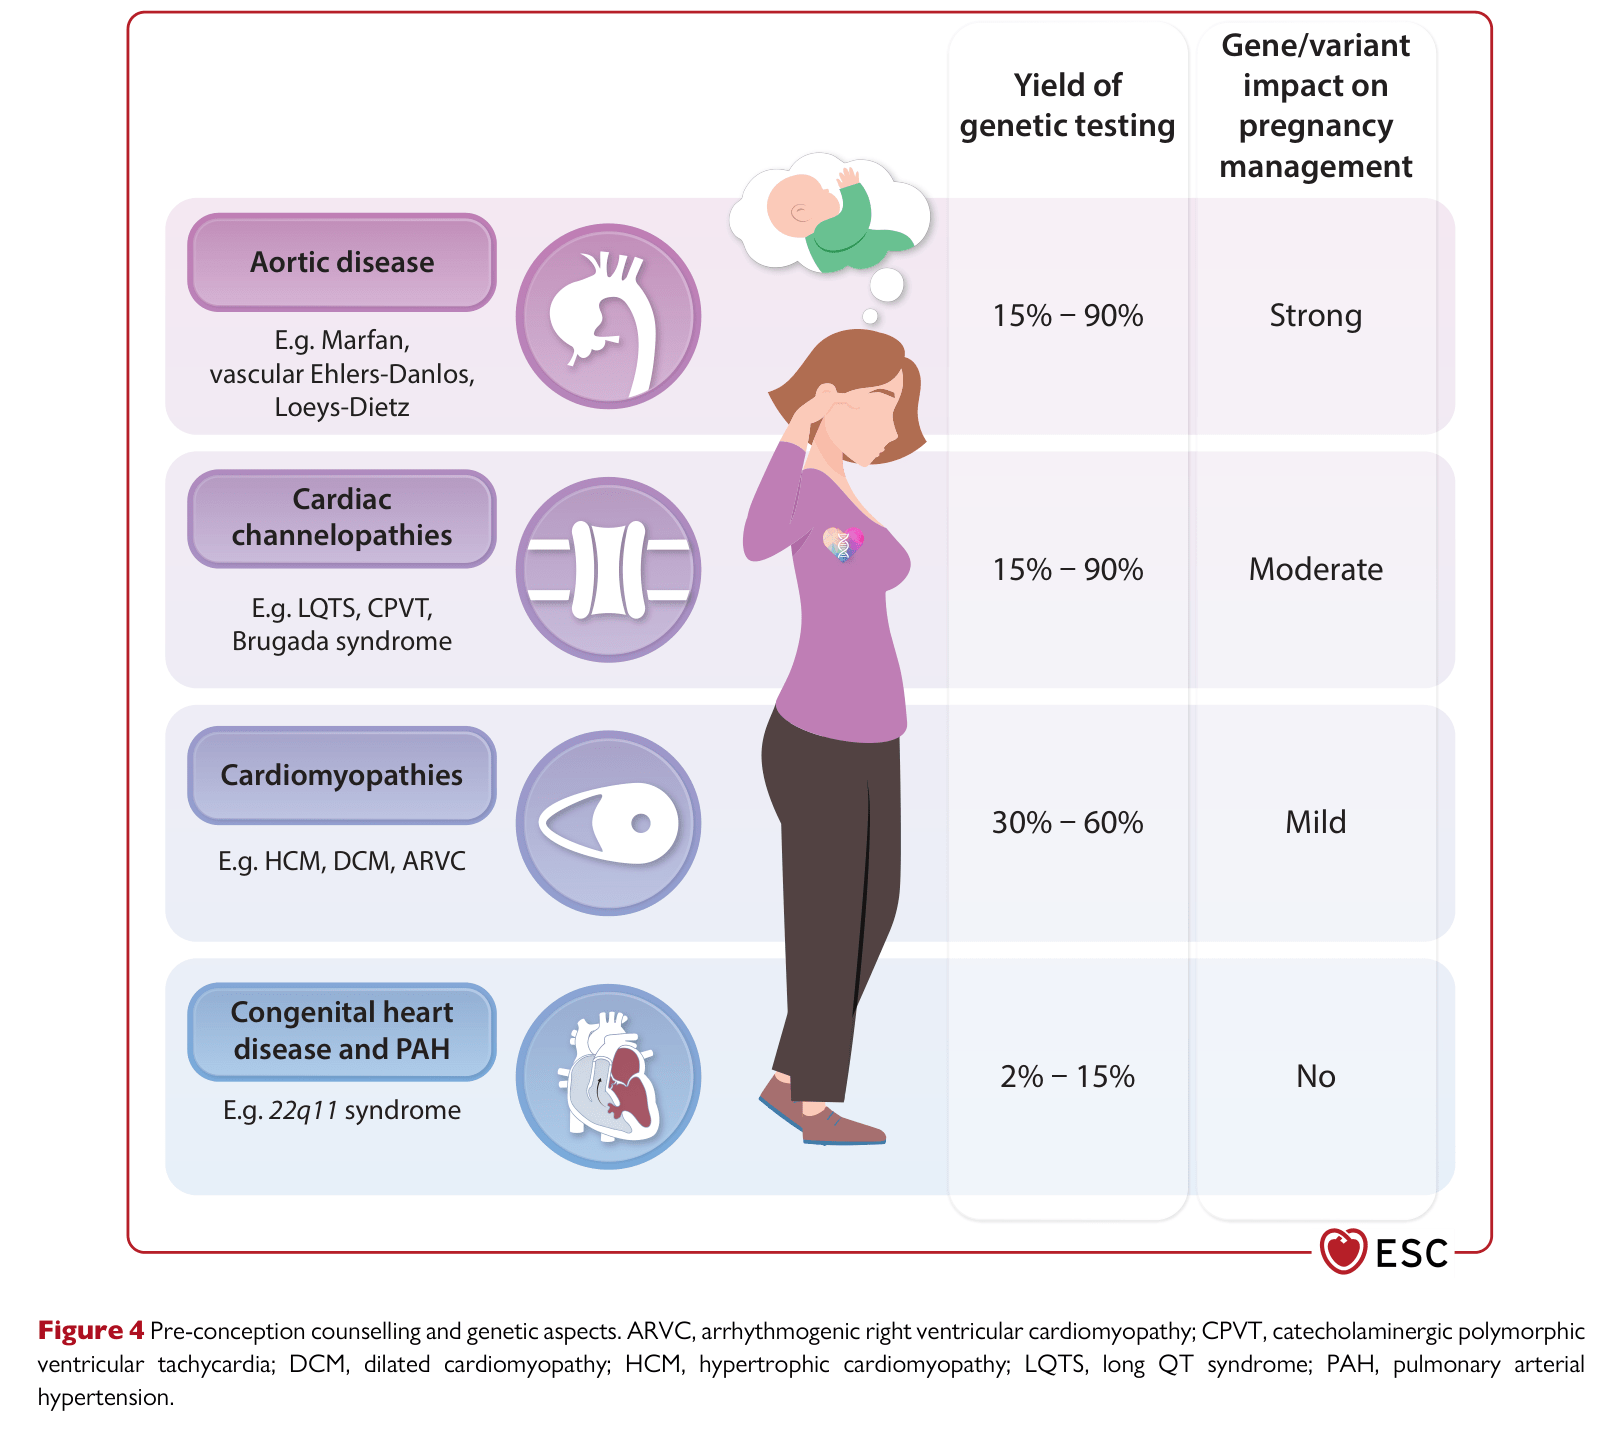
🧬 Figure 4 — Pre-conception 諮詢與基因 testing yield
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
四群疾病的基因 testing 報酬率(yield)與對妊娠管理的影響強度(Gene/variant impact):
| 疾病群 | 例 | Yield | Impact on pregnancy management |
|---|---|---|---|
| Aortic disease | Marfan、vEDS、Loeys-Dietz | 15–90% | Strong(決定手術閾值、產式、藥物) |
| Cardiac channelopathies | LQTS、CPVT、Brugada | 15–90% | Moderate(決定 BB 劑量、產後管理) |
| Cardiomyopathies | HCM、DCM、ARVC | 30–60% | Mild(妊娠 management 影響較小) |
| CHD & PAH | 22q11、TBX1 等 | 2–15% | No(孕期治療不變) |
實務意涵:Aortic disease 的 yield 與 impact 都最強—Marfan、Loeys-Dietz 患者在 pre-conception 就該做 testing,因為結果直接影響手術閾值(Figure 8)。CHD 的 yield 低但仍應考慮(recurrence risk 給 offspring)。
🧪 Figure 5 — 緊急分娩 + 治療性抗凝
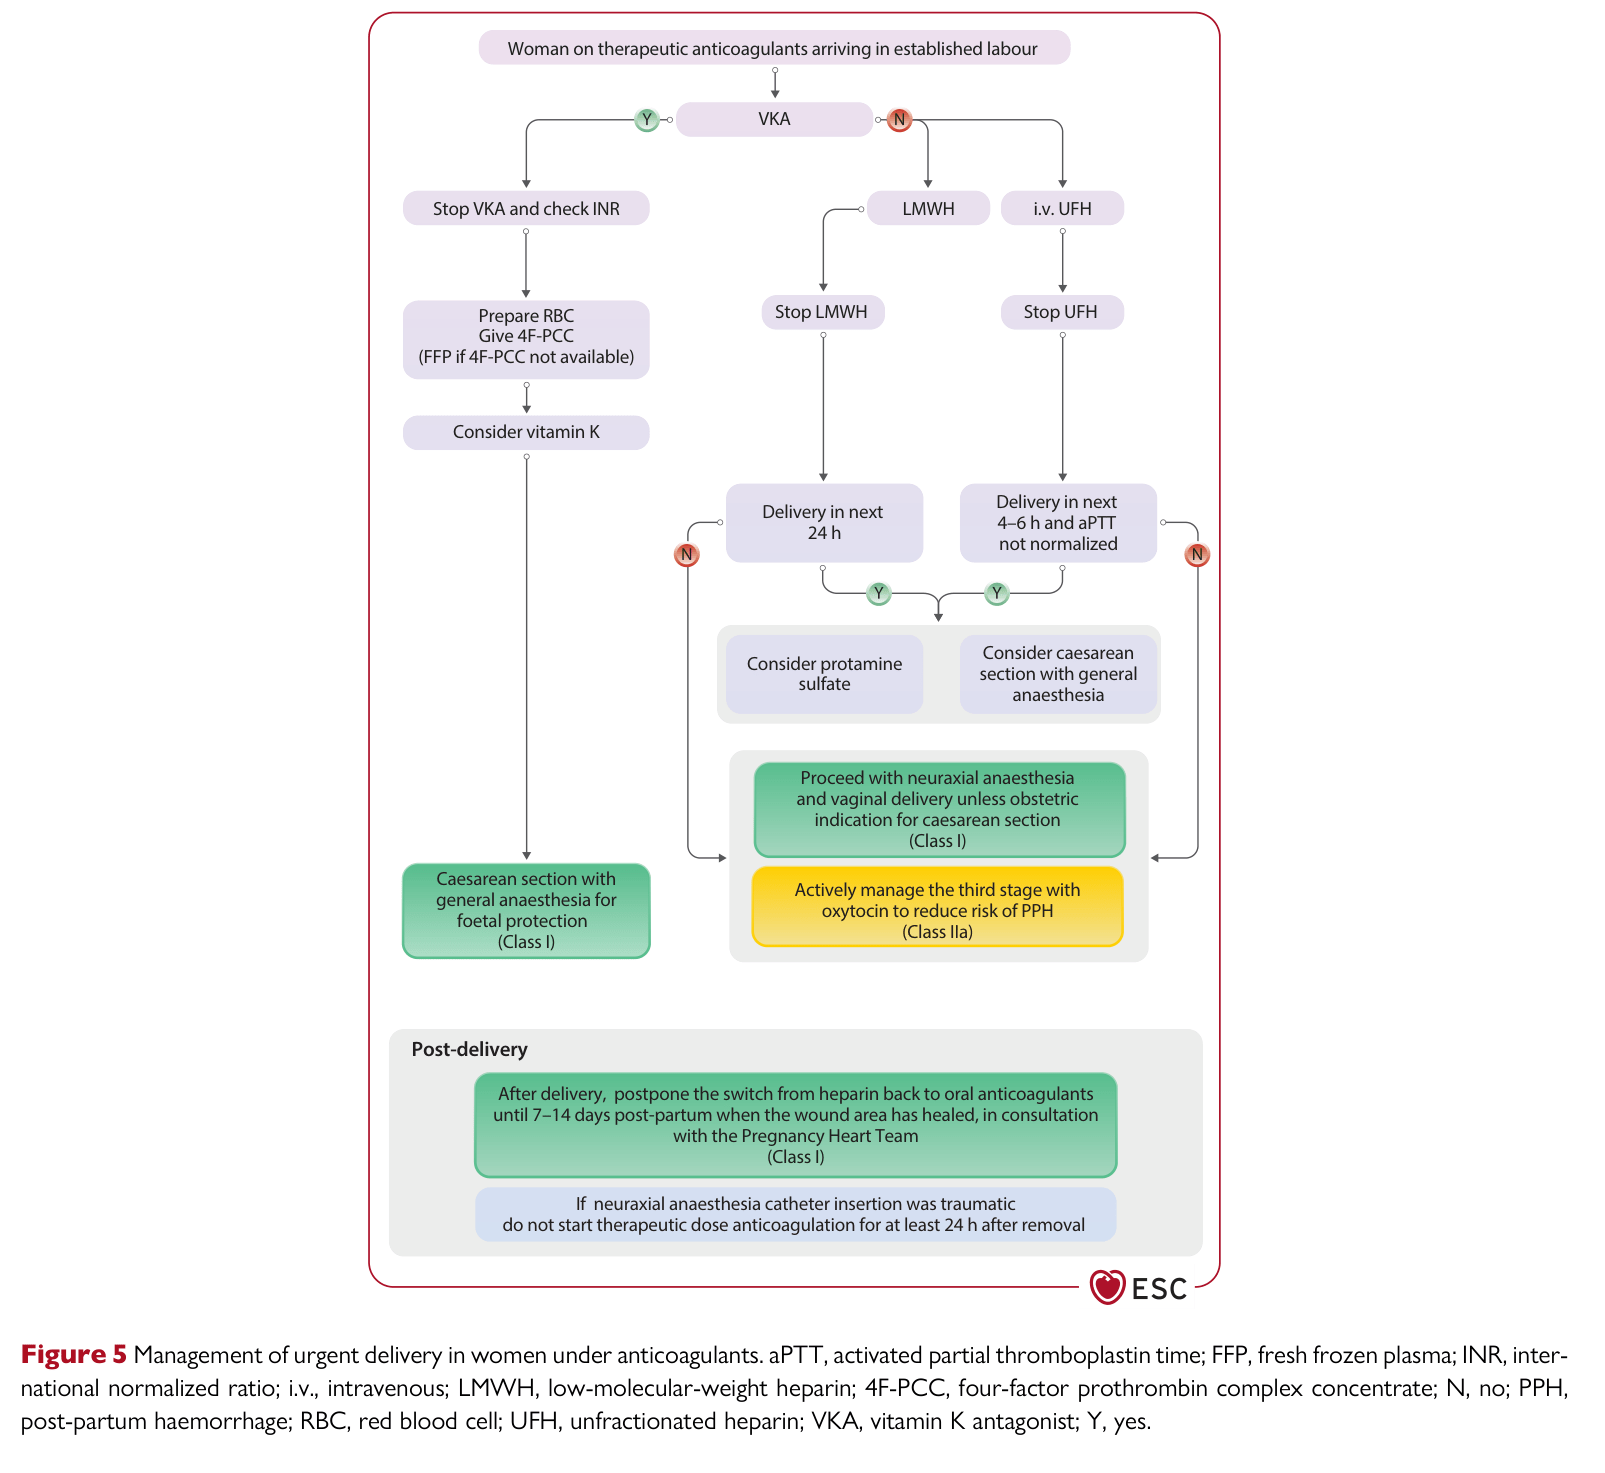
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
這張圖在回答什麼問題:治療性抗凝(VKA / LMWH / UFH)中的孕婦突發要分娩,怎麼快速處理?逐步邏輯詳細解析會放在第 II 篇(與其他 valvular / MHV 抗凝主題一起),這裡只放圖作為總論預覽。重點:VKA 必須立即停 + 4F-PCC 反轉 + caesarean for foetal protection;LMWH 延後 24h or 4-6h aPTT 未正常 → caesarean 或 epidural 風險評估。
💊 Figure 6 — 妊娠 / 哺乳期藥物總圖(最常用的一張)
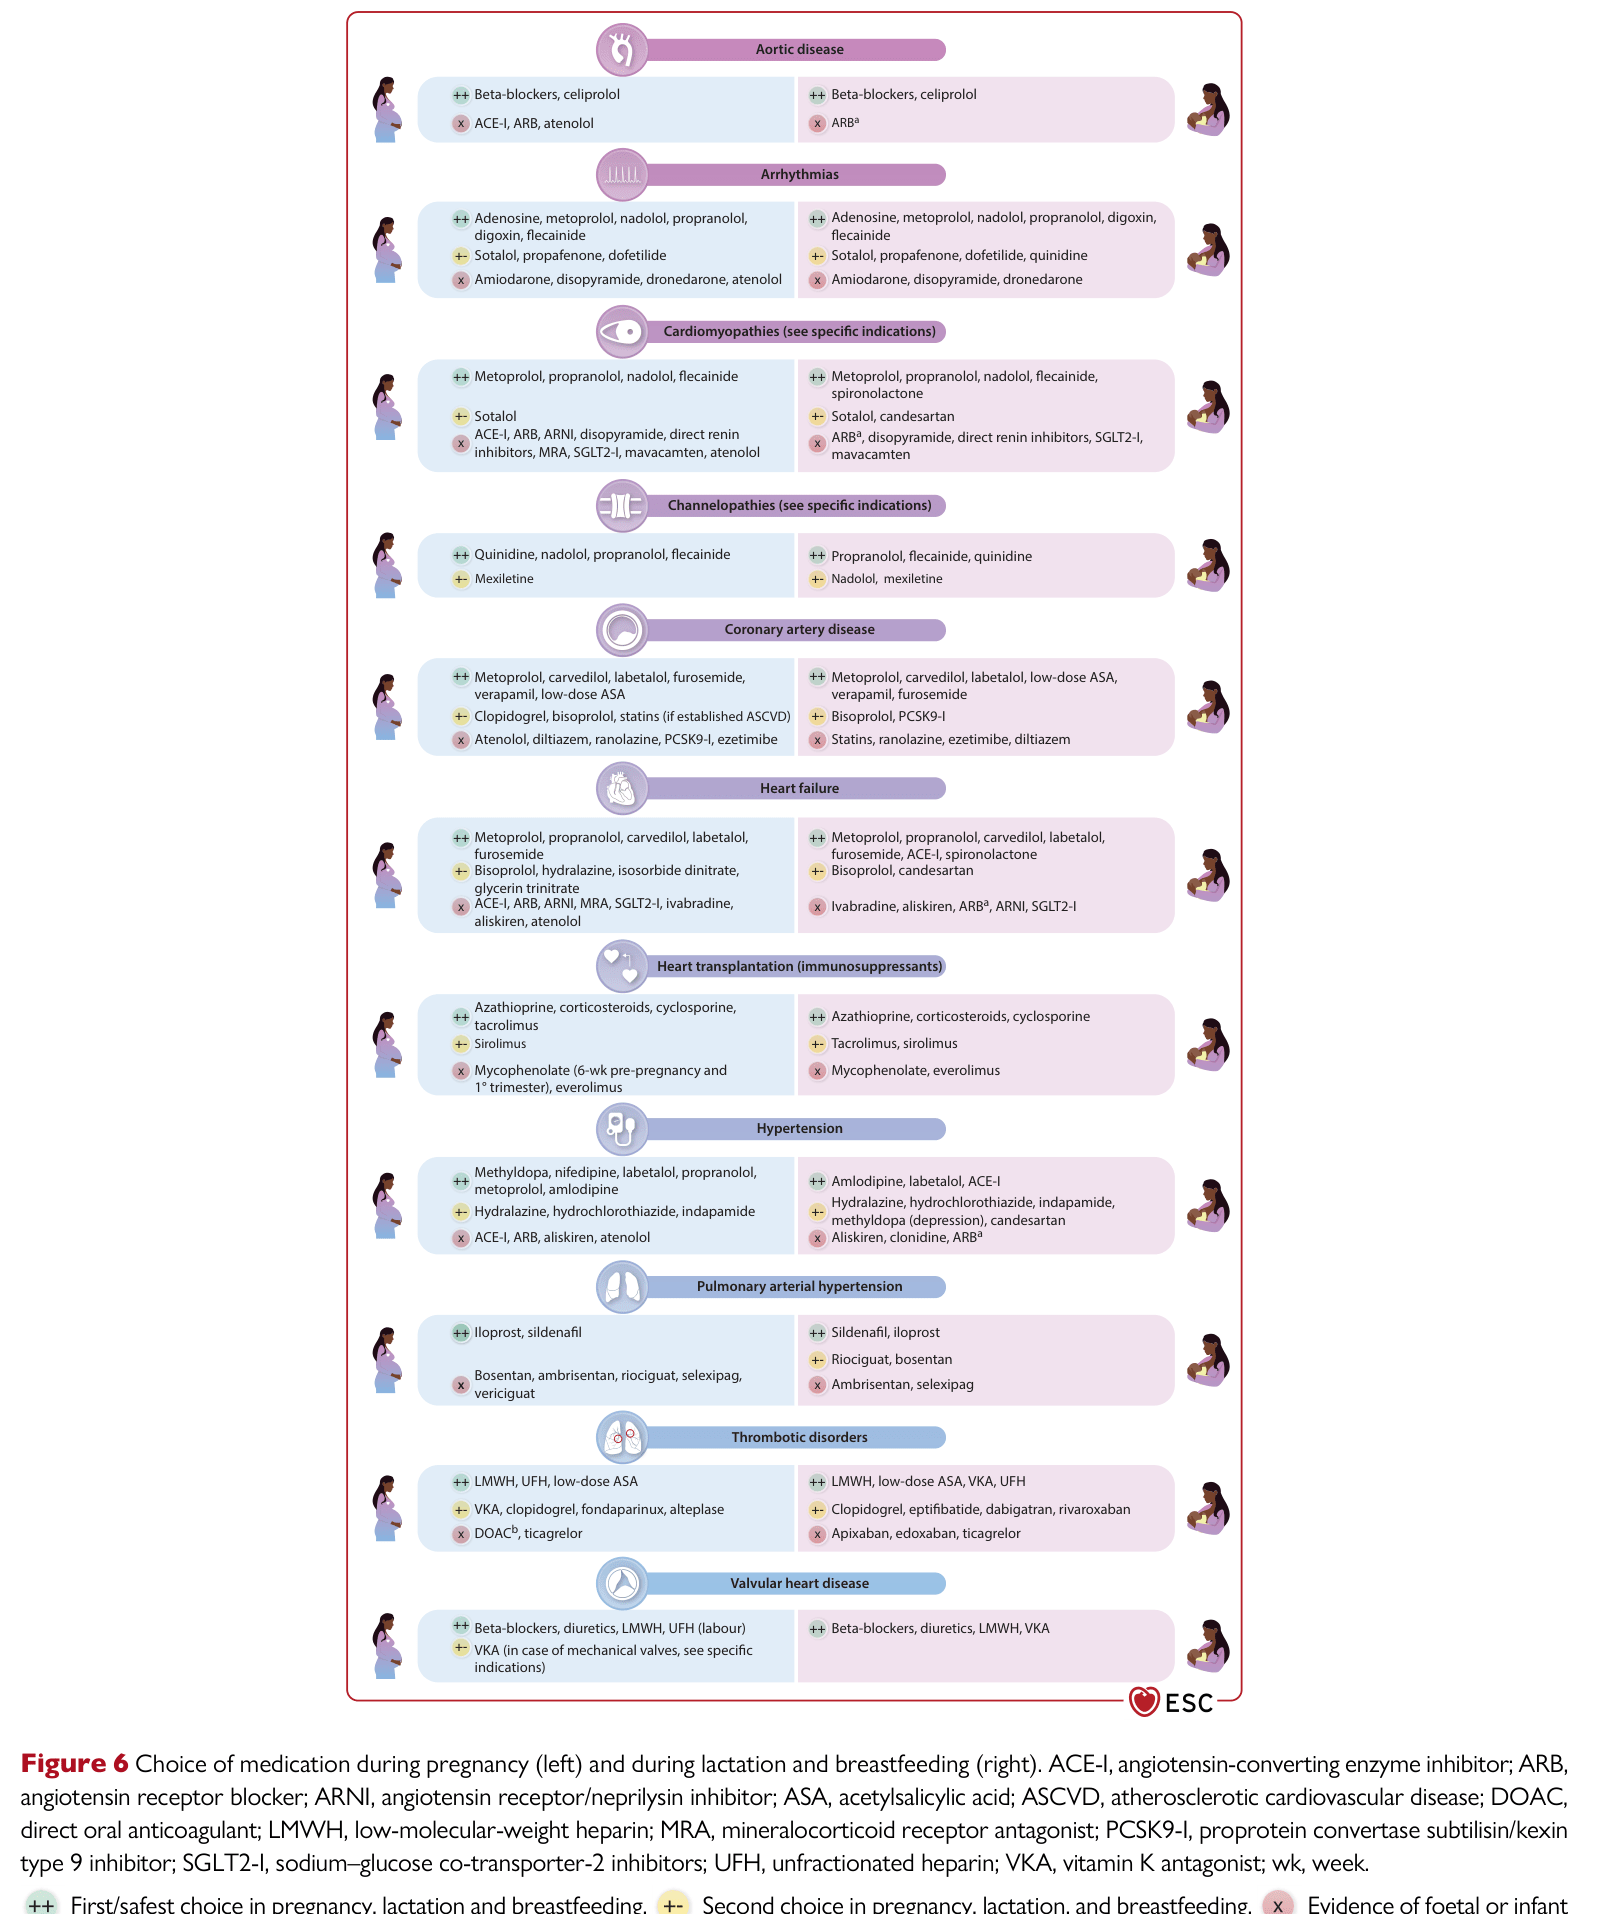
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 Figure 6 速查表(左 = 妊娠、右 = 哺乳)
2025 版把過去 2 頁的 medication 大表壓縮成一張 figure,按疾病類別 12 群,每群兩欄(pregnancy / lactation),用三色 icon:綠勾 = safest choice、藍勾 = second choice、紅叉 = avoid(fetal/infant adverse)。下表把 Fig 6 的 key 選擇翻成繁中:
| 疾病群 | 妊娠 first-line | 妊娠 avoid | Lactation 安全 |
|---|---|---|---|
| Aortic disease | β-blockers(labetalol, metoprolol) | ACEi、ARB、ARNI | β-blockers (labetalol, propranolol) |
| Cardiac channelopathies (LQTS) | nadolol、propranolol(pre-pregnancy dose) | flecainide(除非 CPVT 適應) | 同(建議繼續到 lactation) |
| CMP / HFrEF | BB(metoprolol、bisoprolol)、digoxin、HCTZ、furosemide | ACEi、ARB、ARNI、MRA、ivabradine、SGLT2i | captopril、enalapril、metoprolol、digoxin、HCTZ、furosemide、SGLT2i |
| Coronary artery disease | aspirin(low-dose)、BB、CCB(nifedipine、verapamil)、clopidogrel(with stent) | statins(unless ASCVD & high risk → IIb)、ticagrelor、prasugrel | aspirin、metoprolol、clopidogrel、statins acceptable |
| Heart transplantation | cyclosporine、tacrolimus、azathioprine、prednisone | mycophenolate(強烈致畸)、everolimus、sirolimus | tacrolimus、prednisone safe; cyclosporine acceptable |
| Hypertensive disorders | labetalol、methyldopa、nifedipine;nicardipine i.v. | ACEi、ARB(除非延誤 t1 前) | labetalol、methyldopa、nifedipine、enalapril、captopril |
| PAH | iloprost、sildenafil(個別評估) | ERA(macitentan、bosentan、ambrisentan)、riociguat | sildenafil 可考慮 |
| Thrombotic disorders | UFH、LMWH(dalteparin、enoxaparin、tinzaparin);VKA 在某些 MHV 情境 | DOAC(apixaban、rivaroxaban、edoxaban、dabigatran 都 avoid) | warfarin、UFH、LMWH safe;DOAC limited data |
| Valvular HD | VKA + anti-Xa monitoring (MHV)、LMWH (BPV) | DOACs (MHV 全禁忌) | warfarin、LMWH |
📚 內容導覽(共 6 篇)
| 篇 | 主題 | 對應章節 | 含 Figure |
|---|---|---|---|
| I(本篇) | 總論 — Pregnancy Heart Team、mWHO 2.0 與藥物總則 | §1-5 | 1, 2, 3, 4, 5, 6 |
| II | Pre-existing:CMP、Primary arrhythmia、PPCM、Aortopathies、CHD、PAH | §6-10 | 7, 8 |
| III | VTE、妊娠胸痛 / CAD、Hypertensive disorders | §11、§12.1-12.3 | 9, 10, 11, 12A, 12B, 12C |
| IV | Arrhythmias 與 Cardiac arrest | §12.4 | 13, 14, 15, 16, 17, 18, 19 |
| V | Valvular HD、HF、特殊族群(cardio-onco、heart Tx) | §12.5-12.7 | 20, 21, 22 |
| VI | §13 全新 — Adverse Pregnancy Outcomes 與 Women’s Heart Clinic | §13 | 23, 24, 25 |
📐 mWHO 2.0 速覽 — 後續分篇會反覆引用
| Class | 定義 | 例 | 追蹤頻率 | Maternal mortality risk |
|---|---|---|---|---|
| I | 沒有 detectable 升高的母體死亡風險,輕度提高 morbidity | 輕度 PS、小型 VSD/PDA、修補後 ASD、簡單 mitral valve prolapse、無 PAH 的 atrial tachycardia | 每 trimester | 2.5-5/100,000 |
| II | 輕度 maternal mortality / 中度 morbidity 風險 | 未修補的小 ASD、修補後 TOF、多數 arrhythmias | 每 trimester(或視臨床) | 5.7-7.0/100,000 |
| II-III | 中度 | 輕度 LV impairment、HCM、native或 BPV valvular HD(其他 class II/IV 範圍外) | 每 4-8 週 | — |
| III | 顯著升高 maternal mortality / morbidity | MHV、systemic RV with normal EF、Fontan with normal func、cyanotic HD(unrepaired)、其他 complex CHD | 每 1-2 個月 → 每月,最後 trimester 每 2 週 | 10-19/100,000 |
| IV | 極高 maternal mortality + morbidity,妊娠原則上不建議但PHT shared decision-making | PAH(任何原因)、severe systemic ventricular dysfunction(LVEF <30% / NYHA III-IV)、prior PPCM with residual LV impairment、severe MS、severe symptomatic AS、systemic RV with moderate-severe dysfunction、severe aortic dilation(Marfan >45 mm, BAV >50 mm, LDS >42 mm, TS ASI >25 mm/m²)、severe (re)coarctation、vEDS | 每月(最複雜的每 2 週) | 40-100/100,000 |
- 2025 ESC CVD & Pregnancy 是大改版:Pregnancy Heart Team 升為獨立章節並強制 mWHO II–III+ 使用;mWHO IV 從 COR III 改為「PHT 主導 shared decision-making」I C。
- §13 全新章節:APO(HDP、GDM、SGA、preterm 等)是 future CV risk 的強力 modifier,所有有 APO 史的女性都該做 risk assessment + lifestyle counselling I B,並建立 Women’s Heart Clinic 制度。
- 藥物總則:Figure 6 一張圖整理 12 類疾病的 first-line / avoid;HFrEF 的 ACEi、ARB、ARNI、MRA、ivabradine、SGLT2i 全部禁忌;DOAC 全類別禁忌。
- Pre-conception genetic testing:aortic disease 高 yield 高 impact(決定手術閾值與產式);CMP / channelopathy 中度;CHD / PAH 低 yield 但仍應考慮 recurrence risk。
- 新增 cardiac arrest in pregnancy(manual uterine displacement、IV access above diaphragm、不為 teratogenicity 顧慮停藥)、HDP BP target <140/90、HTAD gene-based surgical threshold。
📖 References(主要引用試驗與指引)
- De Backer J, Haugaa KH, Hasselberg NE, et al. 2025 ESC Guidelines for the management of cardiovascular disease and pregnancy. Eur Heart J 2025;46(43):4462–4568. doi:10.1093/eurheartj/ehaf193 | PMID: 40878294
- Regitz-Zagrosek V, Roos-Hesselink JW, Bauersachs J, et al. 2018 ESC Guidelines for the management of cardiovascular diseases during pregnancy. Eur Heart J 2018;39(34):3165–3241. doi:10.1093/eurheartj/ehy340
- Tita AT, Szychowski JM, Boggess K, et al. Treatment for Mild Chronic Hypertension during Pregnancy (CHAP). N Engl J Med 2022;386:1781–1792. doi:10.1056/NEJMoa2201295
- Roos-Hesselink JW, Ruys TPE, Stein JI, et al. Outcome of pregnancy in patients with structural or ischaemic heart disease: results of a registry of the European Society of Cardiology (ROPAC). Eur Heart J 2013;34:657-665.
- Peters PNJ, van der Zande JA, De Backer J, et al. Pregnancy outcomes in women with heritable thoracic aortic disease: data from ROPAC III. Eur Heart J Qual Care Clin Outcomes 2025;11(7):1091-1107. doi:10.1093/ehjqcco/qcaf038
- Hilfiker-Kleiner D, Haghikia A, Berliner D, et al. Bromocriptine for the treatment of peripartum cardiomyopathy: a multicentre randomized study (BB-EFFECT). Eur Heart J 2017;38:2671-2679.
- Parikh NI, Gonzalez JM, Anderson CAM, et al. Adverse Pregnancy Outcomes and Cardiovascular Disease Risk: AHA Scientific Statement. Circulation 2021;143(18):e902-e916.
本文以教學為目的整理 2025 ESC Guidelines for the management of cardiovascular disease and pregnancy;所有原文 Figure 之版權屬 ESC。商業使用請洽 ESC 取得授權。
