

- 四種 AF 型態對應 4 張 pathway figure:first-diagnosed → Fig 4,paroxysmal → Fig 5,persistent → Fig 6,permanent → Fig 7。共通起手是先做 [C][A],然後依 LVEF(>40% vs ≤40%)切 rate control 用藥。
- Rate control 哲學定型:Lenient(<110 bpm)為一線(RACE II 之後不變),strict(<80 bpm)保留給 lenient 仍症狀者;初始 rate control 是 I C;用藥選擇看 LVEF:>40% → β-blocker / digoxin / diltiazem / verapamil;≤40% → β-blocker / digoxin(diltiazem/verapamil III 在 HFrEF)。
- Rhythm control 大躍進:Catheter ablation 升 paroxysmal AF first-line I A;persistent AF 仍 IIa B/A first-line(依風險因子);HFrEF + AF 的 ablation 升為 I B(CASTLE-AF);早期介入(<12 個月) IIa B(EAST-AFNET 4)。
- Cardioversion 流程整合到 Figure 12:Wait-and-see <48h IIa B(RACE 7 ACWAS);<3 週未抗凝 + AF onset >24h → TOE-guided cardioversion;post-cardioversion 抗凝至少 4 週(>65y 或 CHA2DS2-VA ≥1 終生)。
📐 §7.1 Rate Control — 從 RACE II 到 2024
Lenient vs Strict — 為什麼 <110 還是主流
RACE II 試驗(NEJM 2010)611 名 permanent AF 病人,隨機分 lenient(resting HR <110 bpm)vs strict(resting HR <80 bpm + 中等運動 <110 bpm)。3 年 primary composite endpoint(CV death、HF hospitalization、stroke、systemic embolism、life-threatening arrhythmia、major bleed)兩組相當(12.9% vs 14.9%)。Lenient 組所需藥物較少、QoL 相當。
2024 版繼續 lenient 為主:
| 建議 | COR/LOE |
|---|---|
| Rate control therapy 作為初始 / 輔助 / 單一策略 — 控 HR 並減症狀 | I B |
| Lenient target:resting HR <110 bpm | I C |
| Strict target(<80 bpm):lenient 仍有症狀者 | IIa C |
用藥選擇看 LVEF
| LVEF | 首選 | 第二選 | 禁忌 |
|---|---|---|---|
| >40%(含正常) | β-blocker、diltiazem、verapamil 任一 | Digoxin(合併或單獨) | — |
| ≤40%(HFrEF) | β-blocker(bisoprolol、carvedilol、metoprolol succinate、nebivolol) | Digoxin(合併或單獨) | Diltiazem、Verapamil III(負性 inotropic) |
Digoxin — 不是 obsolete,但要小心 level
- Digoxin 在現代 RCT 較少,但實務上仍有三種角色:(1) β-blocker 不夠時的 add-on;(2) HFrEF + AF 控 rate 又控 HF;(3) hypotensive 不能用 β-blocker / CCB 的患者。
- 劑量:起始 0.125-0.25 mg PO daily;老年、CKD 減量。
- Target digoxin level:0.5-0.9 ng/mL(不是 >1.0;後者觀察性數據顯示死亡率上升)。
- 避免:CrCl <30 mL/min 慎用;P-gp 互動藥(amiodarone、verapamil、cyclosporine)需減量。
AV node ablation + CRT — 救援策略升級
| 建議 | COR/LOE |
|---|---|
| 嚴重症狀 + permanent AF + 至少 1 次 HF 住院 → AV node ablation + CRT | IIa B(新加) |
APAF-CRT 試驗(Eur Heart J 2018, 2022)顯示 AV node ablation + CRT 對 permanent AF + HF 嚴重症狀者降低全因死亡 HR ~0.26(74% reduction)。是「藥物已力不足心」的救援。
🖼️ Figure 4 — Pathway for first-diagnosed AF
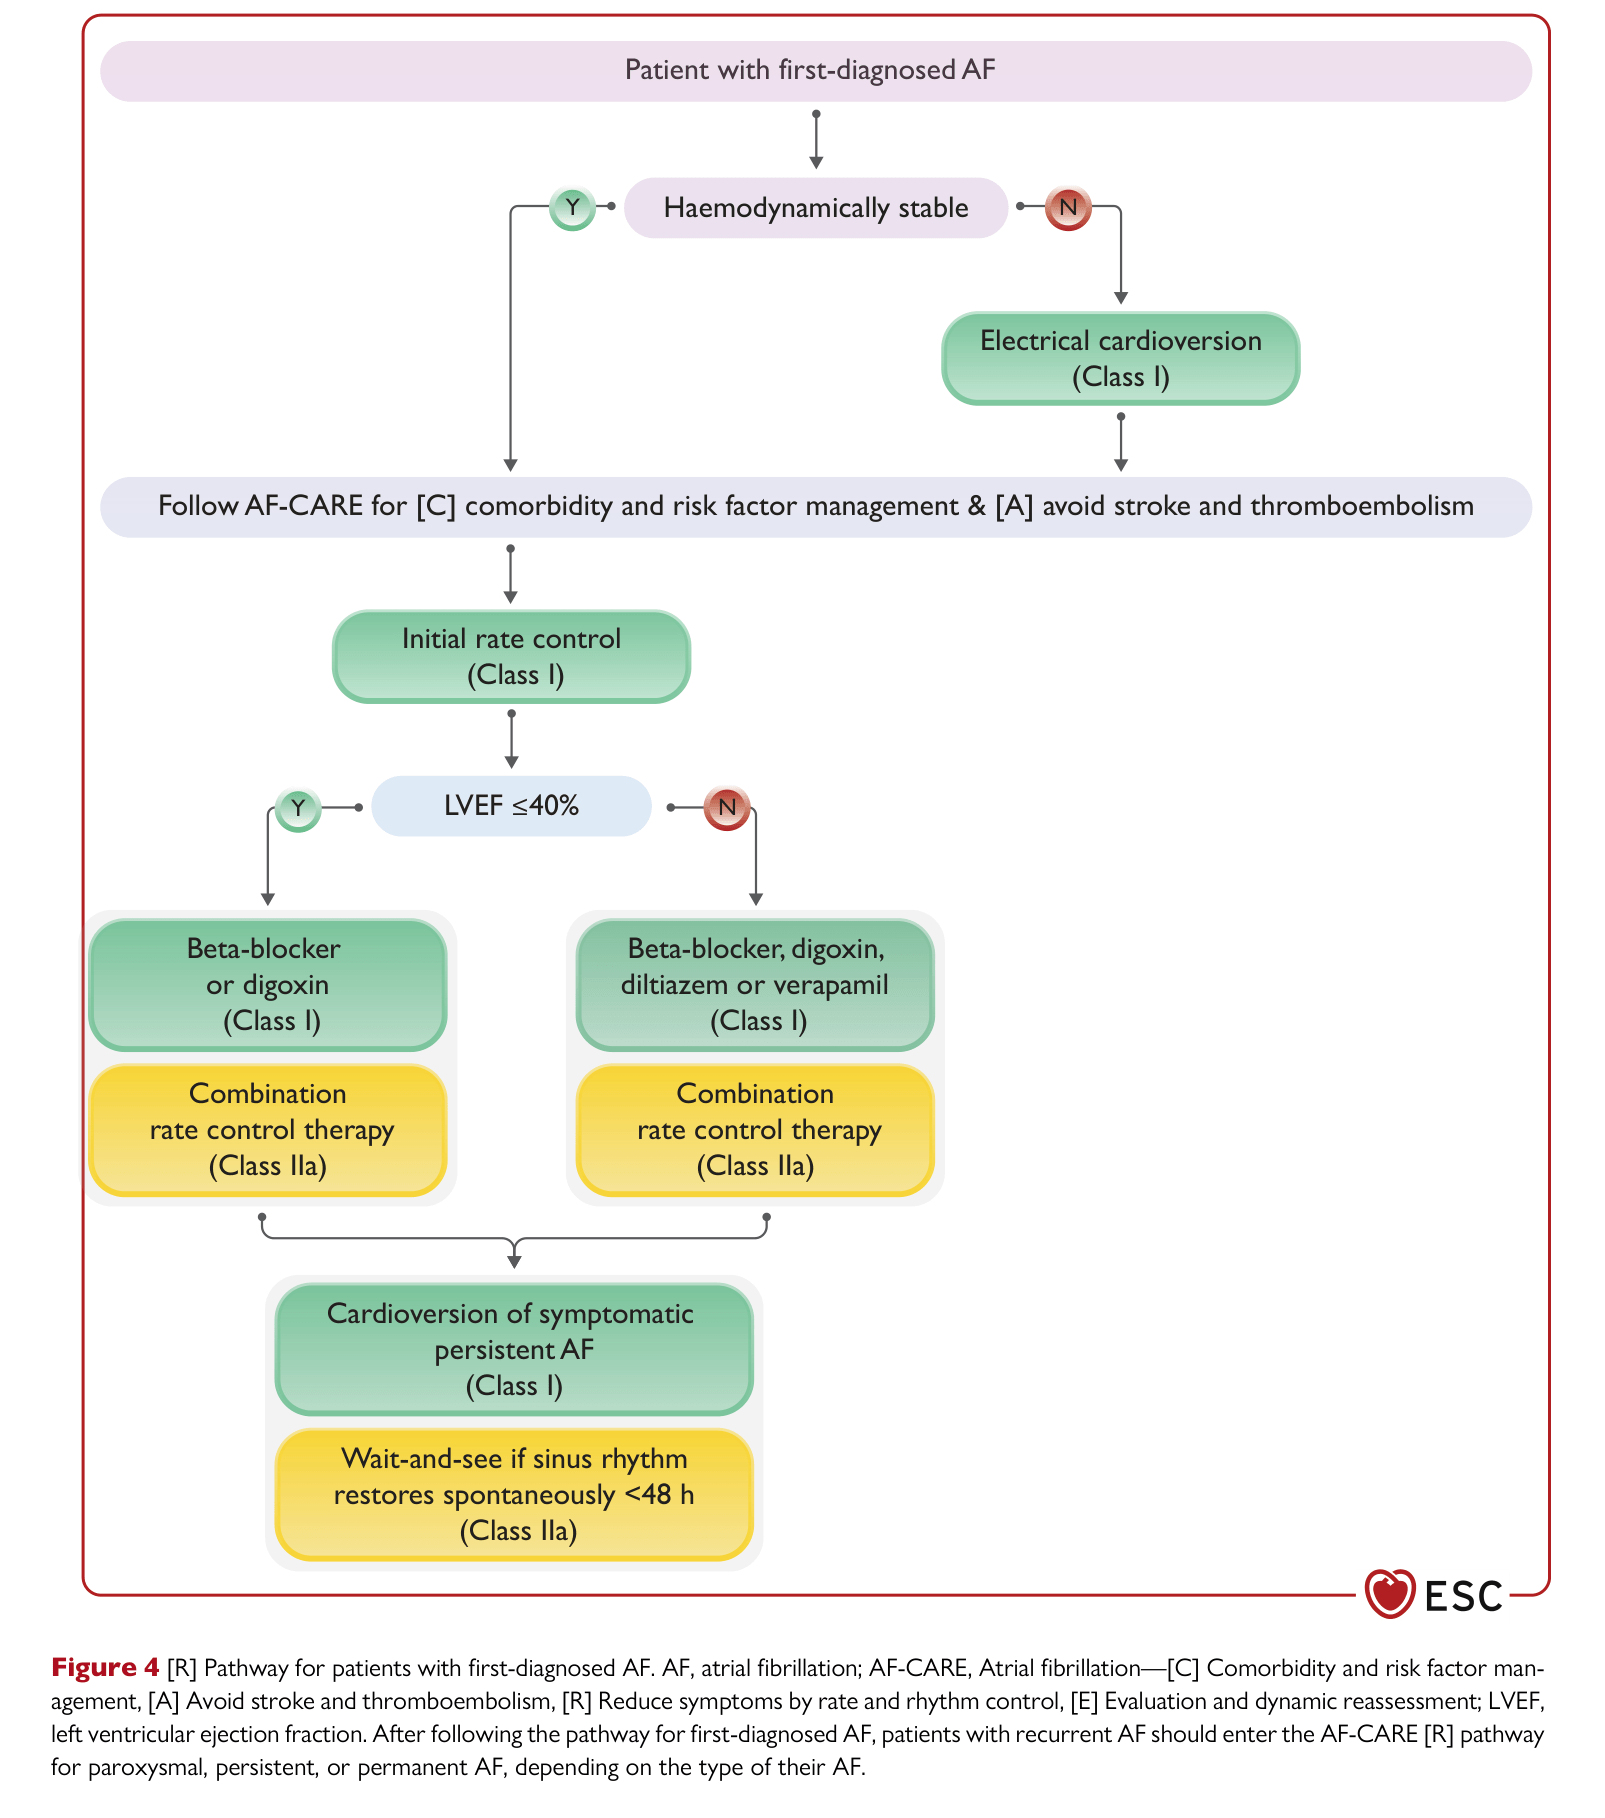
來源:2024 ESC Guidelines for the management of atrial fibrillation (Eur Heart J, doi:10.1093/eurheartj/ehae176) — 個人教學使用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 4
這張圖在回答什麼問題:第一次診斷 AF 的病人,如何快速分流到對的處置?
逐步走完:
容易踩雷的地方:
🖼️ Figure 5 — Pathway for paroxysmal AF
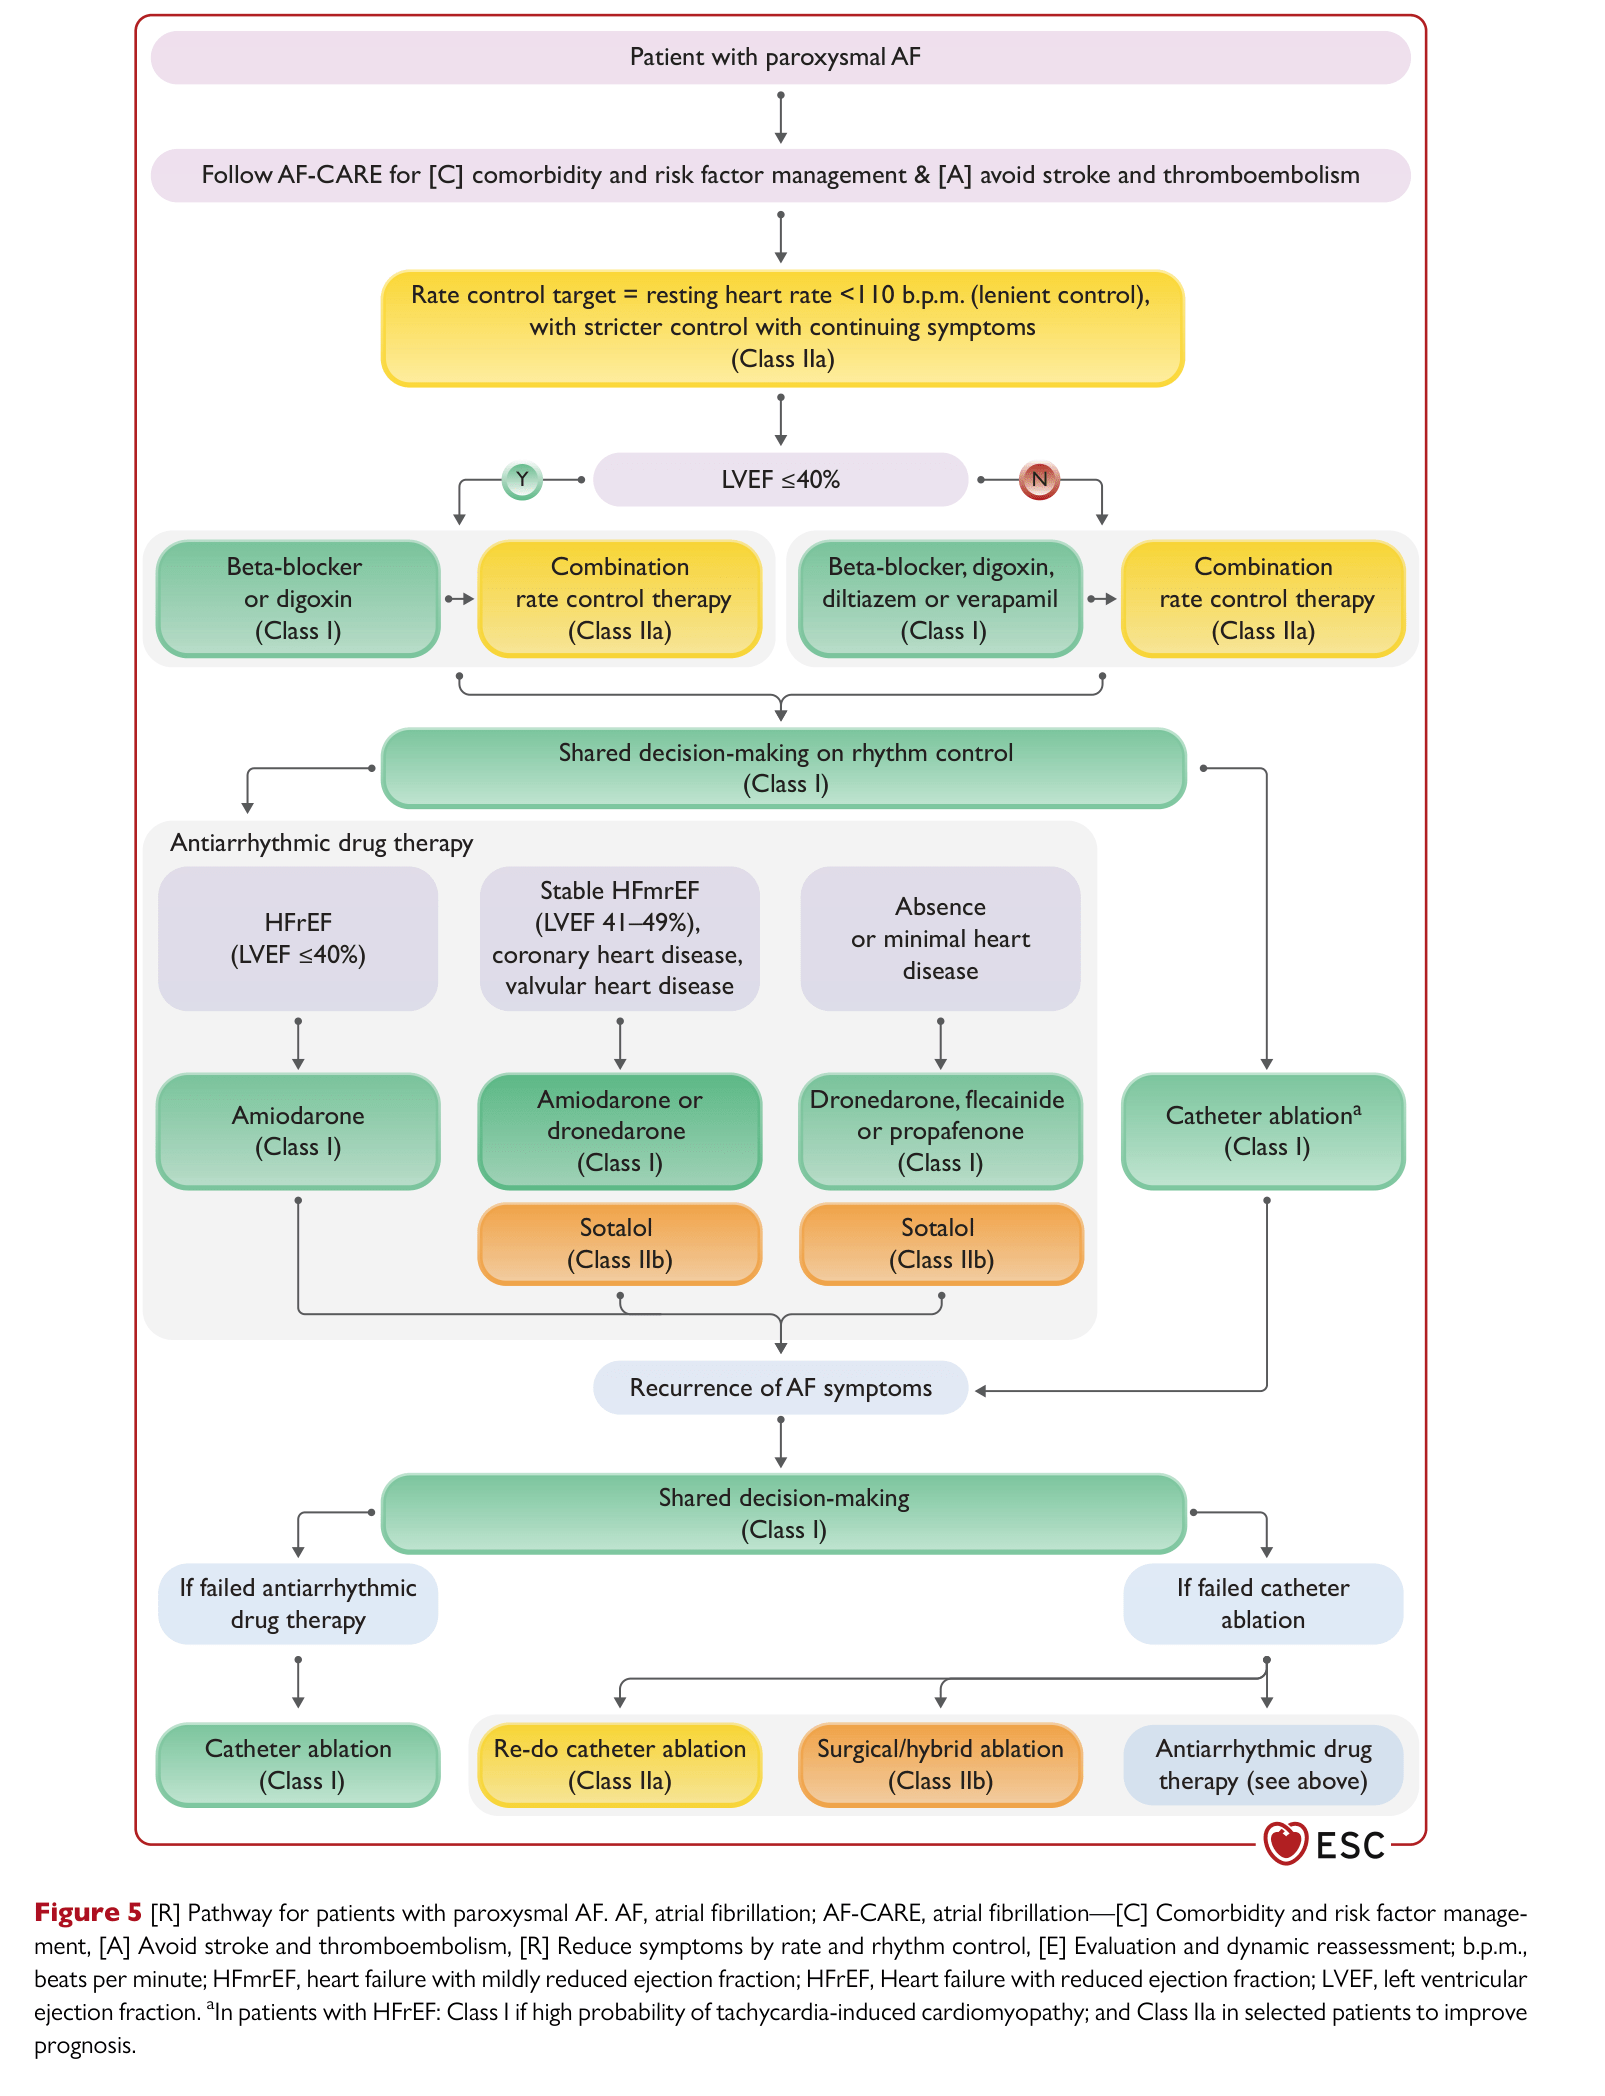
來源:2024 ESC Guidelines for the management of atrial fibrillation (Eur Heart J, doi:10.1093/eurheartj/ehae176) — 個人教學使用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 5
這張圖在回答什麼問題:確診 paroxysmal AF 後,如何選 rate vs rhythm control,rhythm control 該選什麼策略?
逐步走完:
| 族群 | 首選 AAD | 備註 |
|---|---|---|
| HFrEF(LVEF ≤40%) | Amiodarone I | 唯一安全的 AAD;dofetilide 在台灣多無供應 |
| Stable HFmrEF(LVEF 41-49%)/ coronary heart disease / valvular heart disease | Amiodarone 或 dronedarone I | — |
| Absence of minimal heart disease | Dronedarone、flecainide 或 propafenone I | Class 1C 藥物可考慮 pill-in-pocket 策略 |
| 進階替代 | Sotalol IIb | QT prolongation 風險,monitoring |
容易踩雷的地方:
🖼️ Figure 6 — Pathway for persistent AF
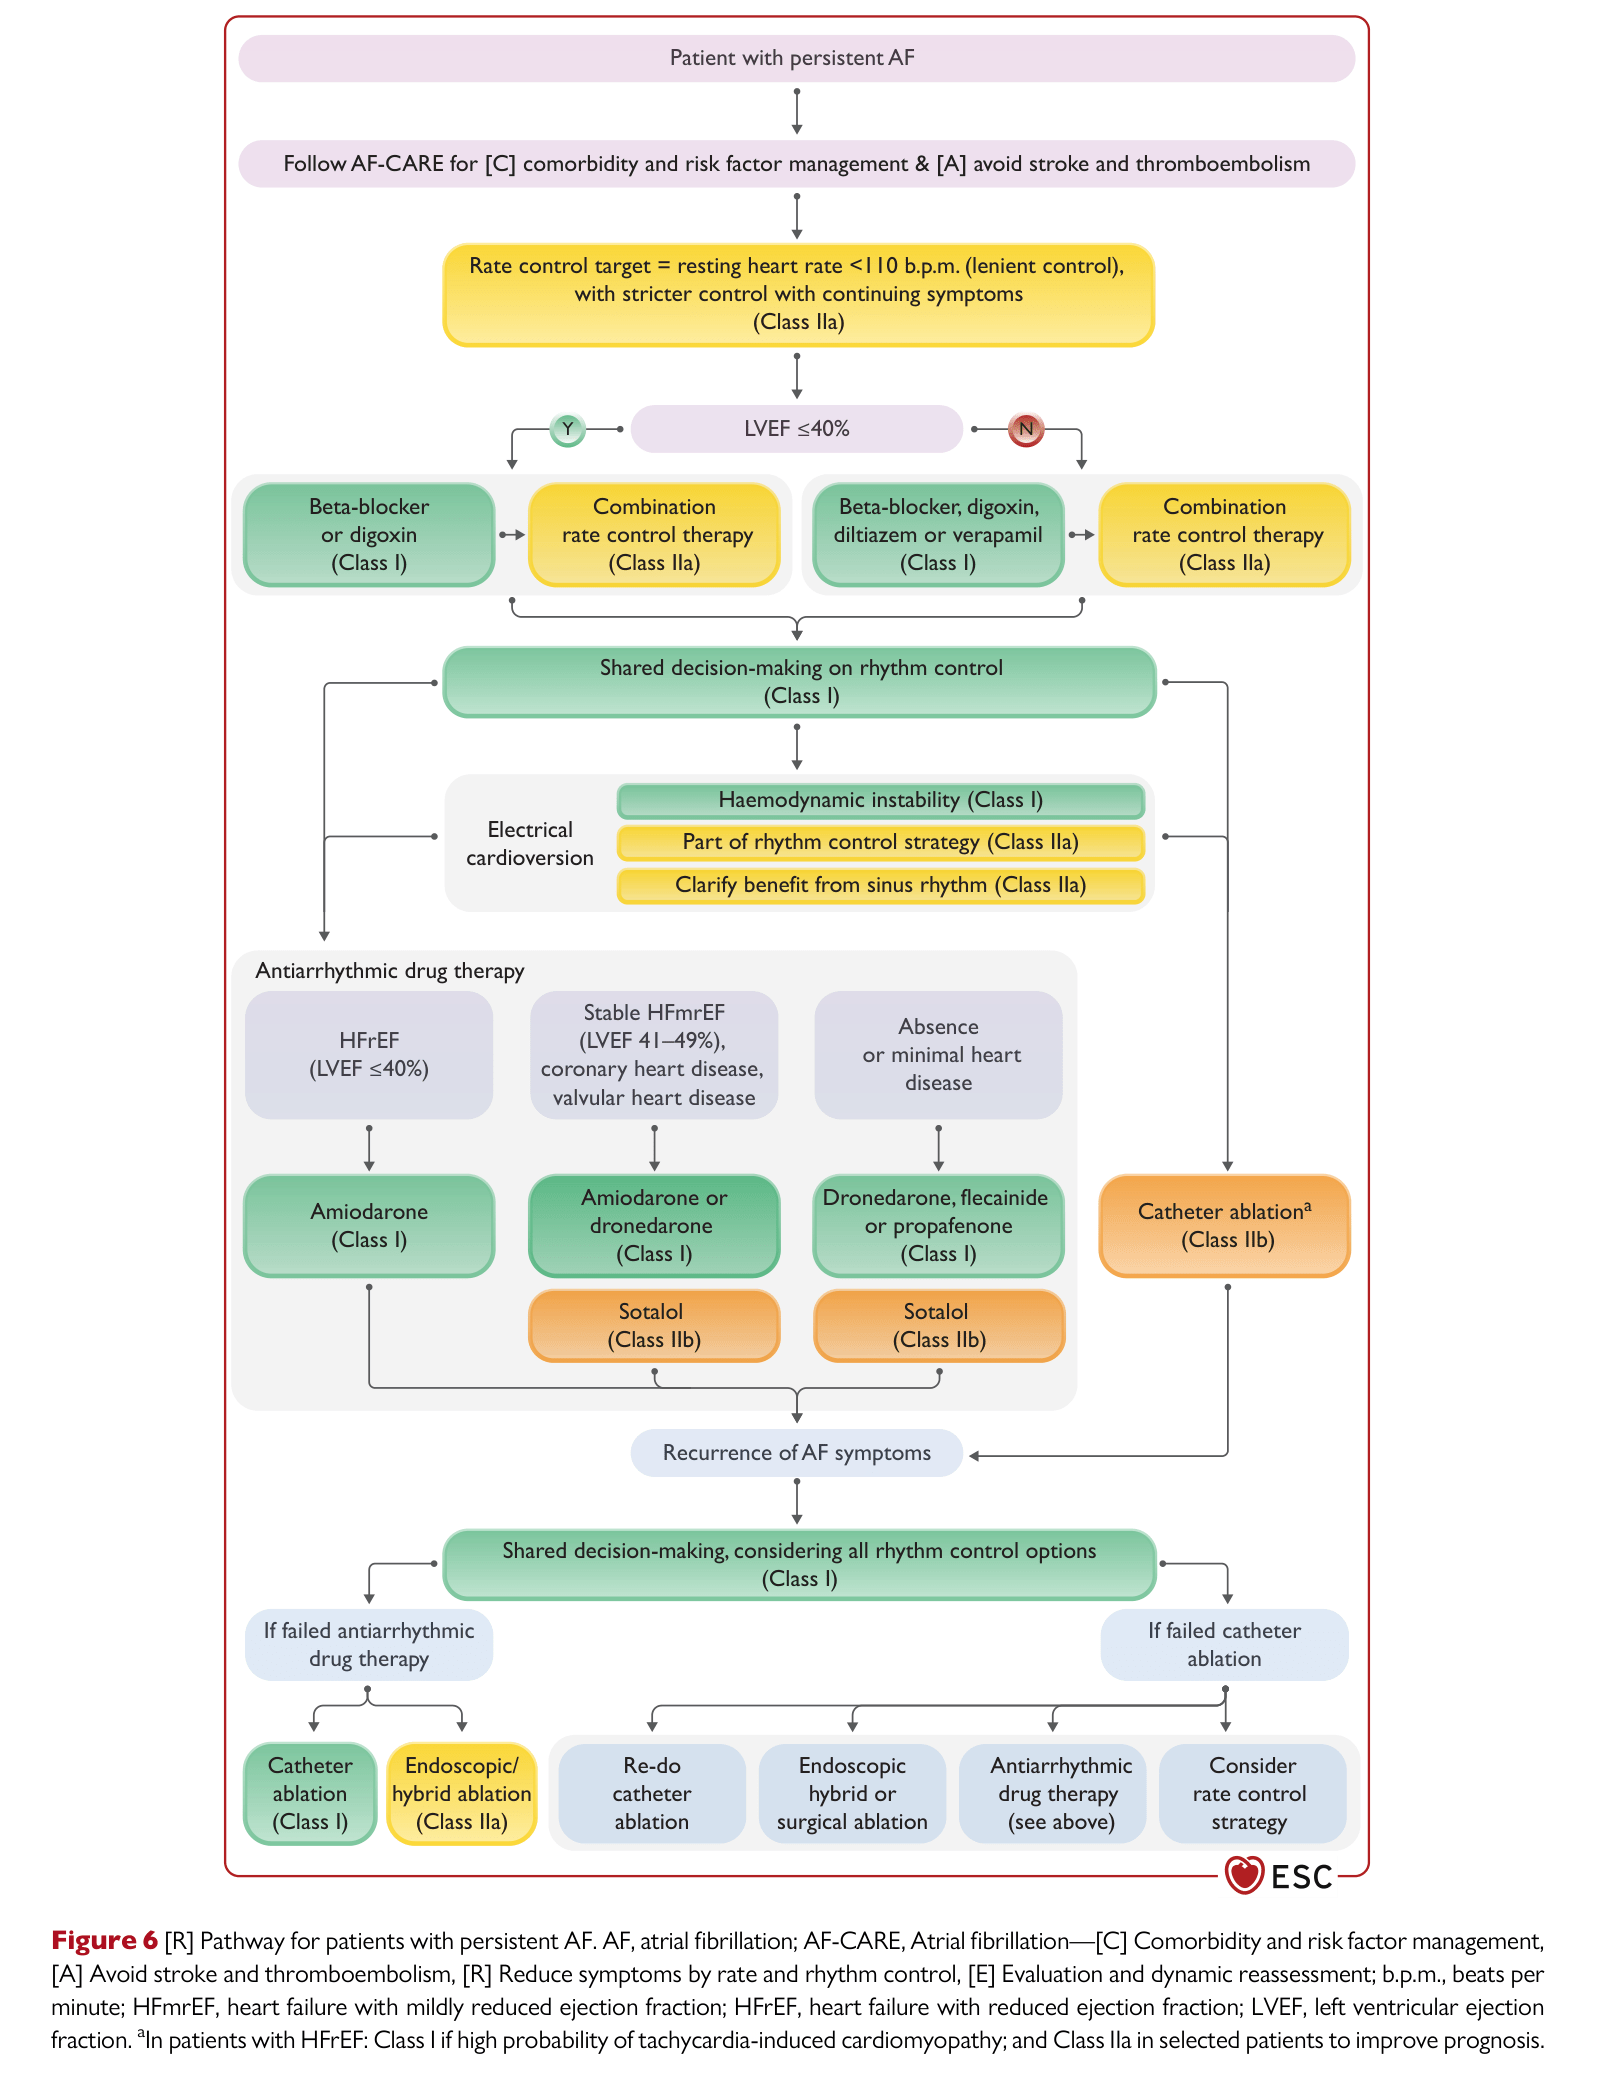
來源:2024 ESC Guidelines for the management of atrial fibrillation (Eur Heart J, doi:10.1093/eurheartj/ehae176) — 個人教學使用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 6
這張圖在回答什麼問題:Persistent AF(>7 天 或需 cardioversion 才能轉復),rhythm control 策略如何分層?
逐步走完:
容易踩雷的地方:
🖼️ Figure 7 — Pathway for permanent AF
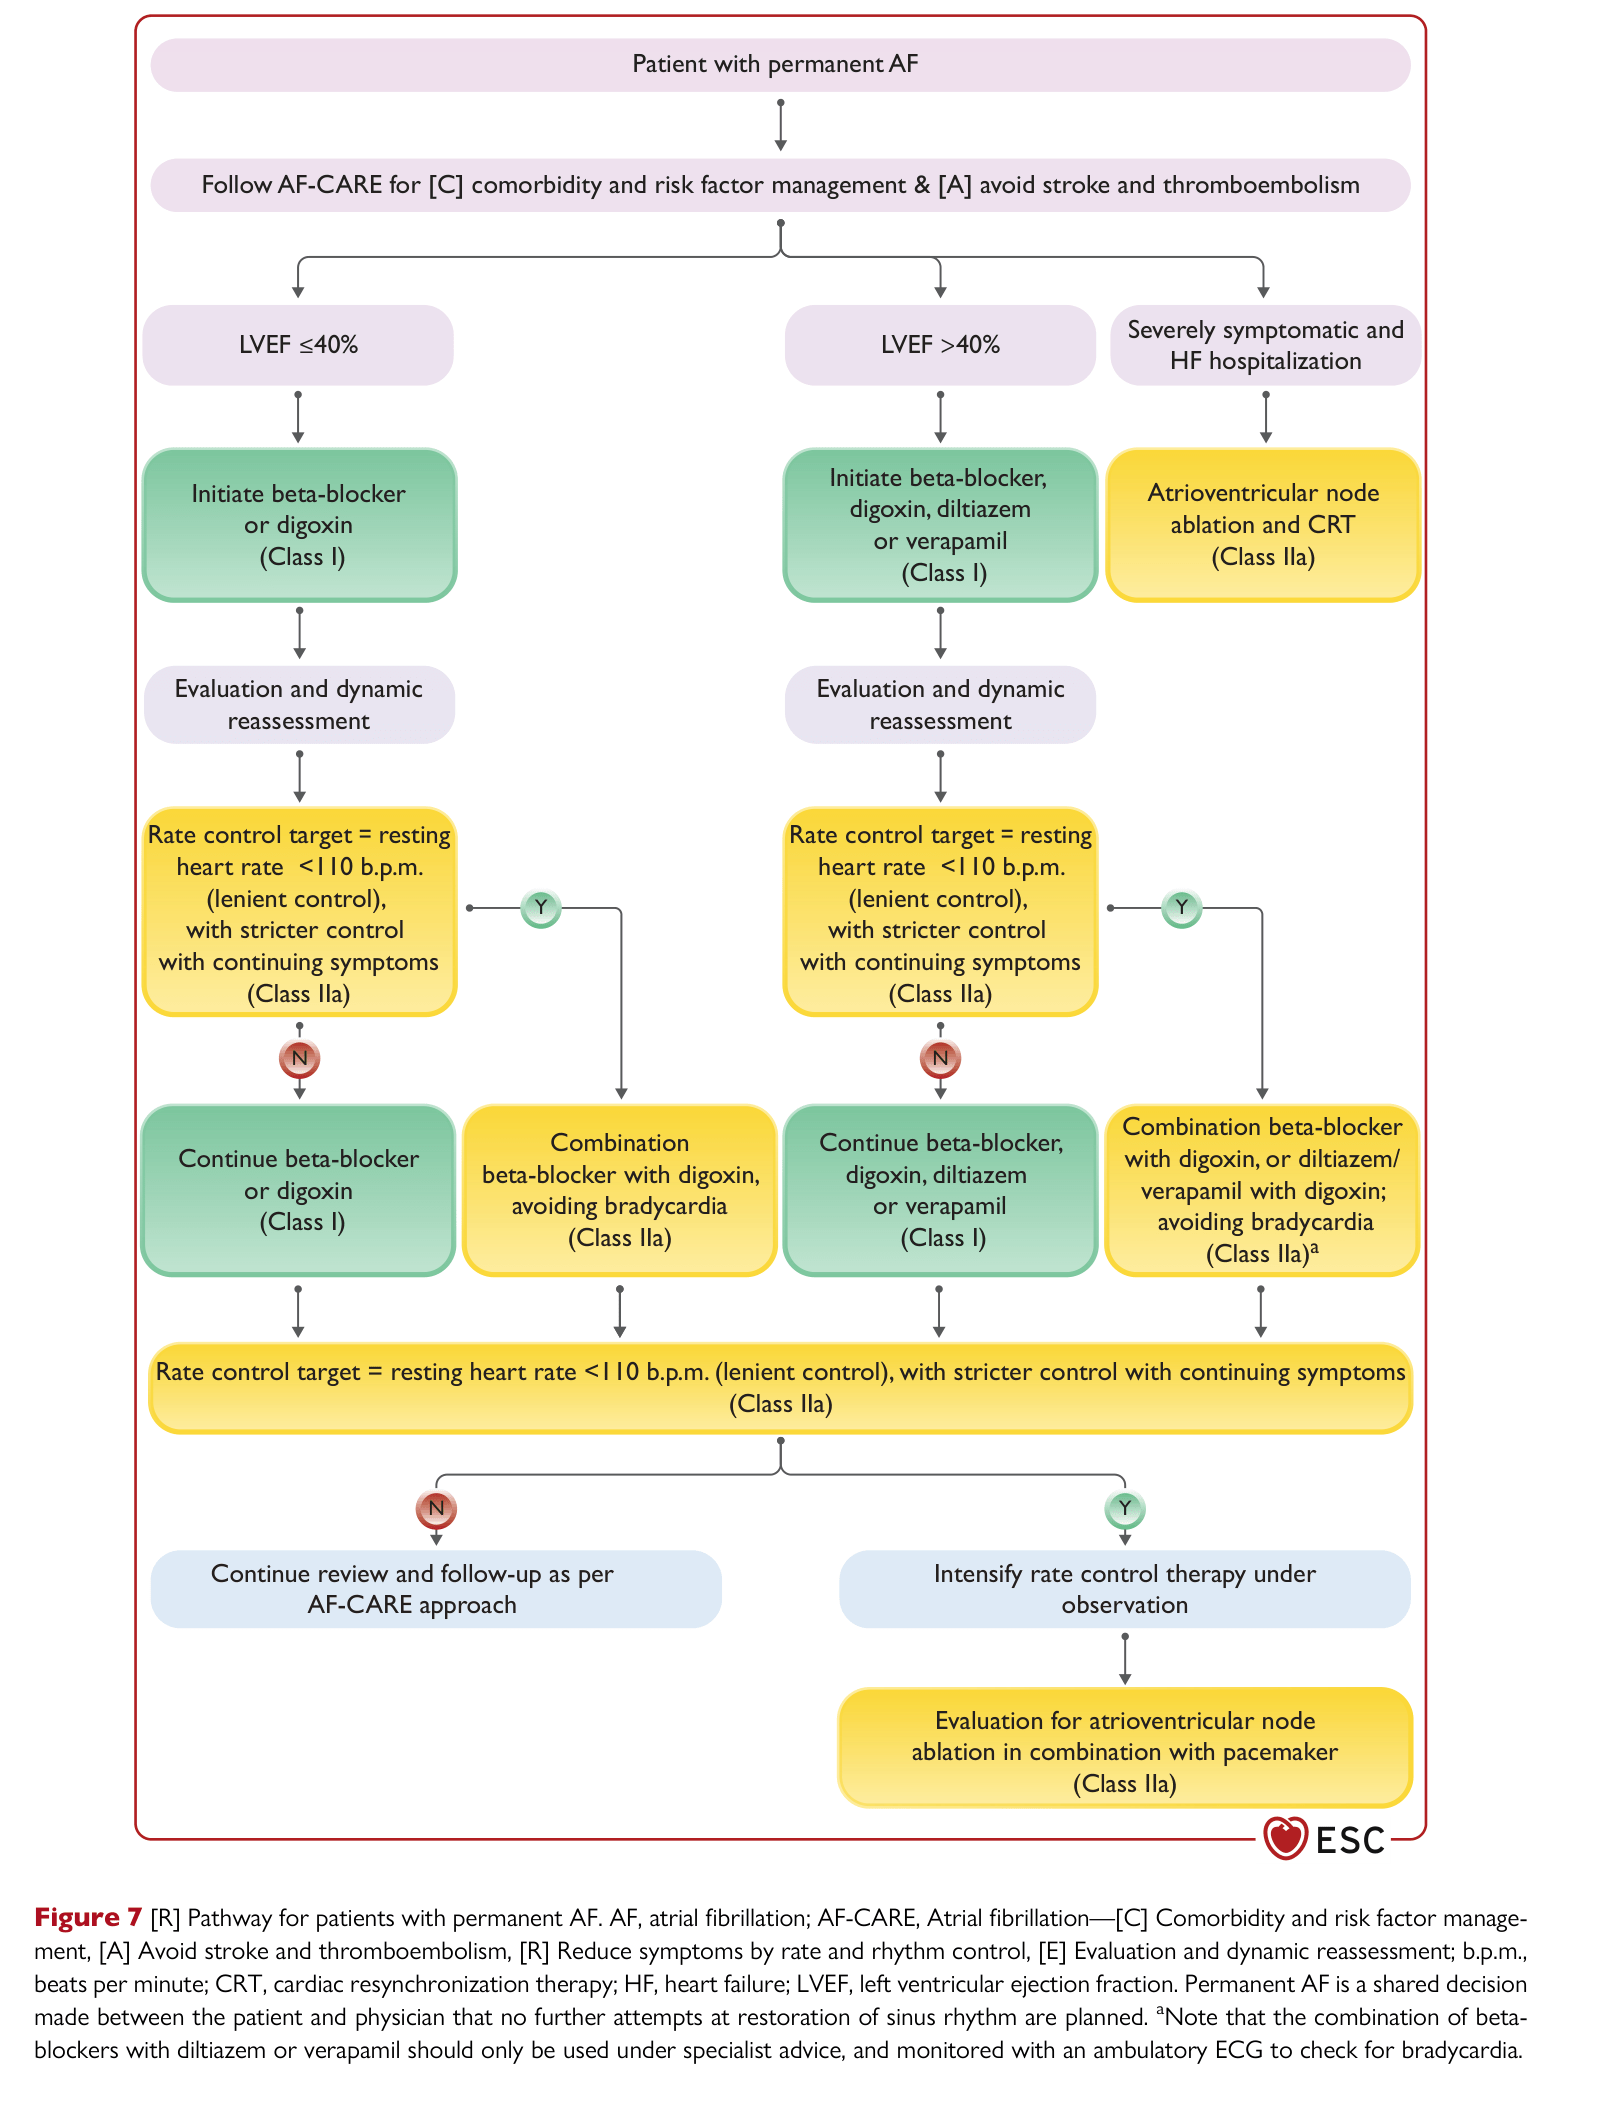
來源:2024 ESC Guidelines for the management of atrial fibrillation (Eur Heart J, doi:10.1093/eurheartj/ehae176) — 個人教學使用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 7
這張圖在回答什麼問題:已決定 permanent AF(不再嘗試 rhythm control 的「治療決策」)的病人,後續如何用 rate control 管下去?
逐步走完:
- LVEF >40%:初始 β-blocker、digoxin 或 verapamil(注意 verapamil 在 >40% 可,diltiazem 也可)I。
- LVEF ≤40%:初始 β-blocker、digoxin I(不可 verapamil/diltiazem)。
- Severely symptomatic + HF hospitalization → 立即考慮 AV node ablation + CRT IIa。
- LVEF >40% combination:β-blocker + digoxin、diltiazem 或 verapamil IIa — avoiding bradycardia。
- LVEF ≤40% combination:β-blocker + digoxin IIa — avoiding bradycardia。
容易踩雷的地方:
📐 §7.2 Rhythm Control — Cardioversion、AAD、Catheter Ablation
1. 早期 rhythm control 的證據(EAST-AFNET 4)
EAST-AFNET 4(NEJM 2020)2,789 名 AF 確診 <12 個月 + CV 風險者,隨機分 early rhythm control(AAD 或 ablation)vs usual care。5 年 primary composite(CV death、stroke、HF hospitalization、ACS hospitalization):HR 0.79(95% CI 0.66-0.94, p=0.005),absolute RR ~1.1% per year。
| 建議 | COR/LOE |
|---|---|
| Implementation of rhythm control within 12 months of diagnosis | IIa B(新加) |
2. Cardioversion — Figure 12 的整合流程
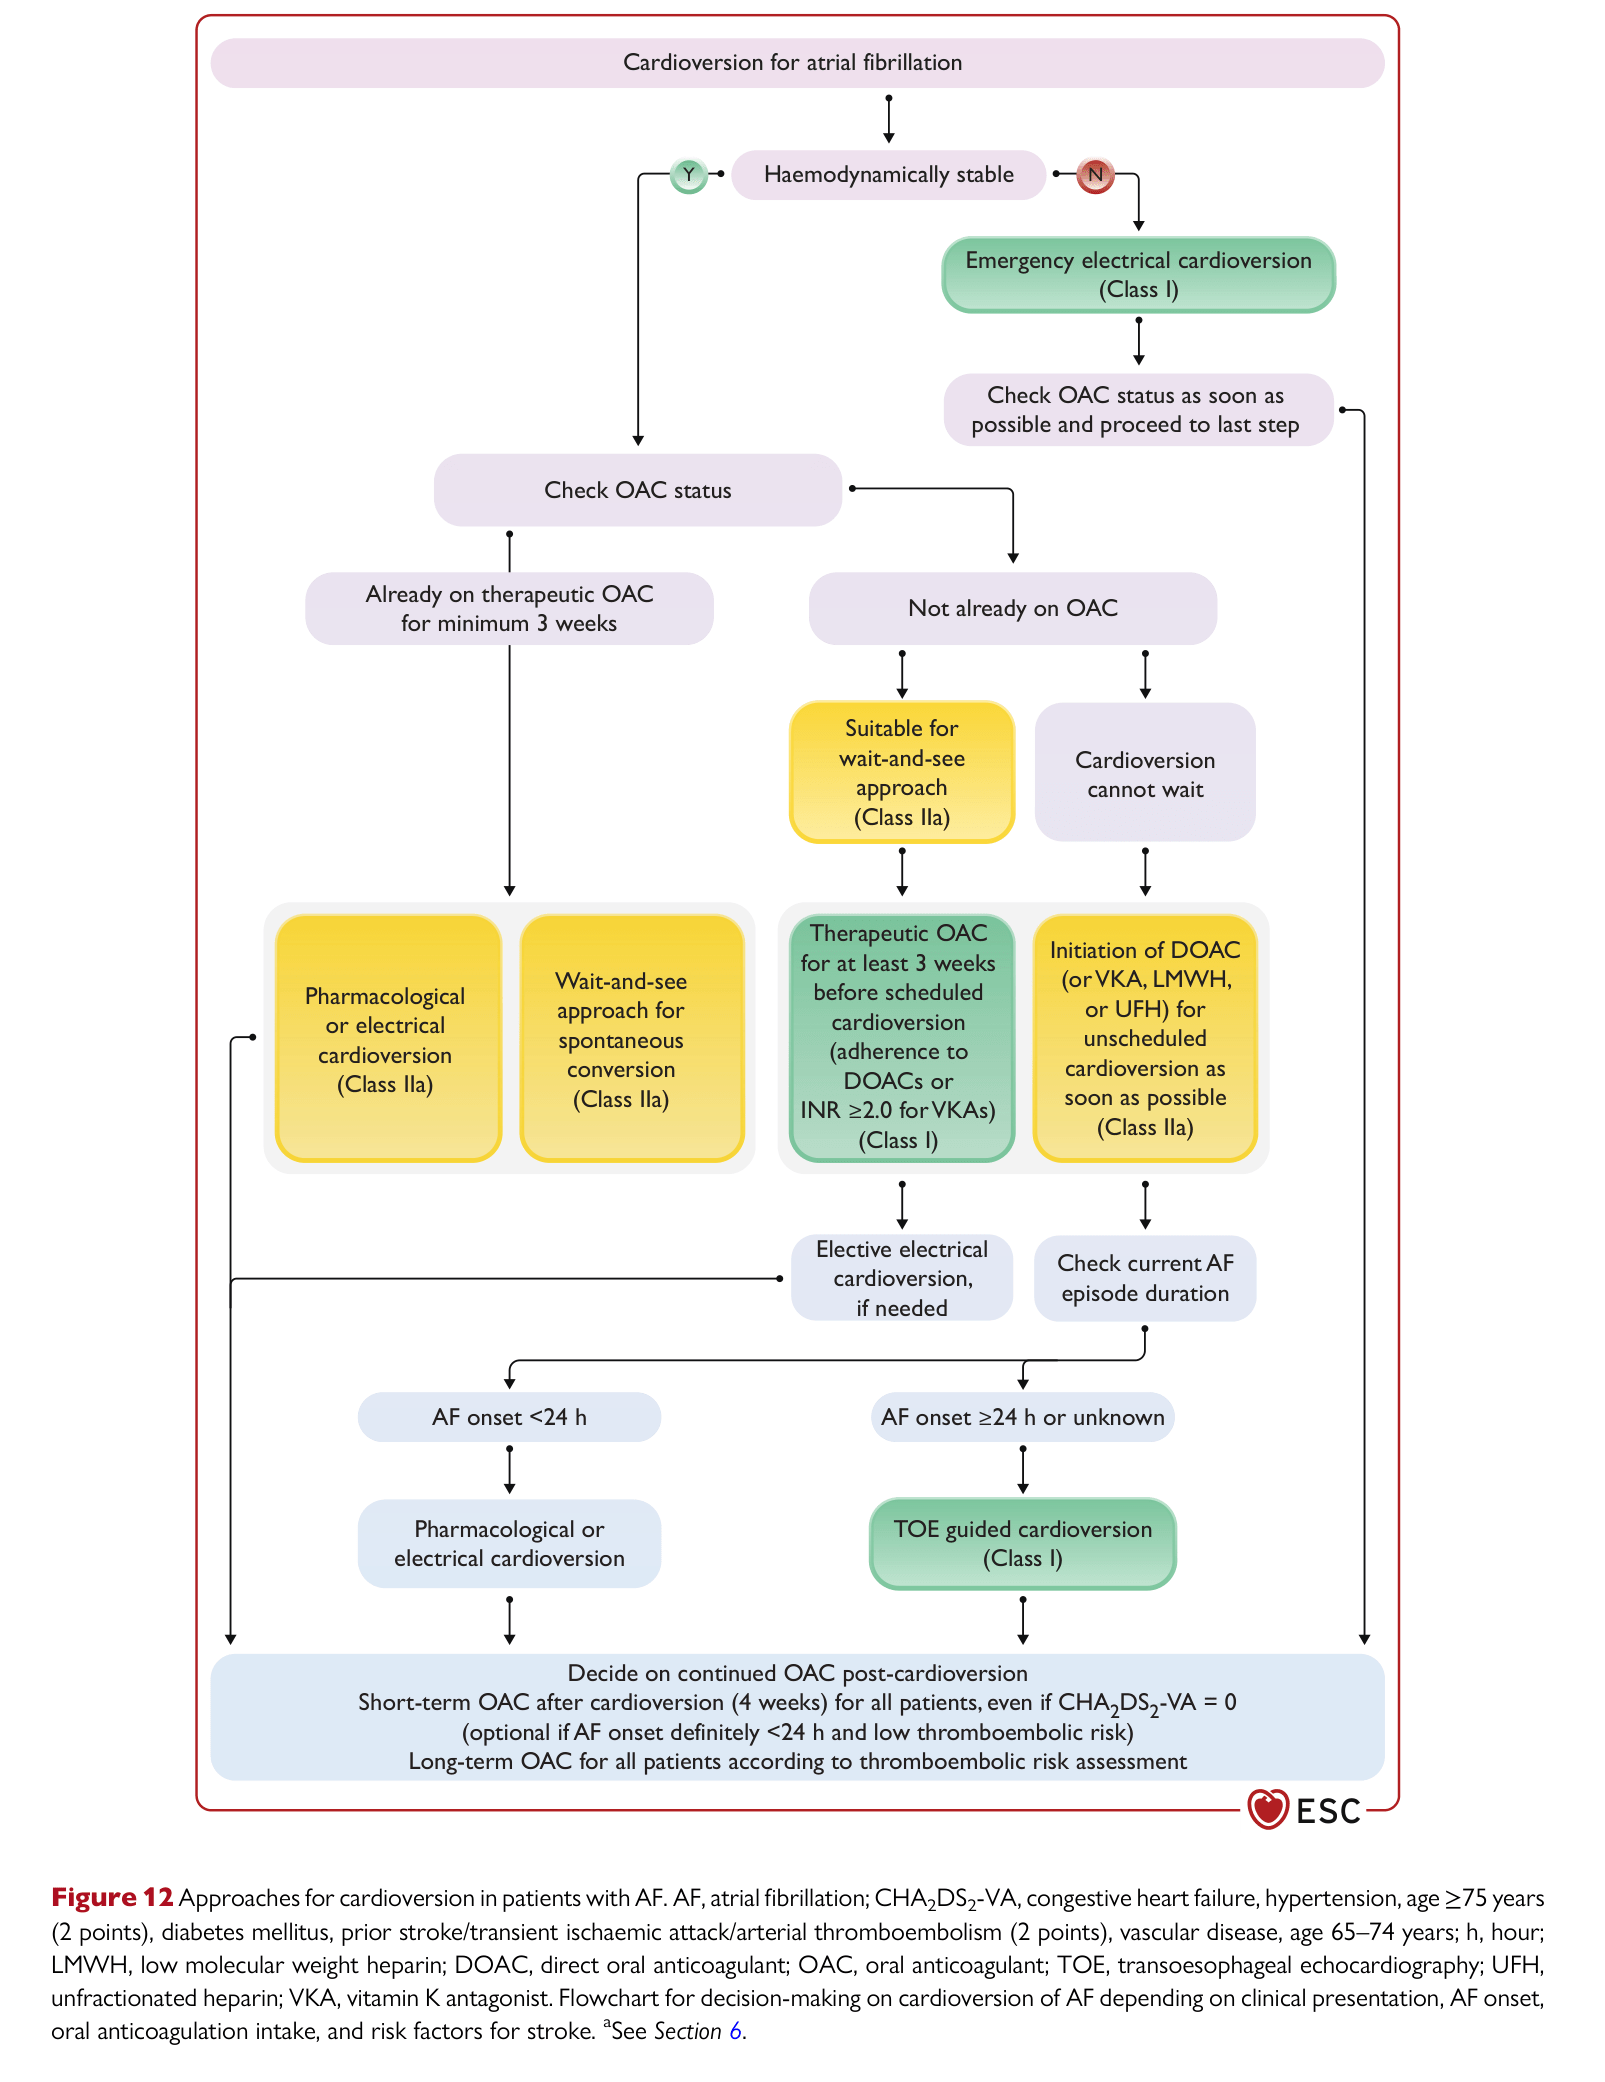
來源:2024 ESC Guidelines for the management of atrial fibrillation (Eur Heart J, doi:10.1093/eurheartj/ehae176) — 個人教學使用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 12
這張圖在回答什麼問題:要做 cardioversion 的 AF 病人,如何依血流動力學、OAC 狀態、AF 持續時間決定路徑?
逐步走完:
- 不穩定(紅燈)→ Emergency electrical cardioversion I,同時 check OAC status as soon as possible and proceed to last step。
- 穩定(綠燈)→ 進 Step 3。
- Already on therapeutic OAC for minimum 3 weeks → 進 Step 4a。
- Not already on OAC → 進 Step 4b。
- AF onset <24 h → Elective electrical cardioversion if needed(OAC 立即啟動)。
- AF onset ≥24 h or unknown → TOE-guided cardioversion I — 用 TOE 排除 LA appendage thrombus 後可立即做。
容易踩雷的地方:
3. Catheter Ablation — 2024 最大升級
| 族群 | 建議 | COR/LOE | vs 2020 |
|---|---|---|---|
| Paroxysmal AF — first-line | Catheter ablation 為首選 rhythm control(shared decision-making) | I A | 從 IIa B 升 I A |
| Paroxysmal AF — AAD 失敗後 | Catheter ablation | I A | 同 |
| Persistent AF — first-line | Catheter ablation 可考慮 | IIa B | — |
| Persistent AF — AAD 失敗後 | Catheter ablation | I A | — |
| HFrEF + AF | Catheter ablation 改善 survival 與 LV function | I B | 升級(CASTLE-AF) |
| Bradycardia–tachycardia syndrome(sick sinus + AF) | Catheter ablation 改善症狀並避免 pacemaker | IIa C | 新加 |
| Recurrence after PVI | Repeat catheter ablation 可考慮 | IIa B | 新加 |
| Anticoagulation periprocedural | Uninterrupted OAC 建議 | I A | 升級 |
Catheter ablation 的關鍵試驗證據
| 試驗 | 族群 | 結果 |
|---|---|---|
| EARLY-AF(NEJM 2021) | 未用 AAD 的 paroxysmal AF | 1 年 atrial tachyarrhythmia recurrence cryoablation 42% vs AAD 68%(HR 0.48) |
| STOP AF First(NEJM 2021) | 未用 AAD 的 paroxysmal AF | 1 年 freedom from AF cryoablation 75% vs AAD 45% |
| CABANA(JAMA 2019) | 2,204 名 paroxysmal/persistent AF | ITT primary composite 沒差,但 paroxysmal subgroup、AF burden、QoL 顯著改善 |
| CASTLE-AF(NEJM 2018) | 363 名 HFrEF + AF | ablation 降 all-cause death + HF hospitalization HR 0.62 |
| CONVERGE(Circ EP 2022) | 153 名 persistent AF | hybrid epicardial-endocardial 1 年 freedom 67% vs endocardial 50% |
| STAR-AF II(NEJM 2015) | 589 名 persistent AF | PVI alone 不劣於 PVI + linear/CFAE |
| RAFT-AF(NEJM 2022) | 411 名 AF + HF | ablation 降 all-cause death + HF event HR 0.80(borderline) |
Endoscopic / Hybrid AF Ablation(§7.2.7)
| 族群 | 建議 | COR/LOE |
|---|---|---|
| Symptomatic persistent AF refractory to AAD | Endoscopic / hybrid 應該考慮(shared rhythm-control team of EP + surgeon) | IIa A(新加) |
| Persistent AF + risk factors for catheter ablation failure 或 catheter ablation 失敗 | Thoracoscopic / hybrid surgical ablation 應該考慮(maintain long-term sinus rhythm) | IIa B |
| Symptomatic paroxysmal AF refractory to AAD + catheter ablation 失敗 | Endoscopic / hybrid 可以考慮 | IIb B |
| Continuation of OAC after concomitant / endoscopic / hybrid AF ablation(elevated thromboembolic risk) | 建議 | I C |
Concomitant Surgical Ablation(§7.2.8)— 心臟手術順帶做
| 情境 | 建議 | COR/LOE |
|---|---|---|
| Mitral valve surgery + AF(適合 rhythm control) | Concomitant surgical ablation 建議 | A(升級) |
| Non-mitral cardiac surgery + AF(適合 rhythm control) | Concomitant surgical ablation 應該考慮 | IIa B(新加) |
| Intraprocedural imaging for LA thrombus detection | 建議 | I C(新加) |
- 四種 AF 對應 4 張 figure:first-diagnosed (Fig 4) → paroxysmal (Fig 5) → persistent (Fig 6) → permanent (Fig 7)。所有路徑共通:先做 [C][A],rate control 依 LVEF 切(>40% 全種類;≤40% 不可 verapamil/diltiazem)。
- Rate control:lenient <110 bpm 一線,strict <80 給 lenient 仍症狀者;AV node ablation + CRT 在 permanent AF + HF hosp IIa B。
- Rhythm control 大升級:Catheter ablation 升為 paroxysmal AF first-line I A;HFrEF + AF ablation I B;早期介入 <12 個月 IIa B。
- Cardioversion(Fig 12):Wait-and-see <48h IIa B;TOE-guided 給未抗凝 + onset ≥24h;post-CV 4 週抗凝,長期依 CHA2DS2-VA。
- AAD 用藥四分層:HFrEF → amiodarone;HFmrEF/CAD/valve → amiodarone/dronedarone;無結構心 → dronedarone/flecainide/propafenone;sotalol IIb。Flecainide/propafenone 在結構性心臟病禁用(CAST)。
- Concomitant surgical ablation:mitral valve surgery 升為 I A(強烈建議順帶做);non-mitral IIa B。
📖 References
- Van Gelder IC, Rienstra M, Bunting KV, et al. 2024 ESC Guidelines for the management of atrial fibrillation. Eur Heart J 2024;45(36):3314–3414. doi:10.1093/eurheartj/ehae176
- Van Gelder IC, Groenveld HF, Crijns HJGM, et al. Lenient versus Strict Rate Control in Patients with Atrial Fibrillation (RACE II). N Engl J Med 2010;362:1363–1373. doi:10.1056/NEJMoa1001337
- Kirchhof P, Camm AJ, Goette A, et al. Early Rhythm-Control Therapy in Patients with Atrial Fibrillation (EAST-AFNET 4). N Engl J Med 2020;383:1305–1316. doi:10.1056/NEJMoa2019422
- Andrade JG, Wells GA, Deyell MW, et al. Cryoablation or Drug Therapy for Initial Treatment of Atrial Fibrillation (EARLY-AF). N Engl J Med 2021;384:305–315. doi:10.1056/NEJMoa2029980
- Wazni OM, Dandamudi G, Sood N, et al. Cryoballoon Ablation as Initial Therapy for Atrial Fibrillation (STOP AF First). N Engl J Med 2021;384:316–324. doi:10.1056/NEJMoa2029554
- Marrouche NF, Brachmann J, Andresen D, et al. Catheter Ablation for Atrial Fibrillation with Heart Failure (CASTLE-AF). N Engl J Med 2018;378:417–427. doi:10.1056/NEJMoa1707855
- Packer DL, Mark DB, Robb RA, et al. Effect of Catheter Ablation vs Antiarrhythmic Drug Therapy on Mortality, Stroke, Bleeding, and Cardiac Arrest Among Patients With Atrial Fibrillation (CABANA). JAMA 2019;321:1261–1274. doi:10.1001/jama.2019.0693
- Pluymaekers NAHA, Dudink EAMP, Luermans JGLM, et al. Early or Delayed Cardioversion in Recent-Onset Atrial Fibrillation (RACE 7 ACWAS). N Engl J Med 2019;380:1499–1508. doi:10.1056/NEJMoa1900353
- Brignole M, Pentimalli F, Palmisano P, et al. AV junction ablation and cardiac resynchronization for patients with permanent atrial fibrillation and narrow QRS (APAF-CRT). Eur Heart J 2018;39:3999–4008. doi:10.1093/eurheartj/ehy555
- DeLurgio DB, Crossen KJ, Gill J, et al. Hybrid Convergent Procedure for Treatment of Persistent Atrial Fibrillation (CONVERGE). Circ Arrhythm Electrophysiol 2020;13:e009288. doi:10.1161/CIRCEP.120.009288
- Verma A, Jiang C, Betts TR, et al. Approaches to Catheter Ablation for Persistent Atrial Fibrillation (STAR-AF II). N Engl J Med 2015;372:1812–1822. doi:10.1056/NEJMoa1408288
- Parkash R, Wells GA, Rouleau J, et al. RAndomized trial of AF ablation versus standard Therapy in heart failure with AF (RAFT-AF). N Engl J Med 2022;386:1737–1746.
- The CAST Investigators. Preliminary report: effect of encainide and flecainide on mortality in a randomized trial of arrhythmia suppression after myocardial infarction. N Engl J Med 1989;321:406–412.
本文以教學為目的整理 2024 ESC Guidelines for the management of atrial fibrillation;所有原文 Figure 之版權屬 ESC/EACTS。商業使用請洽 ESC 取得授權。
