

- HTAD(heritable thoracic aortic disease)框架:syndromic(Marfan、Loeys-Dietz、vEDS、Turner)+ non-syndromic(家族性 TAAD);遺傳檢測與家族篩檢是第一線(I C),FDR 25 歲開始 imaging(IIa C),每 5 年到 60 歲。
- Marfan:BB + ARB 合併使用(IIa A,新)取代過去單藥;妊娠前須 root >45 mm 必修(I C)、40-45 mm 可考慮(IIb C);BB 終生(I C)。
- Loeys-Dietz:aortic surgery threshold 較低(依 subtype,最低 LDS Type 1/2 root >40 mm);遠端動脈 aneurysm/dissection 風險高,全身 vascular surveillance(DUS+CCT+CMR)。
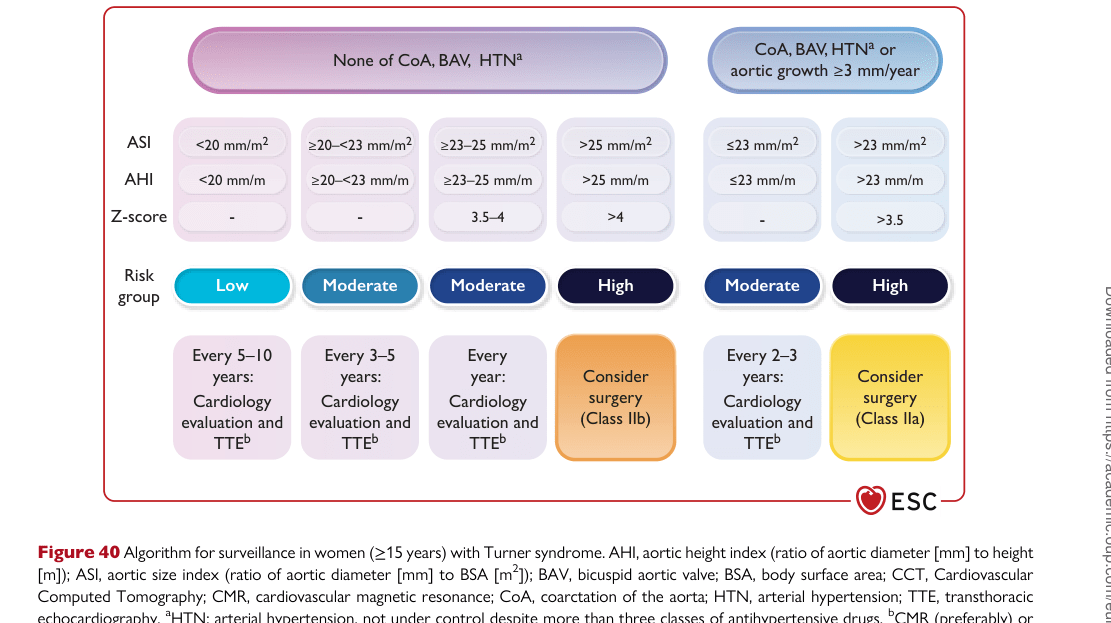
- Turner syndrome(女性 ≥15 歲):用 ASI / AHI / z-score 而非絕對直徑;ASI >23 mm/m² + 風險因子 → elective surgery(IIa C);ASI >25 + 無風險因子 → 可考慮(IIb C)。
- vEDS(vascular Ehlers-Danlos):celiprolol(IIa B,新);定期 DUS/CCT/CMR 全身血管(I C)。
- BAV-associated aortopathy:root phenotype → surgery ≥50 mm(I B);ascending phenotype low-risk → >52 mm 可考慮(IIa B);FDR TTE 篩檢(I C,新)。
- Coarctation:lifelong follow-up;CCT/CMR 每 3-5 年(I B)。
🗺️ 章節對應
本篇對應原文 Ch 10 — Genetic and congenital diseases of the aorta,嵌入 Figure 39-44(共 6 張),是本系列裡 disease-subtype 最豐富的一篇。每個 syndrome 都各自有:(1) imaging surveillance protocol、(2) surgical threshold、(3) 妊娠管理、(4) 家族篩檢策略。
🧬 10.1 HTAD — Heritable Thoracic Aortic Disease 總框架
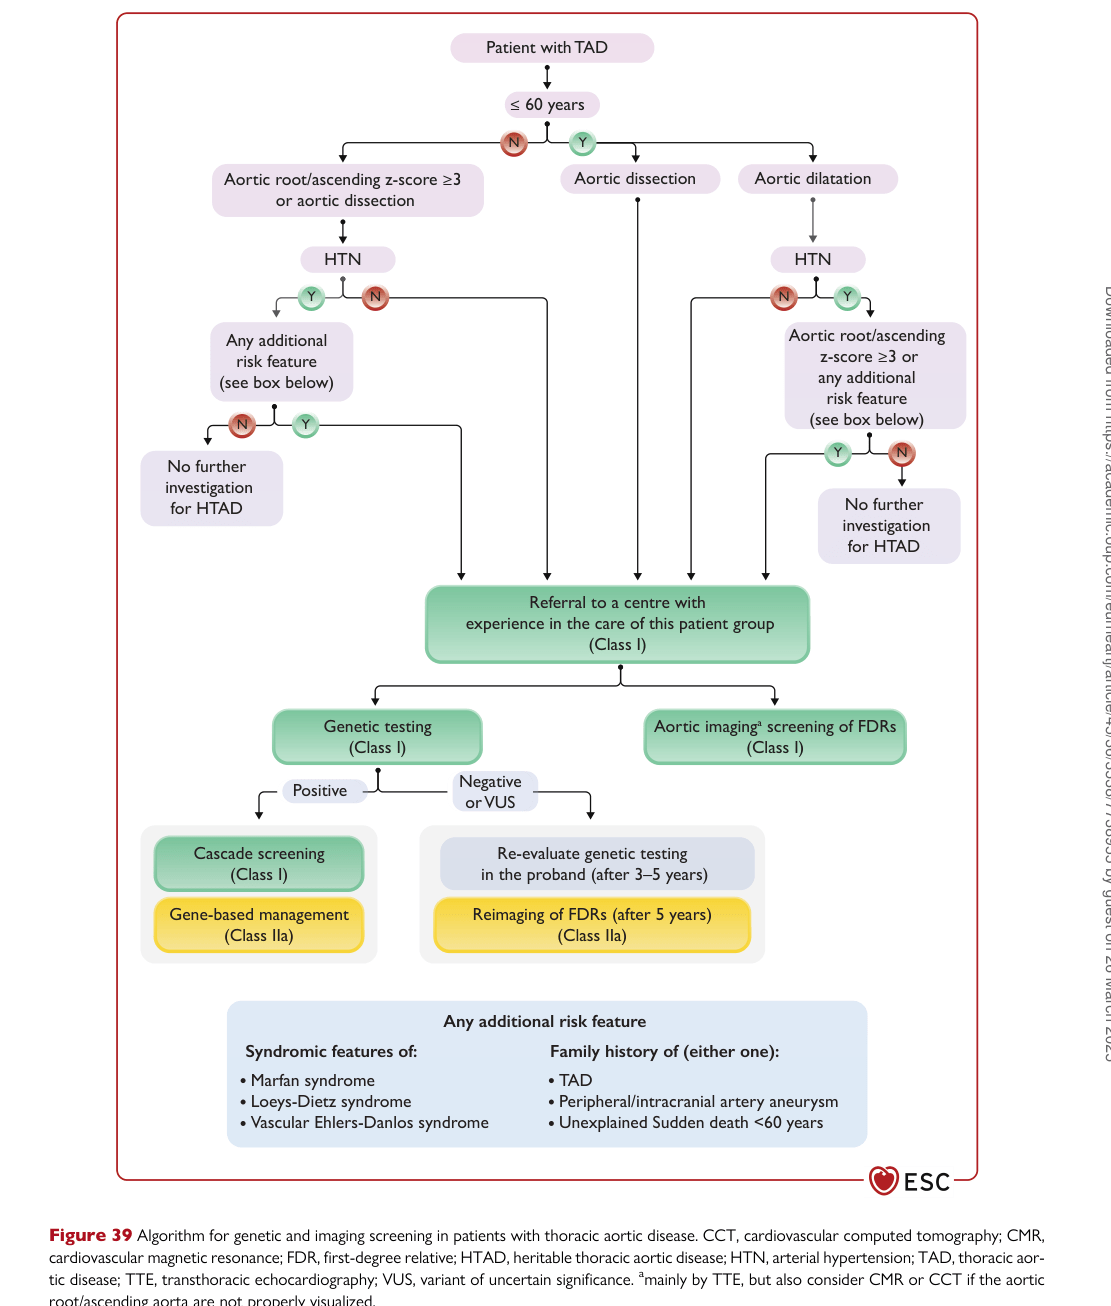
診斷與家族篩檢流程
來源:2024 ESC Guidelines for the Management of Peripheral Arterial and Aortic Diseases (Eur Heart J 2024;45:3538-3700, doi:10.1093/eurheartj/ehae179) — 個人教學用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 39(HTAD 基因與影像篩檢流程)
這張圖在回答什麼問題:診斷一位 TAD(thoracic aortic disease)病人後,如何決定要不要做基因檢測?家族成員怎麼篩?
逐步走完:
- 個人:早發 TAA/TAAD(<60 歲)、aortic disease + syndromic features(Marfan habitus、lens dislocation、joint hypermobility、translucent skin)、合併 cerebral/visceral aneurysm。
- 家族:FDR 有 TAA/TAAD/不明原因突然死亡(<50 歲);多個家族成員受影響。
容易踩雷的地方:
🎀 10.2 Turner Syndrome
來源:2024 ESC Guidelines for the Management of Peripheral Arterial and Aortic Diseases (Eur Heart J 2024;45:3538-3700, doi:10.1093/eurheartj/ehae179) — 個人教學用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 40(Turner syndrome 女性 ≥15 歲監測流程)
這張圖在回答什麼問題:Turner 患者體型較小,怎麼用 indexed parameters 評估 dissection risk?
逐步走完:
- ASI(Aortic Size Index) = ascending diameter (mm) / BSA (m²)
- AHI(Aortic Height Index) = ascending diameter (mm) / height (m)
- z-score:標準化後的偏離程度
容易踩雷的地方:
🧬 10.3 Marfan、Loeys-Dietz 與其他 HTAD
來源:2024 ESC Guidelines for the Management of Peripheral Arterial and Aortic Diseases (Eur Heart J 2024;45:3538-3700, doi:10.1093/eurheartj/ehae179) — 個人教學用,原始版權屬 ESC/EACTS。
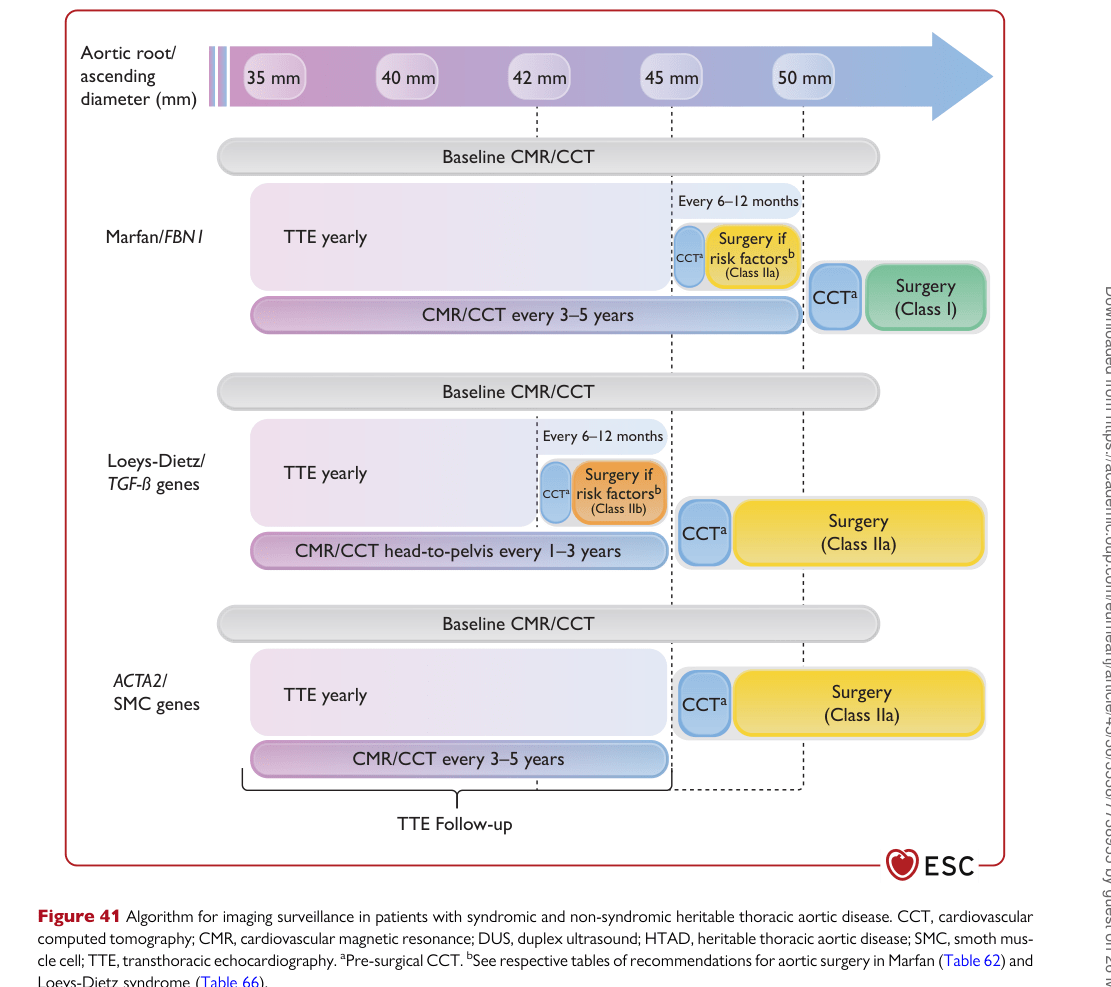
🧭 圖表逐步解析:Figure 41(syndromic/non-syndromic HTAD 影像 surveillance)
逐步走完:
- Root <45 mm,無 additional risk → 每年
- Root <45 mm,有 additional risk → 每 6 個月
- Root ≥45 mm,無 additional risk → 每 6-12 個月
容易踩雷的地方:
📏 10.3.1 Loeys-Dietz Syndrome(LDS)細節
來源:2024 ESC Guidelines for the Management of Peripheral Arterial and Aortic Diseases (Eur Heart J 2024;45:3538-3700, doi:10.1093/eurheartj/ehae179) — 個人教學用,原始版權屬 ESC/EACTS。
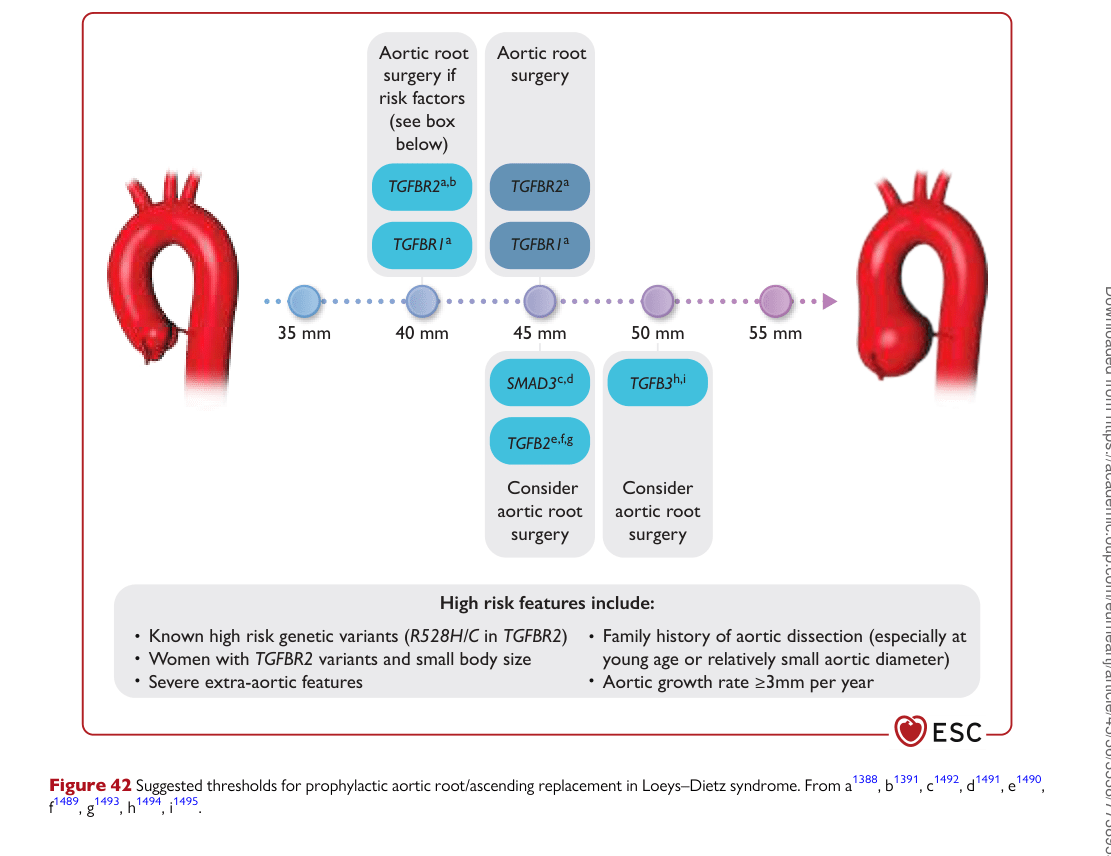
Figure 42 把 LDS 的 prophylactic aortic root/ascending replacement threshold 整理:
- LDS Type 1(TGFBR1)/ Type 2(TGFBR2):root >40 mm 即可考慮(低 threshold)
- LDS Type 3(SMAD3):root >42-45 mm
- LDS Type 4(TGFB2)/ Type 5(TGFB3):root >45 mm
- 所有 LDS:rapid growth(>3 mm/year)、family history of early dissection、planning pregnancy → 降低 threshold
關鍵:LDS 不能等到 55 mm — dissection 在 small root 也會發生。
💖 10.4 Marfan Syndrome 藥物與妊娠
藥物治療
| 建議 | Class | 細節 |
|---|---|---|
| BB 或 ARB(最大耐受劑量) | I A | 單藥;reduce aortic dilation rate |
| BB + ARB 合併 | IIa A | 新,meta-analysis 顯示合併比單藥更降低 dilation rate |
實務劑量範例:
- Atenolol:starting 25-50 mg → titrate to HR <80 / max BP 耐受
- Losartan:starting 25-50 mg → titrate to 100 mg
- Bisoprolol 或 metoprolol succinate 為替代
🧪 Marfan ARB/β-blocker IPD meta-analysis(2022, Lancet)— 撐起「BB + ARB 合併」IIa A
設計:個別病人資料(individual patient data, IPD)meta-analysis,整合 7 個隨機試驗、1,442 名 Marfan syndrome 病人(含 AIMS、COMPARE、Marfan Sartan、LOAT、Pediatric Heart Network 等);比較 ARB vs control、以及 ARB vs β-blocker;主要終點=aortic root Z-score 的年變化率,中位追蹤約 3 年。
結果:無 prior aortic surgery 者,ARB 使 aortic root Z-score 年增速約減半,且 在同時服用 β-blocker 的人身上同樣有效;β-blocker 的效果與 ARB 相近。假設兩者作用可加成,從診斷即合併 ARB + β-blocker 可比單藥更進一步減緩 root 擴大。
臨床意義:這正是 2024 指引把「BB + ARB 合併(最大耐受劑量)」列為 IIa A(單藥 BB 或 ARB 仍為 I A)的證據基礎。易踩雷/限制:終點是 影像替代指標(root growth),而非 dissection/death 等 hard endpoint;合併用藥要留意血壓過低與耐受度,採「最大耐受劑量」而非硬性 target。
妊娠管理
| 建議 | Class | 細節 |
|---|---|---|
| 所有 Marfan 女性 pre-conception evaluation | I C | maternal CV risk + 其他併發症評估 |
| 於 pregnancy heart and vessel team 中心追蹤 | I C | 跨專科共照 |
| Pre-conception 基因諮詢 | I C | HTAD 攜帶風險 |
| 妊娠前 CCT/CMR 全主動脈影像 | I C | baseline 必做 |
| 妊娠期 follow-up(依 root + growth) | I C | 通常每 trimester TTE |
| 妊娠期 BB | I C | continue throughout pregnancy |
| Root >45 mm + planning pregnancy → prophylactic surgery | I C | 必修 |
| Root 40-45 mm + planning pregnancy → 可考慮 prophylactic surgery | IIb C | 共決 |
運動建議:避免 competitive contact sports、isometric high-intensity(重訓 1RM);建議 low-moderate dynamic exercise(walking、cycling、swimming)。
🫀 10.5 Bicuspid Aortic Valve(BAV)-Associated Aortopathy
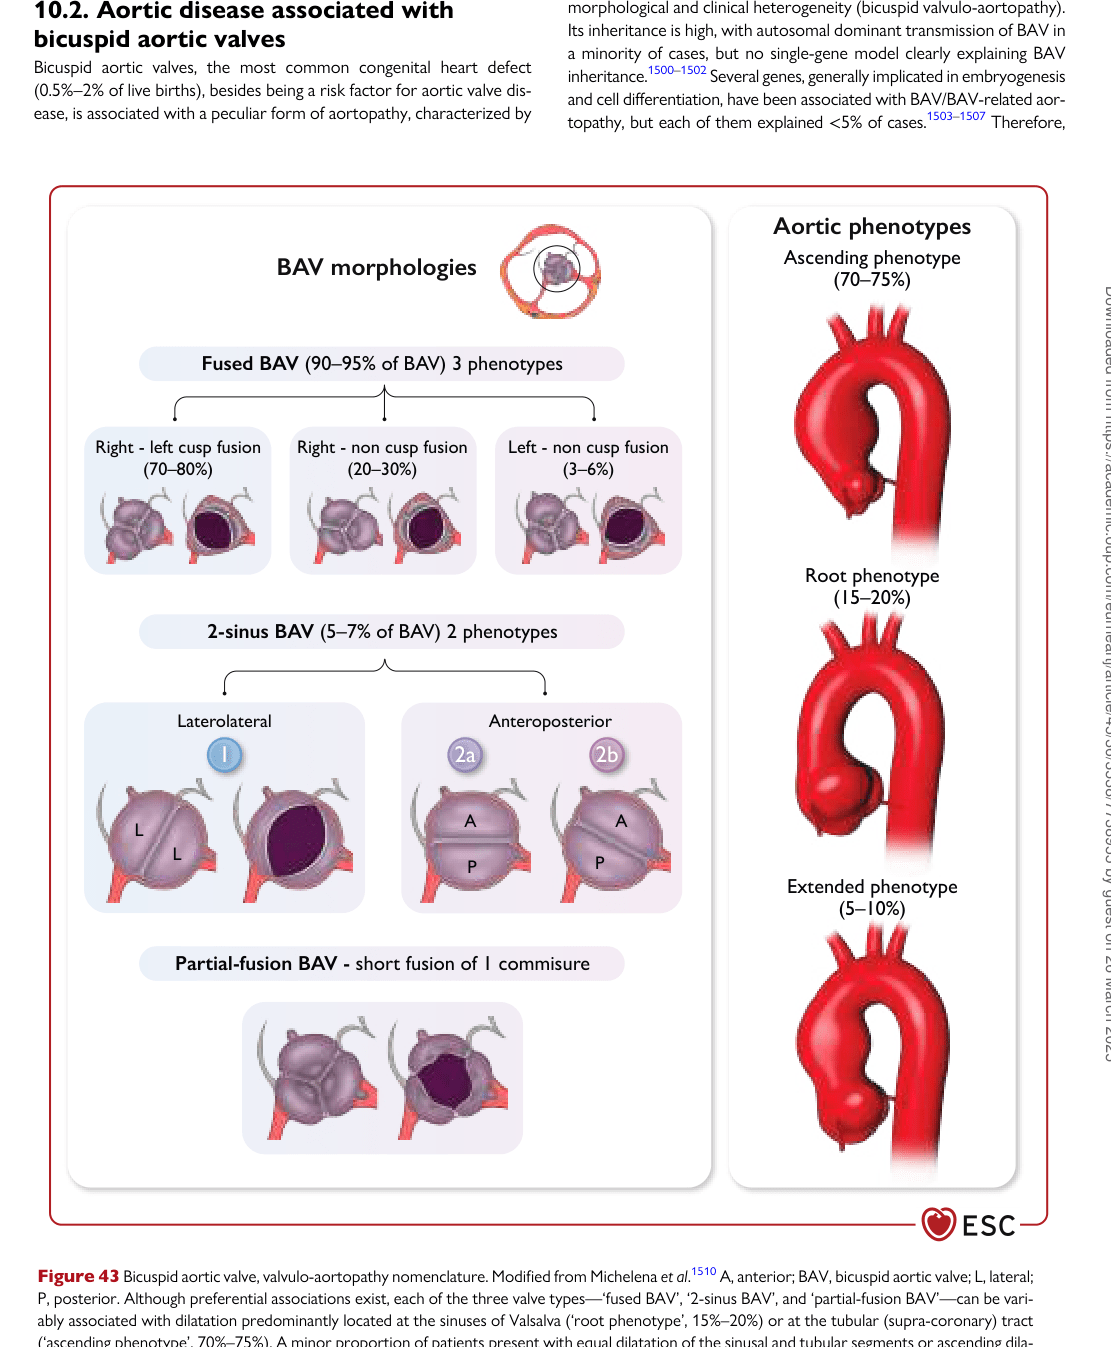
來源:2024 ESC Guidelines for the Management of Peripheral Arterial and Aortic Diseases (Eur Heart J 2024;45:3538-3700, doi:10.1093/eurheartj/ehae179) — 個人教學用,原始版權屬 ESC/EACTS。
Figure 43 把 BAV-associated valvulo-aortopathy 分為 morphological subtypes:
- Type A(anterior commissure):常合併 ascending phenotype
- Type B(other):可能 root phenotype
- Root phenotype:root dilation 主導,dissection 風險較高
- Ascending phenotype:tubular ascending 主導,dilation 較線性
BAV-aortopathy 手術建議
| 情境 | 建議 | Class / LOE |
|---|---|---|
| Root phenotype | ≥50 mm | I B |
| Ascending phenotype, low surgical risk | >52 mm 可考慮 | IIa B |
| FDR 篩檢(root phenotype 或 isolated AR) | TTE | I C |
| BAV + 全主動脈影像 baseline | CCT/CMR if echo unclear or diameter >45 mm | I C |
| TTE 監測 | diameter >40 mm → 每 1-2 年 | I C |
BAV-aortopathy 實務
- 診斷 BAV → 立即評估 root + ascending、aortic valve function(AR/AS)、coarctation(合併率約 7-15%)。
- FDR 篩檢(新建議):root phenotype 或 isolated AR 病人的 FDR 都應做 TTE,因 BAV 與 BAV-aortopathy 顯著家族聚集。
- Pregnancy in BAV:root >45 mm → pre-conception surgery 評估;ascending >50 mm 同樣需評估。
🔄 10.6 Coarctation of the Aorta
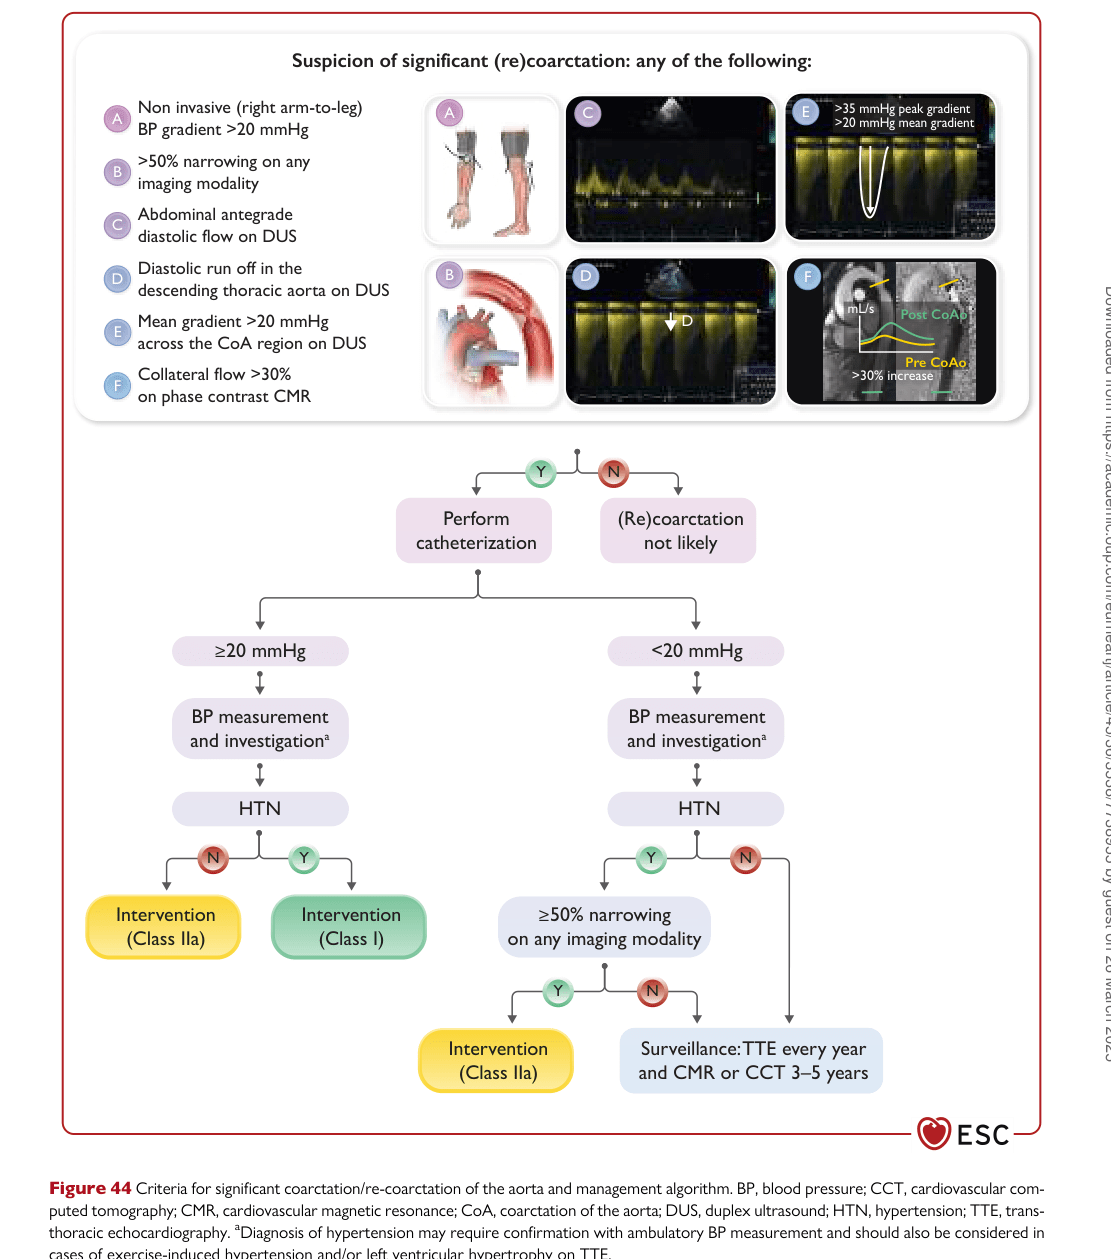
來源:2024 ESC Guidelines for the Management of Peripheral Arterial and Aortic Diseases (Eur Heart J 2024;45:3538-3700, doi:10.1093/eurheartj/ehae179) — 個人教學用,原始版權屬 ESC/EACTS。
🧭 圖表逐步解析:Figure 44(顯著 coarctation/re-coarctation 判定與管理)
逐步走完:
- Arm-leg SBP gradient >20 mmHg(resting 或 exercise)
- Doppler peak gradient >20 mmHg + diastolic tail
- Coarctation diameter <50% of diaphragmatic aorta(CCT/CMR)
- Resistant HTN with confirmed coarctation
容易踩雷的地方:
🤰 妊娠特別考量(橫跨各 HTAD)
| 疾病 | Pre-conception threshold | 妊娠期影像 | 分娩方式 |
|---|---|---|---|
| Marfan | Root >45 mm → prophylactic surgery | 每 trimester TTE | vaginal delivery if root <40 mm 且無 dissection;其餘 C-section |
| LDS | Root >40-42 mm(依 subtype) | 每 4-6 週 TTE | 傾向 C-section |
| vEDS | 強烈不建議妊娠(maternal mortality ↑↑) | 每月影像若仍妊娠 | C-section + planned vascular surgery cover |
| Turner | ASI 評估;高風險避免 | 每 trimester TTE | 個別化 |
| BAV-aortopathy | Root >45 mm 評估 | 每 trimester TTE | vaginal if low risk |
| Coarctation | 修復後 OK;未修復 + 顯著 → repair first | 每 trimester TTE + BP | vaginal if low risk |
📋 關鍵 Recommendations 對照表
| 主題 | 建議 | Class / LOE | vs 舊版 |
|---|---|---|---|
| HTAD FDR genetic counselling | pre-conception | I C | 新明文 |
| HTAD FDR imaging screening | 25 歲開始 / 每 5 年至 60 | IIa C | 新明文 |
| Turner ASI/AHI/z-score | indexed parameter | I C | 新(過去用絕對直徑) |
| Turner elective surgery(風險因子) | ASI >23 + risk | IIa C | 新 |
| vEDS celiprolol | routine | IIa B | 新 |
| vEDS surveillance | DUS/CCT/CMR 定期 | I C | 新明文 |
| Marfan BB or ARB | 最大耐受劑量 | I A | 不變 |
| Marfan BB + ARB 合併 | 最大耐受劑量 | IIa A | 新 |
| Marfan TTE 規範頻率 | 依 root size + risk | I C | 細節更新 |
| BAV root phenotype 手術 | ≥50 mm | I B | 不變 |
| BAV ascending phenotype low-risk | >52 mm 可考慮 | IIa B | 新 |
| BAV FDR TTE 篩檢 | root phenotype / isolated AR | I C | 新 |
| Coarctation lifelong CCT/CMR | 每 3-5 年 | I B | 明文化 |
- HTAD 框架:syndromic + non-syndromic;遺傳檢測 → FDR cascade screening;未找到 mutation 仍要 FDR imaging(25 歲開始 / 每 5 年)。
- Marfan 新藥物:BB + ARB 合併(IIa A);妊娠前 root >45 mm 必修;終生 BB。
- Loeys-Dietz:surgical threshold 顯著降低,type 1/2 可低至 40 mm;全身 vascular surveillance。
- Turner:用 ASI/AHI/z-score 而非絕對直徑;ASI >23 + 風險因子 → 手術。
- vEDS:celiprolol(IIa B);非侵入性影像為主,避免 invasive procedure。
- BAV-aortopathy:root phenotype 50/ascending low-risk 52 mm;FDR TTE 篩檢(新)。
- Coarctation:終生追蹤、CCT/CMR 每 3-5 年;要篩 BAV 與 berry aneurysm;持續嚴格控制 HTN。
- 妊娠:所有 HTAD 都該 pre-conception evaluation;syndrome-specific threshold;高風險建議 C-section + 多專科共照。
🎬 系列總結語
到本篇為止,2024 ESC PAAD Guidelines 五篇系列完成。重看一遍系列脈絡:
- (I) 總論:把 atherosclerosis 視為整條動脈系統的疾病;三大藥物基石(LDL <55、COMPASS、SET/HBET)升級。
- (II) LE PAD / CLTI / ALI:診斷 → SET + OMT 3 個月 → QoL 仍差才介入;CLTI 第一線 endovascular + vein bypass;ALI 6P + Rutherford 分級救命。
- (III) 其他血管床 + Polyvascular:carotid 用 NASCET、symptomatic 14 天內介入;RAS 多數不該 revascularize;CMI 三聯 + 2 條 stenosis;polyvascular = LDL <55 + COMPASS。
- (IV) Aortic Aneurysm + AAS:AAA 篩檢收斂;TAA threshold 部分降低;TAAD 修復三大新標準(resuspension、open distal anastomosis、hemi-arch);subacute TBAD TEVAR window 新增。
- (V) Genetic aortopathy:HTAD 框架、Marfan BB+ARB、Turner ASI、vEDS celiprolol、BAV FDR 篩檢、Coarctation 終生追蹤。
臨床落地三句話:
- 診斷一處 PAAD = 主動評估其他血管床 + 把 LDL 壓到 <55 + 評估是否合適 COMPASS。
- 所有 IC 病人先 OMT + SET 3 個月再談介入;CLTI vs ALI 是 surgical emergency,分秒必爭。
- 主動脈病人:屆滿 surgical threshold + 嚴格 BP/HR 控制;HTAD 病人 — 基因檢測、家族篩檢、妊娠 pre-conception、終生 BB 與影像追蹤都不能漏。
📖 References
- Mazzolai L, Teixido-Tura G, Lanzi S, et al. 2024 ESC Guidelines for the management of peripheral arterial and aortic diseases. Eur Heart J 2024;45(36):3538-3700. doi:10.1093/eurheartj/ehae179. PMID: 39210710.
- Aboyans V, Ricco JB, Bartelink ME, et al. 2017 ESC Guidelines on the Diagnosis and Treatment of Peripheral Arterial Diseases. Eur Heart J 2018;39(9):763-816.
- Erbel R, Aboyans V, Boileau C, et al. 2014 ESC Guidelines on the diagnosis and treatment of aortic diseases. Eur Heart J 2014;35(41):2873-2926.
- Anand SS, Bosch J, Eikelboom JW, et al. Rivaroxaban with or without aspirin in patients with stable peripheral or carotid artery disease (COMPASS). Lancet 2018;391(10117):219-29.
- Bonaca MP, Bauersachs RM, Anand SS, et al. Rivaroxaban in Peripheral Artery Disease after Revascularization (VOYAGER PAD). N Engl J Med 2020;382(21):1994-2004.
- Bonaca MP, Nault P, Giugliano RP, et al. Low-Density Lipoprotein Cholesterol Lowering With Evolocumab and Outcomes in Patients With Peripheral Artery Disease (FOURIER subanalysis). Circulation 2018;137(4):338-50.
- Pitcher A, Spata E, Emberson J, et al. Angiotensin receptor blockers and β blockers in Marfan syndrome: an individual patient data meta-analysis of randomised trials. Lancet 2022;400(10355):822-31. doi:10.1016/S0140-6736(22)01534-3.
本文以教學為目的整理 2024 ESC Guidelines for the management of peripheral arterial and aortic diseases,所有原文 Figure 之版權屬 ESC/EACTS;商業使用請洽 ESC 取得授權。
