

- Lp(a) 升格為 risk modifier:>50 mg/dL(>105 nmol/L)視為 CV risk-enhancing factor IIa B。每個成人一生至少測一次—濃度高度由 genetics 決定,測一次就夠(>90% heritable)。Lp(a) 高的病人優先用 high-intensity statin 並把 LDL-C 降到底。
- 三酸甘油脂治療精準化:n-3 PUFA 的角色限縮到 high-dose icosapent ethyl(pure EPA ethyl ester,2×2 g/day),給 statin + TG 135-499 mg/dL 的 high/very high risk 病人 IIa B。Volanesorsen 給 FCS 的 severe TG >750 mg/dL IIa B。Pemafibrate 被 PROMINENT 推翻、混合 EPA+DHA 被 STRENGTH 推翻。
- HIV 一級預防 statin 直接打開:≥40 歲 PWH 一律 statin,不看 LDL-C / 不看 SCORE2 I B(REPRIEVE)。注意 antiretroviral drug interaction—pitavastatin 是 REPRIEVE 用的選擇。
- Cancer 化療心毒性預防:anthracycline-treated cancer 病人若 high/very high cancer therapy-related CV toxicity → statin IIa B(STOP-CA)。對齊 2022 ESC cardio-oncology guidelines。
- 飲食補充品被擋下:沒實證 safety + LDL-C lowering 的 supplements III B—包括 red yeast rice、garlic、cinnamon、turmeric、混合 PUFA、phytosterols(雖能降 LDL-C ~10% 但無 outcome data)。
🔬 §6 Lipoprotein(a) — 終於進入主流
為什麼 Lp(a) 重要
Lp(a)(讀作 “L-P-little-a”)是LDL-like 粒子上面共價結合一條 apolipoprotein(a)—apo(a) 結構類似 plasminogen(雖然無 fibrinolytic 活性)。它的致動脈粥狀硬化機轉不完全等同 LDL:(a) 直接 deposit 進 plaque 並促 inflammation;(b) 帶大量 oxidized phospholipids 加劇 endothelial dysfunction;(c) 結構模仿 plasminogen 干擾 fibrinolysis、促 thrombosis;(d) 在 aortic valve leaflet 沉積引起 calcific aortic stenosis。
遺傳決定為主:Lp(a) 濃度 >90% 由 LPA gene(特別是 KIV-2 copy number 變異)決定。意義:單次測量就足夠(不像 LDL-C 受飲食 / statin 影響),且家族成員應該一起測。
受影響的疾病(UK Biobank、CGPS、CCHS 大規模數據):
- 最強:MI(dose-response)、aortic valve stenosis
- 中等:peripheral artery disease、heart failure
- 較弱:ischemic stroke、CV mortality、all-cause mortality
濃度 thresholds:
- <30 mg/dL(<62 nmol/L):正常
- 30-50 mg/dL(62-105 nmol/L):稍升,輕微增加 CV 風險
- ≥50 mg/dL(≥105 nmol/L):clinically relevant、risk-enhancing factor(影響 ~20% 人口)
- ≥180 mg/dL:極高風險(相當於 heterozygous FH 的等級)
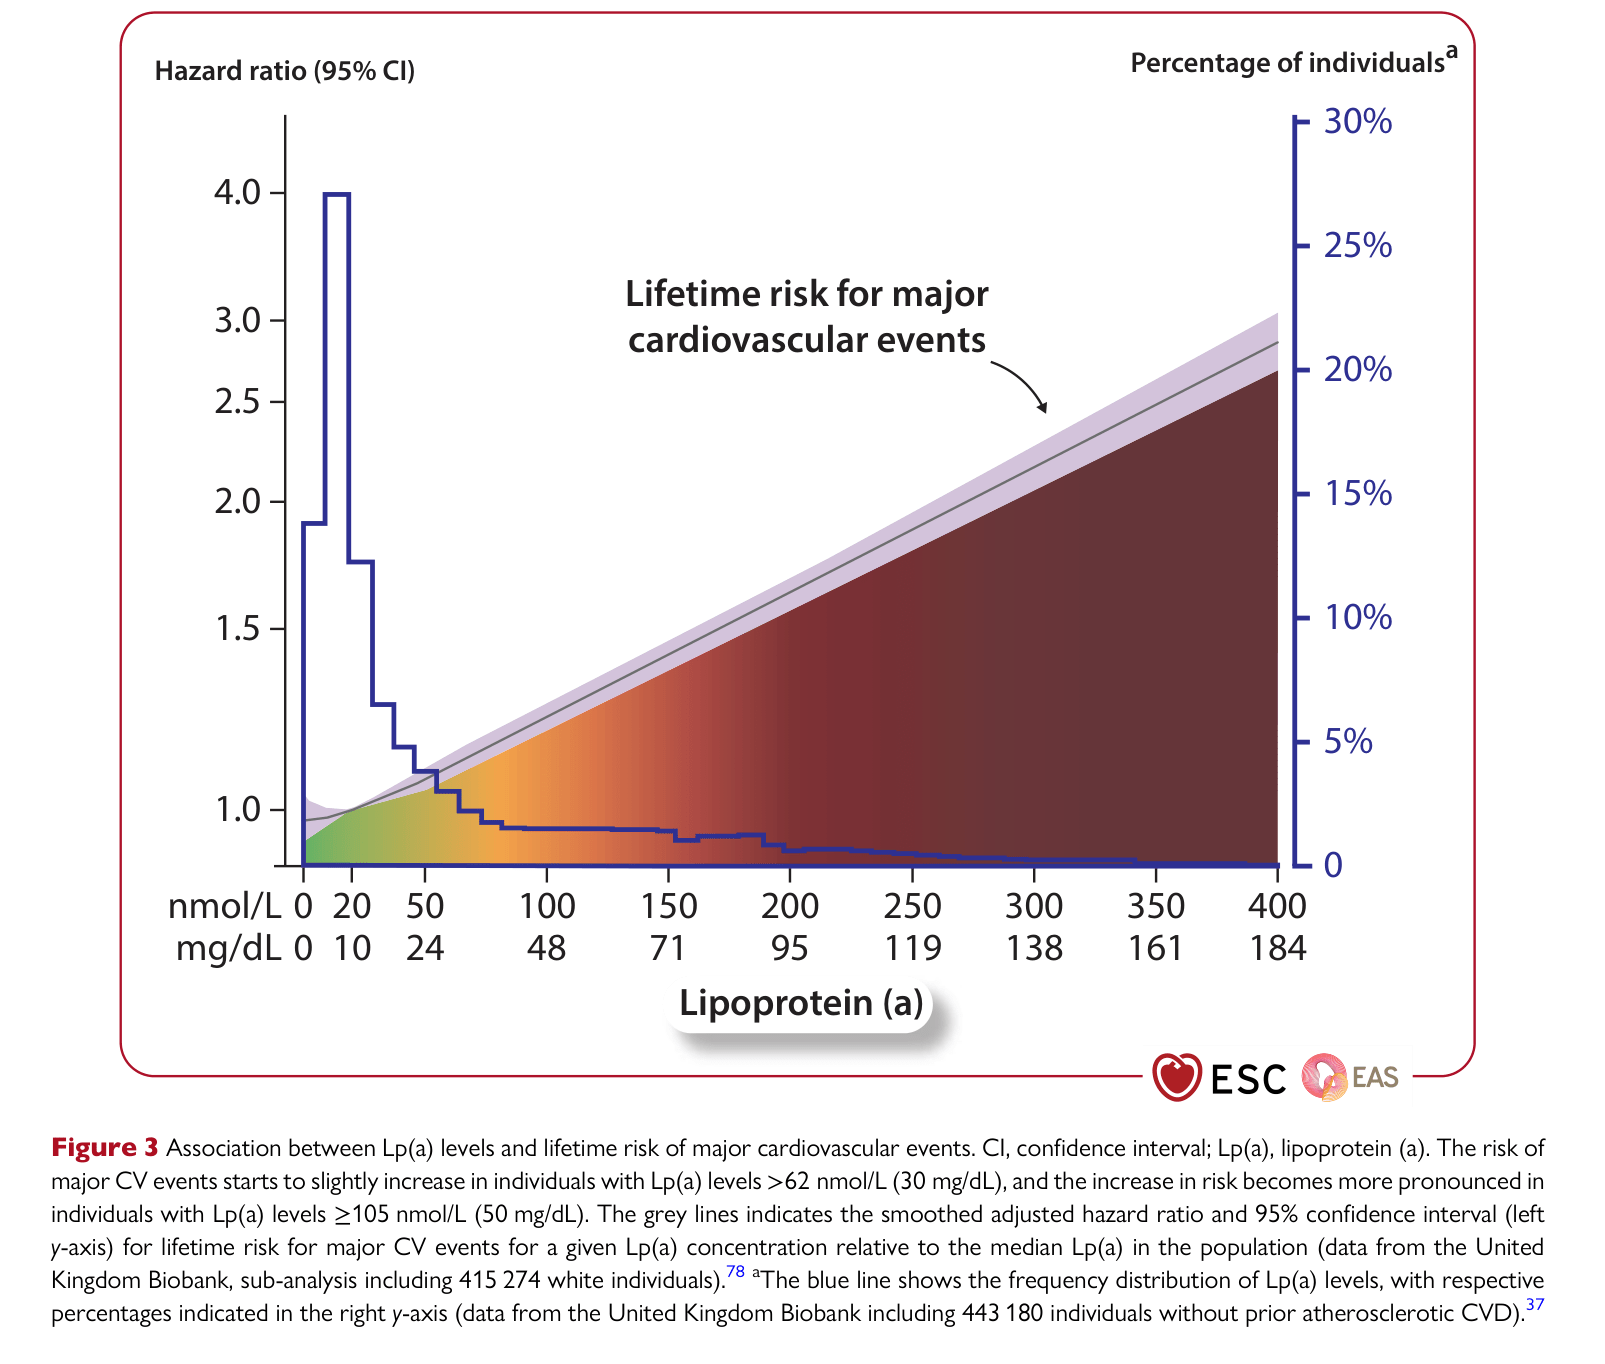
來源:2025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias (doi:10.1093/eurheartj/ehaf190) — 個人教學使用,原始版權屬 ESC/EAS。
🧭 圖表逐步解析:Figure 3(Lp(a) 與 lifetime CV risk)
這張圖在回答什麼問題:不同 Lp(a) 濃度對應的 lifetime major CV event 風險倍率是多少?這個增加是「閾值式跳階」還是「連續上升」?
讀法:左 y 軸 = adjusted hazard ratio(HR,相對於族群中位 Lp(a));右 y 軸 = 該族群中 Lp(a) 此濃度的人口百分比(藍線 frequency distribution);x 軸 = Lp(a) 濃度(nmol/L 與 mg/dL 雙標)。資料來自 UK Biobank 415,274 人(grey HR line)與 UK Biobank 443,180 人 without prior ASCVD(blue frequency distribution)。
逐步走完:
- Lp(a) 0-30 mg/dL:HR ≈ 1.0(基線)
- Lp(a) >62 nmol/L(30 mg/dL):HR 開始 >1.0—風險開始 slight 增加
- Lp(a) ≥105 nmol/L(50 mg/dL):HR 明顯 >1.0,increase 變得 pronounced
- Lp(a) 200 nmol/L:HR ~2.0(風險倍增)
- Lp(a) 400 nmol/L:HR 接近 4.0(風險 4 倍)
容易踩雷的地方:
- 單位混淆:nmol/L 與 mg/dL 換算不是固定比例(apo(a) 大小變異)。實驗室報的單位請看清楚;指引偏好 nmol/L。一些舊報告用 mg/dL,>50 mg/dL ≈ >105 nmol/L 是 rough 對應。
- Lp(a) HR 用在「重新分類」而非「絕對門檻」—Lp(a) 高的 moderate risk 病人考慮往 high reclassify;不是說 Lp(a) >50 mg/dL 自動就是 very high risk。
- 誤以為 statin 會降 Lp(a)。statin 對 Lp(a) 沒效(甚至略升)—7 個 statin outcome trial individual-patient-data meta-analysis 確認 no effect。但 Lp(a) 高的病人仍應該用 high-intensity statin,因為他們的 baseline ASCVD 風險高,降 LDL-C 是現在唯一能做到的事。
- menopause 之後 Lp(a) 可能上升 → 對停經前 borderline 的女性(Lp(a) 30-50 mg/dL),停經後重測一次合理。
- 不同 assay 之間結果差異大(apo(a) Kringle-IV repeats 變異)。追蹤同一病人時要用同一 assay,避免比較不同實驗室的結果。
建議與 actionable items
(1) 一生至少測一次 Lp(a)—2019 版已有此建議,2025 強化。特別重要:
- FH 患者
- 早發 ASCVD 患者(<55 男 / <65 女)且無傳統 risk factor
- 有早發 ASCVD 或高 Lp(a) 家族史者
- Moderate risk 或在治療決策閾值附近者(決定要不要開藥的關鍵)
(2) Lp(a) >50 mg/dL(>105 nmol/L)作為 risk-enhancing factor IIa B—用來幫助 risk reclassification(向上)。
(3) Lp(a) 高的病人 LDL-C 降到底:強烈鼓勵 high-intensity statin(即使 statin 對 Lp(a) 本身沒效,但降 LDL-C 能降整體 atherogenic burden)。實務上對 Lp(a) 非常高的病人,許多臨床醫師會 PCSK9 mAb(PCSK9 inhibition 降 Lp(a) ~25-30%—雖然不是主要 indication)。
(4) 線上 Lp(a) risk-benefit algorithm:eas-society.org/LPA_risk_and_benefit_algorithm
Lp(a)-lowering 藥物(在等 outcome)
目前進行中:
- Pelacarsen(antisense oligonucleotide targeting LPA mRNA)— Lp(a)↓80-90%,HORIZON trial outcome 預計 2025 報告
- Olpasiran(siRNA targeting apo(a))— Lp(a)↓~95%,OCEAN(a)-Outcomes trial 進行中
- Lepodisiran(siRNA)— phase II 階段
- Muvalaplin(口服 small molecule inhibitor,阻 apo(a)-apoB binding)— phase II
這些藥可以將 Lp(a) 降 80-98%—但outcome 是否降 MACE 還未證實。在 outcome 結果出來之前,沒有 specific Lp(a)-lowering recommendation。
🔬 §7 Hypertriglyceridaemia
整體立場
TG 與 CV 風險獨立相關(即使 LDL-C controlled),但 「降 TG → 降 CV event」的因果鏈不像 LDL-C 那麼直接。Statin 仍是降 TG 病人的第一線—即使 TG 是主要 abnormality,statin 也有 outcome benefit。
Fibrate 的角色(基本沒變)
Fenofibrate、bezafibrate、gemfibrozil 降 TG 有限(中等效力),沒有清楚的 outcome benefit。次群分析(atherogenic dyslipidemia—high TG + low HDL-C)有訊號,但 confirmatory trial 失敗。
PROMINENT trial(NEJM 2022)— 重大負面結果:pemafibrate(selective PPAR-α modulator)給 T2DM + 輕中度 hypertriglyceridemia + 低 HDL-C(n=10,497)—MACE 沒改善,ApoB 與 LDL-C 反而上升。這基本上把 fibrate-class 在 outcome 上的地位推得更低。
2025 update 維持 2019 版 fenofibrate / bezafibrate 的 IIb 建議—可以考慮但 evidence 弱。Fibrate 不是用來降 LDL-C 或 total cholesterol 的。
n-3 PUFA:從「general PUFA」精準化為「icosapent ethyl」
關鍵兩個對立 trial:
| 項目 | REDUCE-IT(positive) | STRENGTH(negative) |
|---|---|---|
| 主要藥物 | Pure icosapent ethyl (EPA ethyl ester) 2×2 g/day | EPA + DHA mixture (omega-3 carboxylic acid) |
| 族群 | Statin-treated, TG 135-499 mg/dL, ASCVD or DM+RF | Statin-treated, TG 200-499 mg/dL, high CV risk |
| placebo | Mineral oil | Corn oil |
| 結果(MACE) | HR 0.75(25% RRR) | HR 0.99(no effect) |
差異解讀:(a) 主成分不同(pure EPA vs EPA+DHA mixture)—DHA 可能干擾 EPA 的 anti-atherogenic 效應;(b) Placebo 形式不同(mineral oil 可能有 mild pro-atherogenic 效應,造成 REDUCE-IT 效果被放大);(c) 高劑量 pure EPA 對 membrane structure、cholesterol domain、endothelial function 有獨特效應。
🧪 REDUCE-IT(2019, N Engl J Med)vs STRENGTH(2020, JAMA)— 為何只有 pure icosapent ethyl 進指引
設計:REDUCE-IT—8,179 名 statin-treated、TG 135–499 mg/dL、ASCVD 或 DM+RF 患者,隨機 pure icosapent ethyl(純 EPA ethyl ester)2 g bid vs mineral oil placebo,median 4.9 年。STRENGTH—13,078 名類似族群,EPA+DHA carboxylic acid(Epanova)4 g/day vs corn oil,因無效提前終止。
結果:REDUCE-IT 主要 MACE 17.2% vs 22.0%,HR 0.75(95% CI 0.68–0.83;P<.001,25% RRR)。STRENGTH HR 0.99(95% CI 0.90–1.09)完全無效,雖然 TG 仍降約 19%。
臨床意義:兩者方向相反,撐起「只有 high-dose pure icosapent ethyl」IIa B、混合 EPA+DHA 與 supplement fish oil 不算。爭議/陷阱:REDUCE-IT 用 mineral oil 對照可能本身有輕度 pro-atherogenic 效應(placebo 組 LDL-C/hs-CRP 上升),使療效被放大—這是 pure EPA 真實效益究竟多大的長期爭論點。
2025 update 的精準化建議:High-dose icosapent ethyl(2×2 g/day)+ statin → high/very high risk + TG 135-499 mg/dL IIa B。混合 EPA+DHA 或低劑量 fish oil 不在內。
Volanesorsen — FCS 救援
FCS(familial chylomicronemia syndrome)是 LPL(lipoprotein lipase)功能缺損的罕病,TG >1000 mg/dL 是常態,胰臟炎是主要 morbidity。傳統 fibrate / fish oil / 飲食控制效果有限。
Volanesorsen:antisense oligonucleotide targeting hepatic ApoC-III mRNA(ApoC-III 抑制 LPL;降它 = 解除 LPL 抑制 = 降 TG)。
APPROACH(phase III,n=66 FCS):Volanesorsen 300 mg/week SC,TG↓77% in 3 個月、77% 病人 TG 降到 <750 mg/dL。Meta-analysis of 3 trials: TG >500 mg/dL 病人 acute pancreatitis 顯著減少。
副作用注意:thrombocytopenia(要 frequent 監測 platelet)、injection-site reaction(60% 病人)。已被 EMA 核准(FDA 未核准)作為 FCS 的 adjunct to diet/TG-lowering therapy。
建議:Volanesorsen 給 FCS 患者 + TG >750 mg/dL,降胰臟炎風險 IIa B。
進行中的 TG-lowering 藥物
注射 ApoC-III 標的藥物(antisense oligonucleotide 與 siRNA)能降 TG 80% — Olezarsen(ASO)、Plozasiran(siRNA)等在 phase III。這些可能在下一版完整指引被納入。
🔬 §8 HIV — 一級預防 statin 翻轉
為什麼 HIV 病人 CVD 風險高
PWH(people with HIV)有2 倍 ASCVD 風險(vs general population)。機轉:(a) 慢性免疫活化與發炎(即使 viral suppressed);(b) ART 引起的 dyslipidemia(特別 protease inhibitor);(c) 傳統 risk factors 在 PWH 累積—吸菸率高、HTN、DM 等。
關鍵問題:傳統 risk prediction tools(SCORE2、Framingham)low-balling HIV CVD 風險。所以「等 SCORE2 跨閾值再開 statin」會錯失預防時機。
REPRIEVE — 翻盤的試驗
REPRIEVE(NEJM 2023):
- n = 7,769 PWH,40-75 歲,low-to-moderate ASCVD risk(10-year ASCVD risk <15%),on ART
- Pitavastatin 4 mg/day vs placebo
- Median follow-up 5.1 年(提早終止 for efficacy)
- Primary MACE: HR 0.65(35% RRR);95% CI 0.48-0.90;P=.002
- Men、women 都有效(重要—女性 HIV-associated CVD 風險更高)
- 5-year NNT = 106(很合理)
- 副作用:muscle symptoms(2.4% vs 1.3%)、new-onset DM(5.3% vs 4.0%)—相對 statin 一般可接受
🧪 REPRIEVE(2023, N Engl J Med)— 打開 HIV 一級預防 statin 的試驗
設計:7,769 名 40–75 歲、on ART、low-to-moderate ASCVD risk(10-yr ASCVD <15%)的 PWH,隨機 pitavastatin 4 mg/day vs placebo,median 追蹤 5.1 年(因 efficacy 提前終止)。
結果:Primary MACE 4.81 vs 7.32 per 1000 person-years,HR 0.65(95% CI 0.48–0.90;P=.002,35% RRR);男女皆獲益;5 年 NNT ~106。安全性:muscle symptoms 2.4% vs 1.3%、new-onset DM 5.3% vs 4.0%。
臨床意義:把 HIV ≥40 歲一級預防 statin 從 IIa 推到 I B(不看 LDL-C、不看 SCORE2)。陷阱:選 pitavastatin 4 mg 是因 drug interaction 最少;protease inhibitor(ritonavir/cobicistat)下 simvastatin/lovastatin 禁用、atorvastatin/rosuvastatin 限低劑量。
建議與實務
≥40 歲 PWH 一律 statin,不看 LDL-C / 不看 SCORE2 I B。為什麼這樣?
- RR 35% 降低很顯著
- NNT 106 / 5 年是 acceptable
- HIV 的 risk underestimation 讓「SCORE2 門檻」變得不可靠
- Universal approach 簡化臨床決策,避免漏掉高風險者
Statin 選擇:drug interaction 是關鍵。Protease inhibitor(ritonavir、cobicistat-boosted)強烈抑制 CYP3A4 → simvastatin / lovastatin 禁用;atorvastatin 限低劑量(≤20 mg);rosuvastatin 限低劑量;pitavastatin 4 mg 是 REPRIEVE 用的選擇,drug interaction 最少。Pravastatin 也常用(但 protease inhibitor 可能降低 pravastatin 濃度)。
其他 LDL-C 降階藥物在 HIV:
- Ezetimibe:在 PWH 降 LDL-C 與一般人類似,well tolerated
- Evolocumab(PCSK9 mAb):在 464 PWH 試驗 LDL-C↓57%,well tolerated
- Bempedoic acid / icosapent ethyl:尚未在 PWH 試驗
🔬 §9 Cancer — anthracycline 心毒性的 statin 預防
為什麼需要這個建議
Anthracycline-based 化療(多種血液腫瘤、乳癌等)會引起 cumulative dose-dependent 心毒性 — LVEF↓、HF。發生率:5 年內 HF 達 20%,視 cumulative dose 而定。傳統預防是 dexrazoxane(鐵螯合劑)—有 myelosuppression 顧慮、效果有限。
STOP-CA — 主要試驗
STOP-CA(JAMA 2023):
- n = 300 lymphoma 病人接受 anthracycline
- Atorvastatin 40 mg/day vs placebo(雙盲 RCT)
- Primary endpoint = 12 個月時「LVEF↓ ≥10% AND final LVEF <55%」的比例
- 結果:22%(placebo)→ 9%(atorvastatin),P=.002
🧪 STOP-CA(2023, JAMA)— anthracycline 心毒性的 statin 預防試驗
設計:300 名接受 anthracycline-based 化療的 lymphoma 病人(9 個美國學術中心),雙盲隨機 atorvastatin 40 mg/day(n=150)vs placebo(n=150),化療前開始、持續 12 個月。
結果:主要終點「12 個月內 LVEF 絕對下降 ≥10% 且 final LVEF <55%」的比例 9%(atorvastatin)vs 22%(placebo),P=.002。
臨床意義:撐起 high/very high cancer therapy-related CV toxicity risk 的 anthracycline 病人加 statin IIa B(baseline 風險分層走 2022 ESC cardio-oncology)。限制:終點是 LVEF 影像指標而非硬 HF/MACE、單一癌別(lymphoma)、只給高風險亞群—不是 universal;ezetimibe/PCSK9i/bempedoic acid 無此類證據,不能類推。
3 個小型試驗結果不一致(族群、樣本、follow-up 不同),但 meta-analysis 整體支持 statin 的 cardioprotective signal。
建議
對 high / very high cancer therapy-related CV toxicity risk(baseline stratification 走 2022 ESC cardio-oncology guidelines)的 anthracycline-treated 病人 → statin IIa B。不是 universal—只給高風險亞群。
機轉推測:statin 的 pleiotropic effect—antioxidant、anti-inflammatory、改善 endothelial function,可能緩衝 anthracycline 引起的 oxidative stress 與 cardiomyocyte injury。
實務眉角:
- Statin 副作用 risk(myopathy、hepatotoxicity)需要 monitor,但不會與 anthracycline 直接 drug interaction
- 對已有 dyslipidemia 的 cancer 病人雙重 benefit—降 CV 風險 + 降 anthracycline 心毒性
- 對「low CV toxicity risk」病人沒必要 universal statin—stratification 重要
其他 LLT(ezetimibe、PCSK9 mAb、bempedoic acid)對 cancer 心毒性沒有試驗證據—不能類推。
🔬 §10 飲食補充品 — 第一個 Class III B
為什麼需要這個 negative recommendation
市場上「lipid-lowering supplement」氾濫—red yeast rice、garlic、cinnamon、turmeric、fish oil capsules、phytosterols。許多病人「先試 supplements」拒絕 statin。2025 update 用明確的 negative recommendation 擋下這條路—沒有實證 safety + LDL-C lowering 的 supplements 一律 III B。
關鍵試驗
SPORT trial(JACC 2022)—single-center RCT, n=199, primary prevention:rosuvastatin 5 mg/day vs placebo vs 6 種 supplements(fish oil、cinnamon、garlic、turmeric、plant sterols、red yeast rice)。28 天 LDL-C 變化:
- Rosuvastatin:LDL-C↓~35%(壓倒性勝利)
- 所有 6 種 supplements:與 placebo 無差異
🧪 SPORT(2022, J Am Coll Cardiol)— statin 完勝 6 種降脂補充品
設計:單中心 RCT,199 名 10 年 ASCVD 風險升高的一級預防受試者,8 臂隨機:rosuvastatin 5 mg/day、placebo、與 6 種補充品(fish oil、cinnamon、garlic、turmeric、plant sterols、red yeast rice),觀察 28 天 LDL-C 變化。
結果:rosuvastatin 相對 placebo LDL-C 降 35.2%(壓倒性);6 種補充品與 placebo 無顯著差異;不良事件率各組相當。
臨床意義:與 OMEMI(PUFA post-MI 無效)一起,支撐「未證實 safety + LDL-C lowering 的 supplements 不推薦做為 ASCVD 預防」III B(dyslipidemia 指引首條 Class III)。限制:樣本小、只看 28 天 lipid 替代終點、無 outcome;但對「先試補充品再說」的病人衛教極有力。
SPORT 簡單明白地推翻 supplements 降 LDL-C 的宣稱。
OMEMI trial(Circulation 2020):n-3 PUFA(EPA+DHA)給 elderly post-MI 患者—無 outcome benefit。這加上 STRENGTH 確認「混合 PUFA supplements 沒 outcome value」。
個別補充品的狀態
| Supplement | LDL-C 降幅 | Outcome 證據 | 2025 立場 |
|---|---|---|---|
| Red yeast rice(low-dose, monacolin <3 mg/d) | 有 mild effect | 無 | 歐盟禁 ≥3 mg/day;<3 mg/day under restrictions |
| Phytosterols (≤2 g/day) | ~10% | 無 | 有降 LDL-C 但沒 outcome data—不推薦做為 ASCVD 預防 |
| Garlic / cinnamon / turmeric | None | 無 | SPORT 推翻 |
| Fish oil / EPA+DHA mix | None | STRENGTH negative | 不推薦做為 ASCVD 預防(icosapent ethyl 是處方藥例外) |
關鍵釐清:
- High-dose icosapent ethyl(2×2 g/day)≠ fish oil supplement—它是純化 EPA ethyl ester 處方藥,有 REDUCE-IT outcome benefit。Supplements form 的 fish oil 跟它完全不同。
- Red yeast rice 含 monacolin K = lovastatin—一些 high-dose 製劑等於低劑量未受監管的 statin,反而有 hepatotoxicity / myopathy 風險。歐盟已經為此祭出 ≥3 mg/day 的禁令。
- 飲食模式(Mediterranean diet、低飽和脂肪)仍然是 cornerstone—這是 2019 版的 healthy diet pattern,與 supplements 不同。
建議
Dietary supplements 或 vitamins 若沒有 documented safety + significant LDL-C lowering efficacy → not recommended for lowering ASCVD risk III B。這是 dyslipidemia guideline 的第一個 Class III。
📋 關鍵 Recommendations 對照表
| 建議 | Class / LOE | vs 2019 | 白話解讀 |
|---|---|---|---|
| Lp(a) >50 mg/dL(>105 nmol/L)視為 CV risk-enhancing factor | IIa B | 新建議 | 用來把 moderate 或閾值附近的病人往 high 重新分類 |
| Icosapent ethyl 2×2 g/day 與 statin 並用,給 high/very high risk + TG 135-499 mg/dL | IIa B | 取代 2019 泛指 n-3 PUFA 的建議 | 必須是純化 EPA、不是 EPA+DHA mixture、不是 supplement form |
| Volanesorsen 300 mg/week,給 FCS 患者 + TG >750 mg/dL,降胰臟炎風險 | IIa B | 新建議 | EMA 核准(FDA 未核准);嚴重 thrombocytopenia 需 monitor |
| HIV ≥40 歲一律 statin(不看 LDL-C / SCORE2),降 CV event 風險;選 statin 看 drug interaction | I B | 從 IIa 升 I(REPRIEVE) | Universal primary prevention;pitavastatin 是 default 選擇 |
| Statin 給 high/very high cancer therapy-related CV toxicity risk 病人,預防 anthracycline-induced LVEF↓ | IIa B | 新建議(與 2022 ESC cardio-oncology 一致) | 對齊 STOP-CA;只給高風險亞群 |
| 未證實 safety + LDL-C lowering 的 dietary supplements 或 vitamins 不推薦做為 ASCVD 預防 | III B | 新建議 | 第一個 Class III;包括 red yeast rice、garlic、cinnamon、turmeric、混合 PUFA、phytosterols |
✅ 重點回顧
- Lp(a):成人一生至少測一次(>90% 由基因決定);>50 mg/dL(>105 nmol/L)是 risk-enhancing factor IIa B。Statin 對 Lp(a) 沒效,但 Lp(a) 高的人仍應 high-intensity statin(把 LDL-C 降到底)。Lp(a)-lowering 藥物 outcome 還在等。
- Hypertriglyceridaemia:Statin 仍是第一線;只有純化 high-dose icosapent ethyl(不是混合 PUFA、不是 supplement form)給 statin + TG 135-499 mg/dL high/very high risk IIa B;Volanesorsen 給 FCS >750 mg/dL IIa B。Fibrate IIb(pemafibrate 被 PROMINENT 推翻)。
- HIV:≥40 歲 PWH 一律 statin I B,不看 LDL-C 不看 SCORE2。Pitavastatin 4 mg 是 default(drug interaction 最少)。其他 statin 需注意 protease inhibitor 交互作用。
- Cancer:High / very high cancer therapy-related CV toxicity risk 病人,anthracycline 治療 + statin 預防 LVEF↓ IIa B。Baseline risk stratification 走 2022 ESC cardio-oncology。
- 飲食補充品:沒實證 safety + LDL-C lowering 的 supplements 一律 III B。釐清 high-dose icosapent ethyl 是處方藥不算 supplement、red yeast rice 高劑量等於未受監管的 statin、phytosterols 雖降 LDL-C 但無 outcome data。
- 共同精神:「LDL-C 以外」的問題用實證導向處理—negative trial(PROMINENT、STRENGTH、SPORT、OMEMI)和 positive trial(REPRIEVE、STOP-CA、APPROACH、CLEAR、ELIPSE)都精準塑形 2025 update 的建議。
📖 References
- Mach F, Koskinas KC, Roeters van Lennep JE, et al. 2025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias. Eur Heart J 2025;46(42):4359–4378. doi:10.1093/eurheartj/ehaf190
- Mach F, Baigent C, Catapano AL, et al. 2019 ESC/EAS Guidelines for the management of dyslipidaemias. Eur Heart J 2020;41:111–188.
- Kronenberg F, Mora S, Stroes ESG, et al. Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement. Eur Heart J 2022;43:3925–3946.
- Madsen CM, Kamstrup PR, Langsted A, et al. Lipoprotein(a)-lowering by 50 mg/dL (105 nmol/L) may be needed to reduce cardiovascular disease 20%. Arterioscler Thromb Vasc Biol 2020;40:255–266.
- Bhatt DL, Steg PG, Miller M, et al. Cardiovascular Risk Reduction with Icosapent Ethyl for Hypertriglyceridemia (REDUCE-IT). N Engl J Med 2019;380:11–22. doi:10.1056/NEJMoa1812792
- Nicholls SJ, Lincoff AM, Garcia M, et al. Effect of High-Dose Omega-3 Fatty Acids vs Corn Oil on Major Adverse Cardiovascular Events in Patients at High Cardiovascular Risk (STRENGTH). JAMA 2020;324:2268–2280.
- Das Pradhan A, Glynn RJ, Fruchart JC, et al. Triglyceride Lowering with Pemafibrate to Reduce Cardiovascular Risk (PROMINENT). N Engl J Med 2022;387:1923–1934.
- Witztum JL, Gaudet D, Freedman SD, et al. Volanesorsen and Triglyceride Levels in Familial Chylomicronemia Syndrome (APPROACH). N Engl J Med 2019;381:531–542.
- Grinspoon SK, Fitch KV, Zanni MV, et al. Pitavastatin to Prevent Cardiovascular Disease in HIV Infection (REPRIEVE). N Engl J Med 2023;389:687–699. doi:10.1056/NEJMoa2304146
- Neilan TG, Quinaglia T, Onoue T, et al. Atorvastatin for Anthracycline-Associated Cardiac Dysfunction (STOP-CA). JAMA 2023;330:528–536. doi:10.1001/jama.2023.11887
- Laffin LJ, Bruemmer D, Garcia M, et al. Comparative Effects of Low-Dose Rosuvastatin, Placebo, and Dietary Supplements on Lipids and Inflammatory Biomarkers (SPORT). J Am Coll Cardiol 2022;80:1075–1086. doi:10.1016/j.jacc.2022.10.013
- Kalstad AA, Myhre PL, Laake K, et al. Effects of n-3 Fatty Acid Supplements in Elderly Patients After Myocardial Infarction (OMEMI). Circulation 2021;143:528–539.
- 2022 ESC Guidelines on cardio-oncology developed in collaboration with the European Hematology Association (EHA), the European Society for Therapeutic Radiology and Oncology (ESTRO) and the International Cardio-Oncology Society (IC-OS). Eur Heart J 2022;43:4229–4361.
本文以教學為目的整理 2025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias,所有原文 Figure 之版權屬 ESC/EAS;商業使用請洽 ESC 取得授權。
