

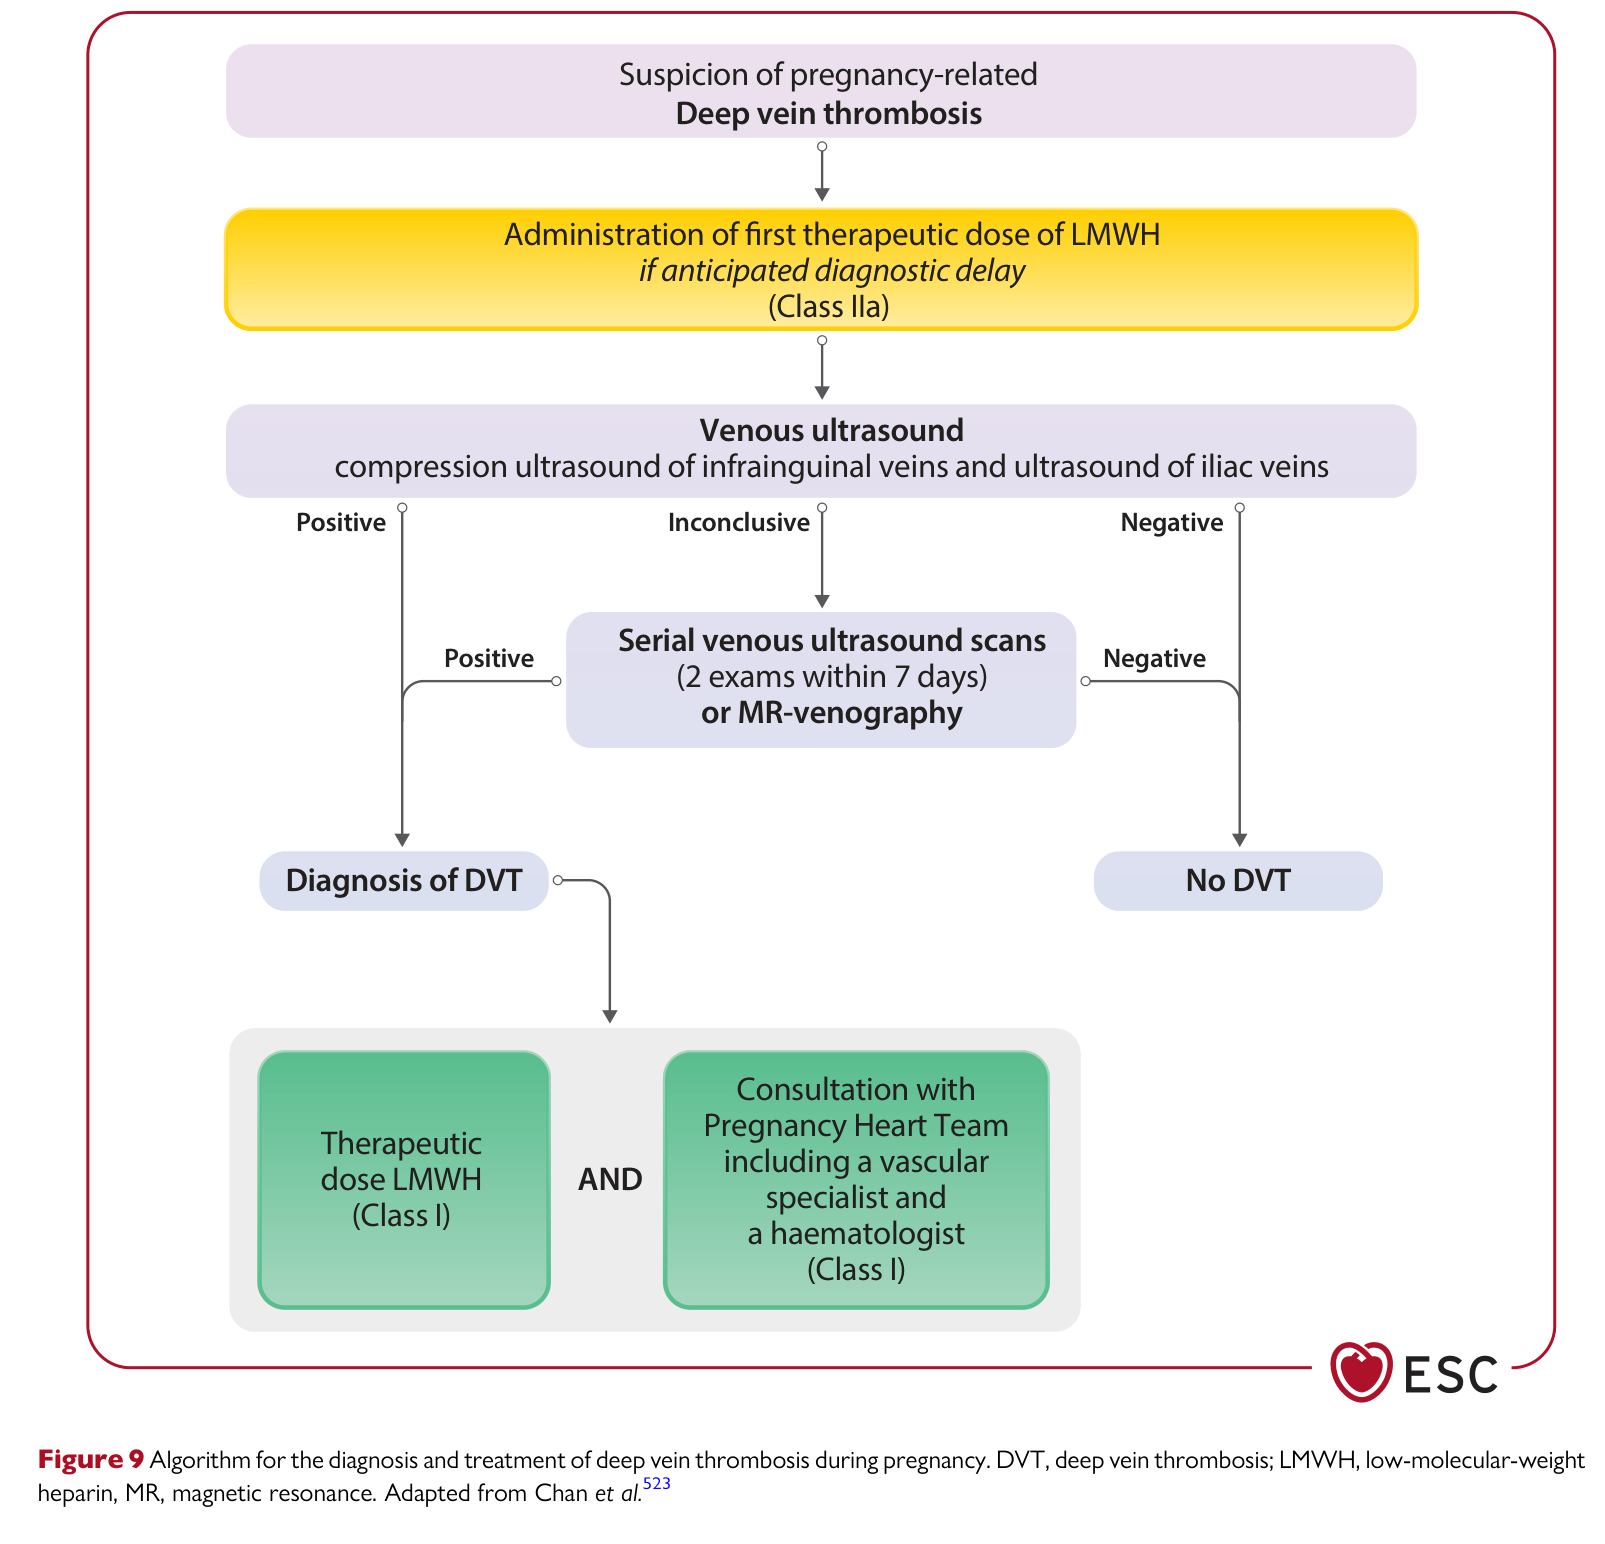
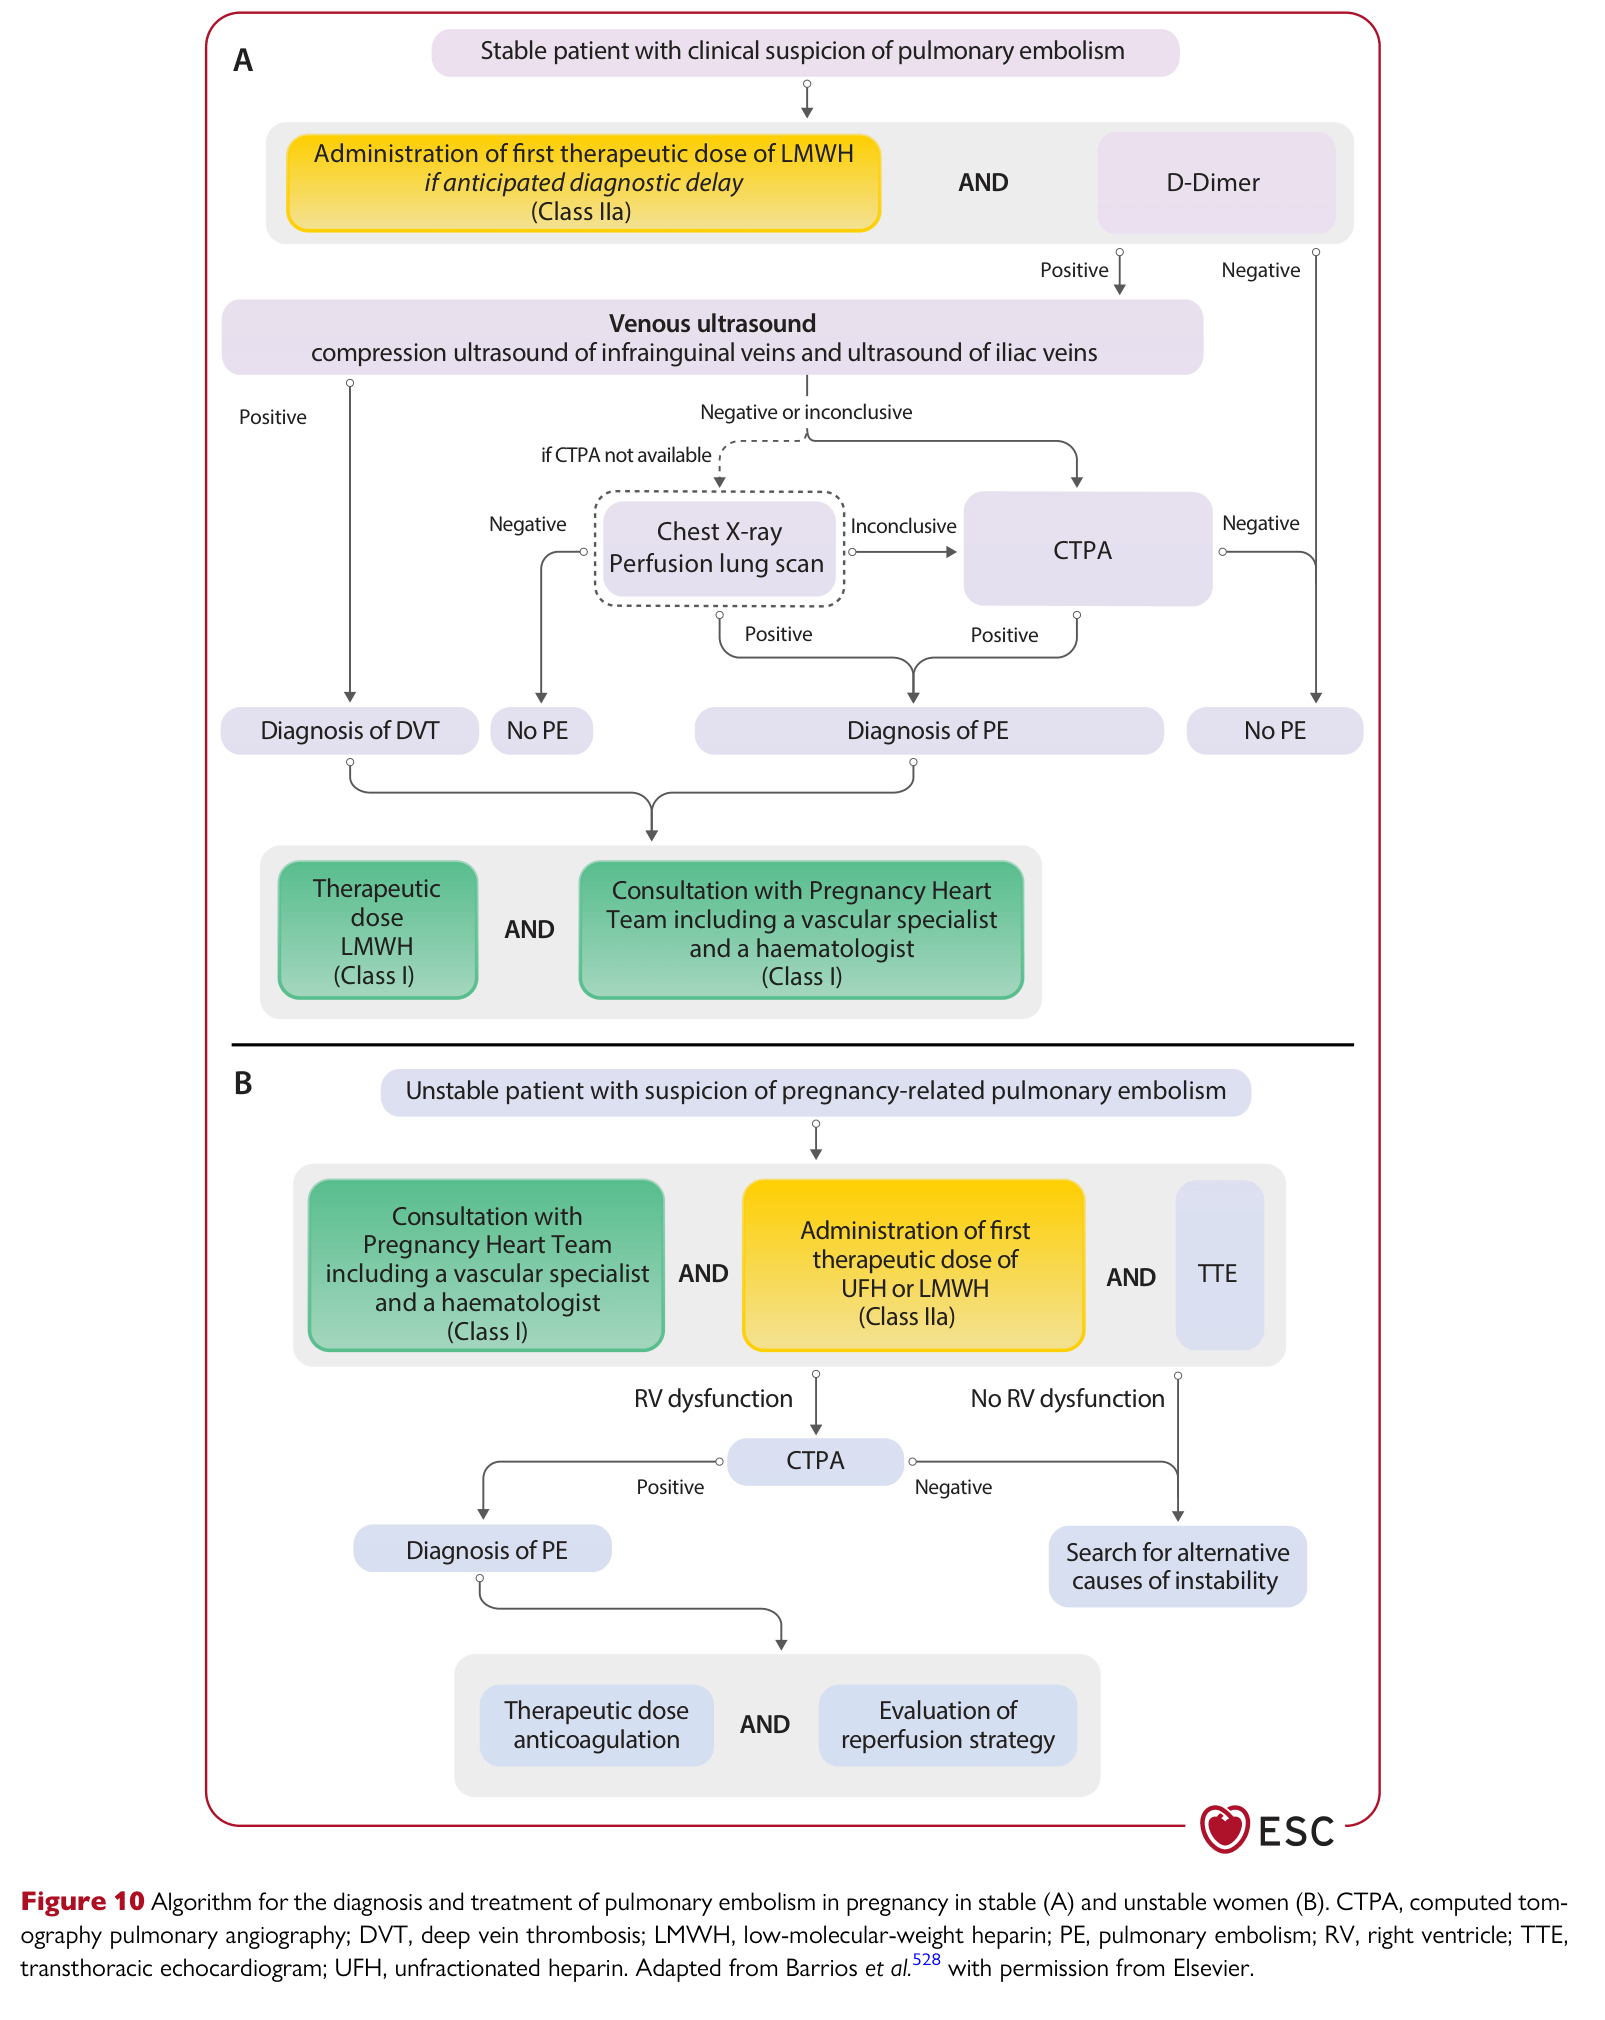
- VTE 診斷不可拖延:immediate formal diagnostic assessment I B;若預期 delay → administration of first therapeutic LMWH dose IIa(Fig 9/10 兩張流程)。
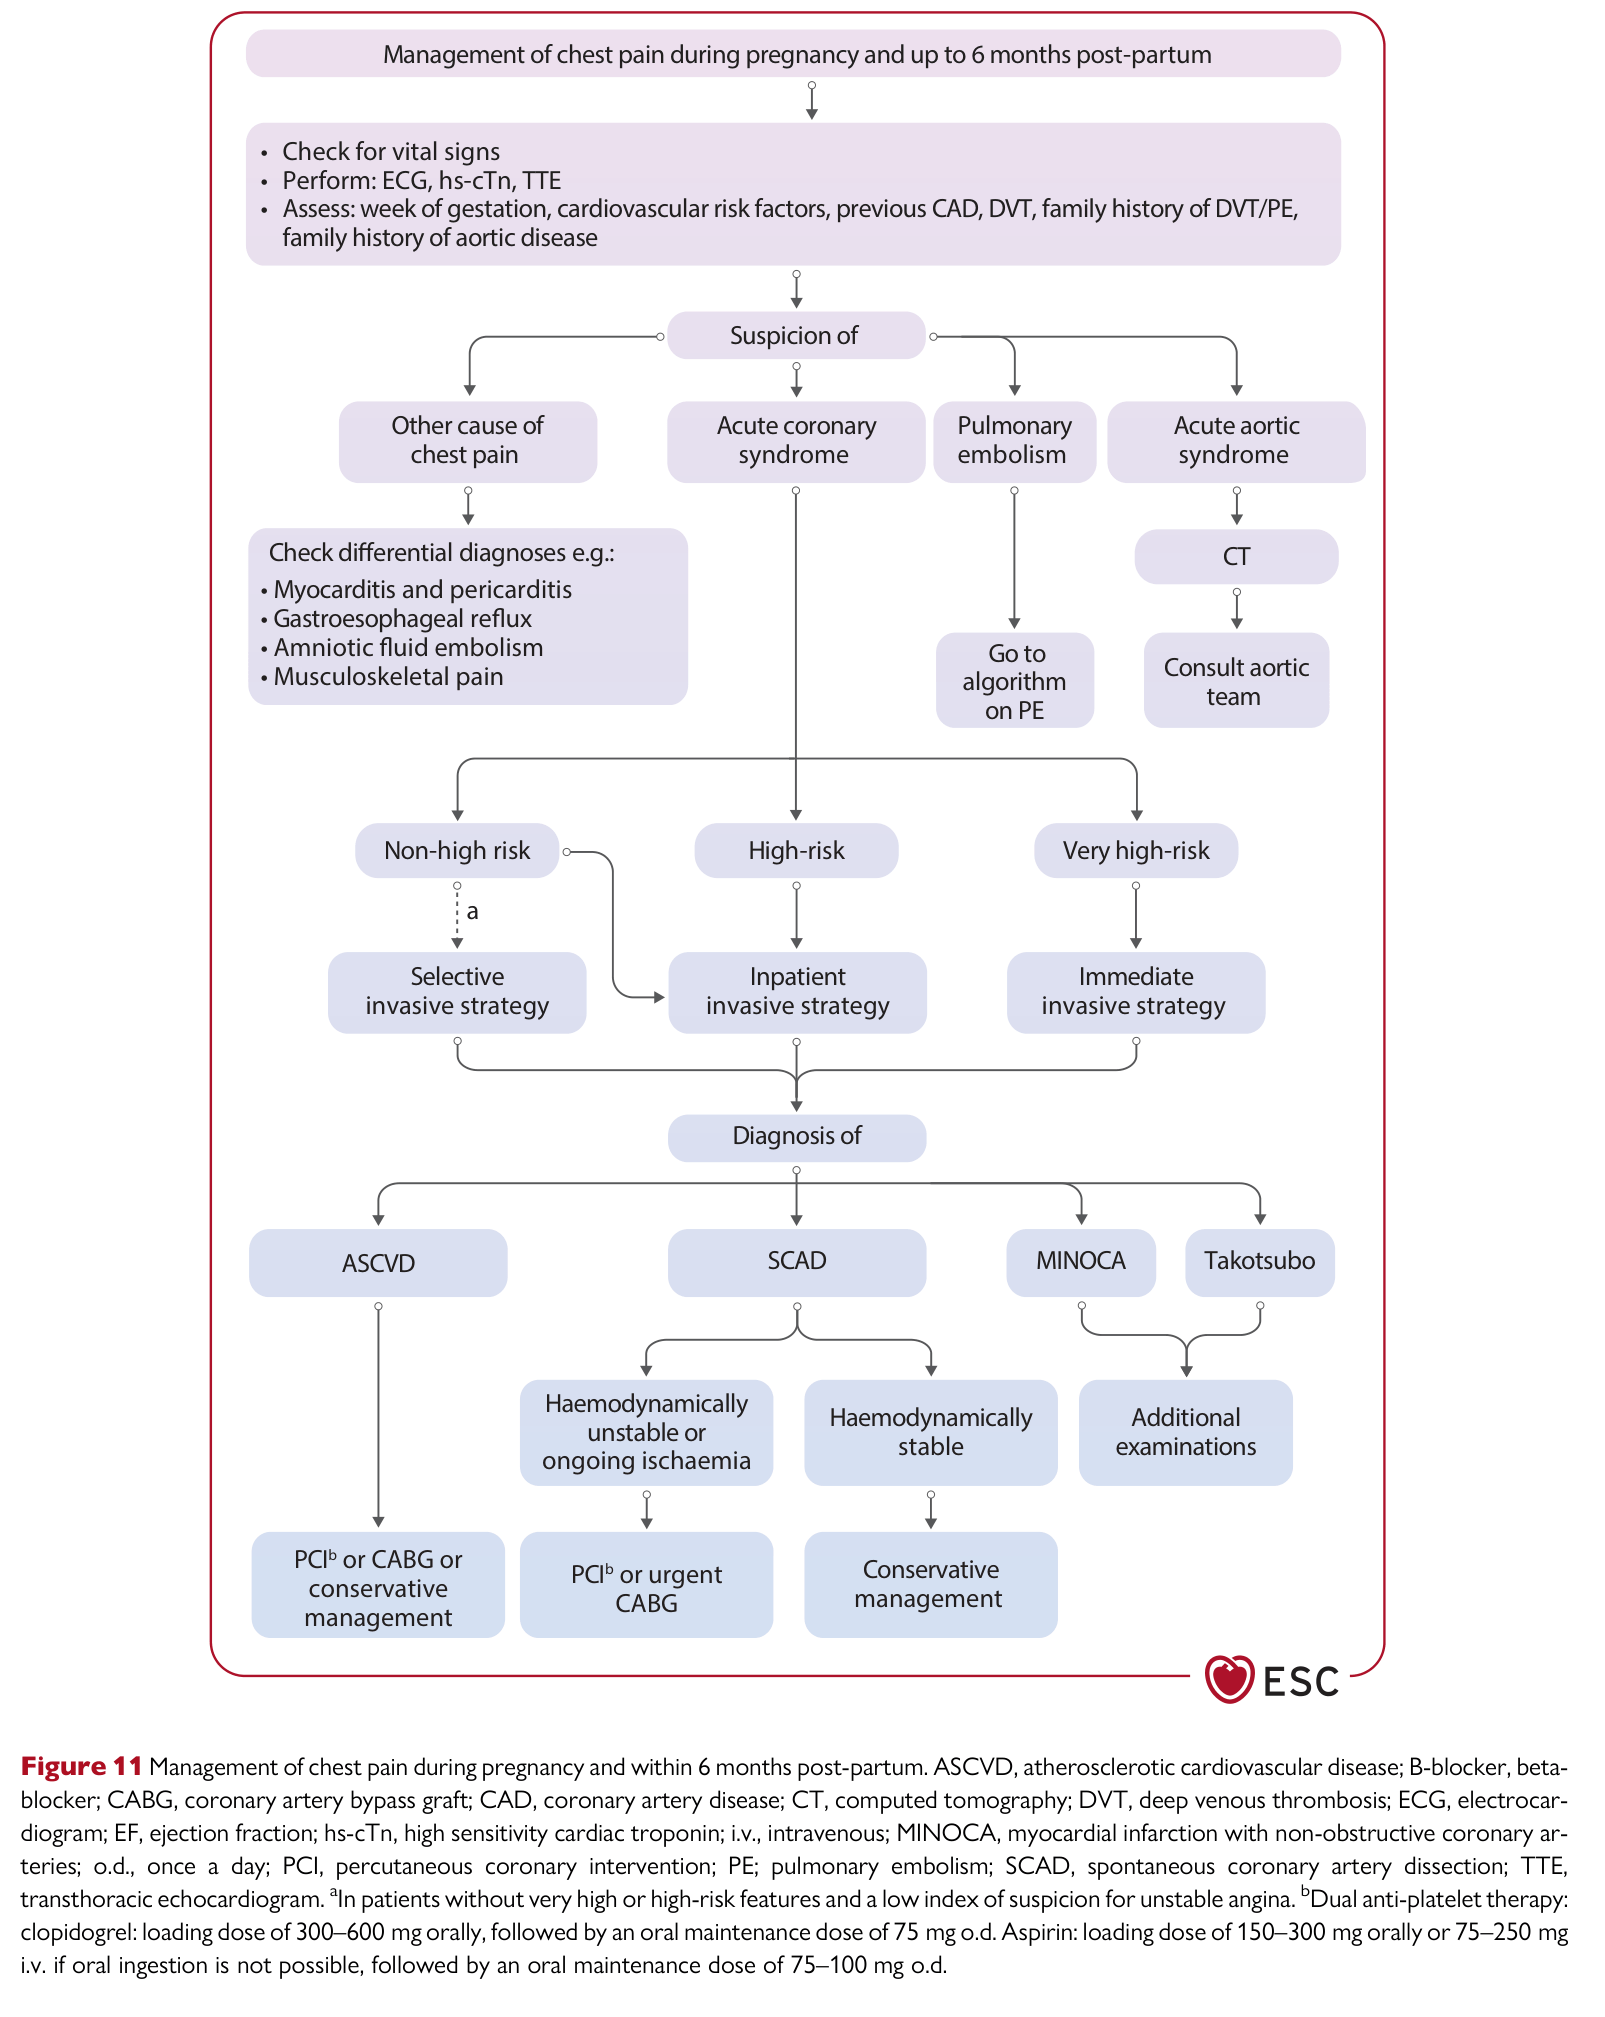
- 妊娠胸痛 Fig 11 一張圖搞定:先排 PE / acute aortic syndrome / ACS(含 SCAD);SCAD 是妊娠 ACS 主因(≥40%);ASCVD / SCAD / MINOCA / Takotsubo 各有不同處置;DAPT 期程與非孕婦相同 I C。
- HDP(Hypertensive Disorders of Pregnancy)BP target <140/90 I B(CHAP trial)—2018 是 <150/100 或不明確,2025 更積極。Severe HTN 一線 IV labetalol / urapidil / nicardipine 或 oral nifedipine / methyldopa I C。
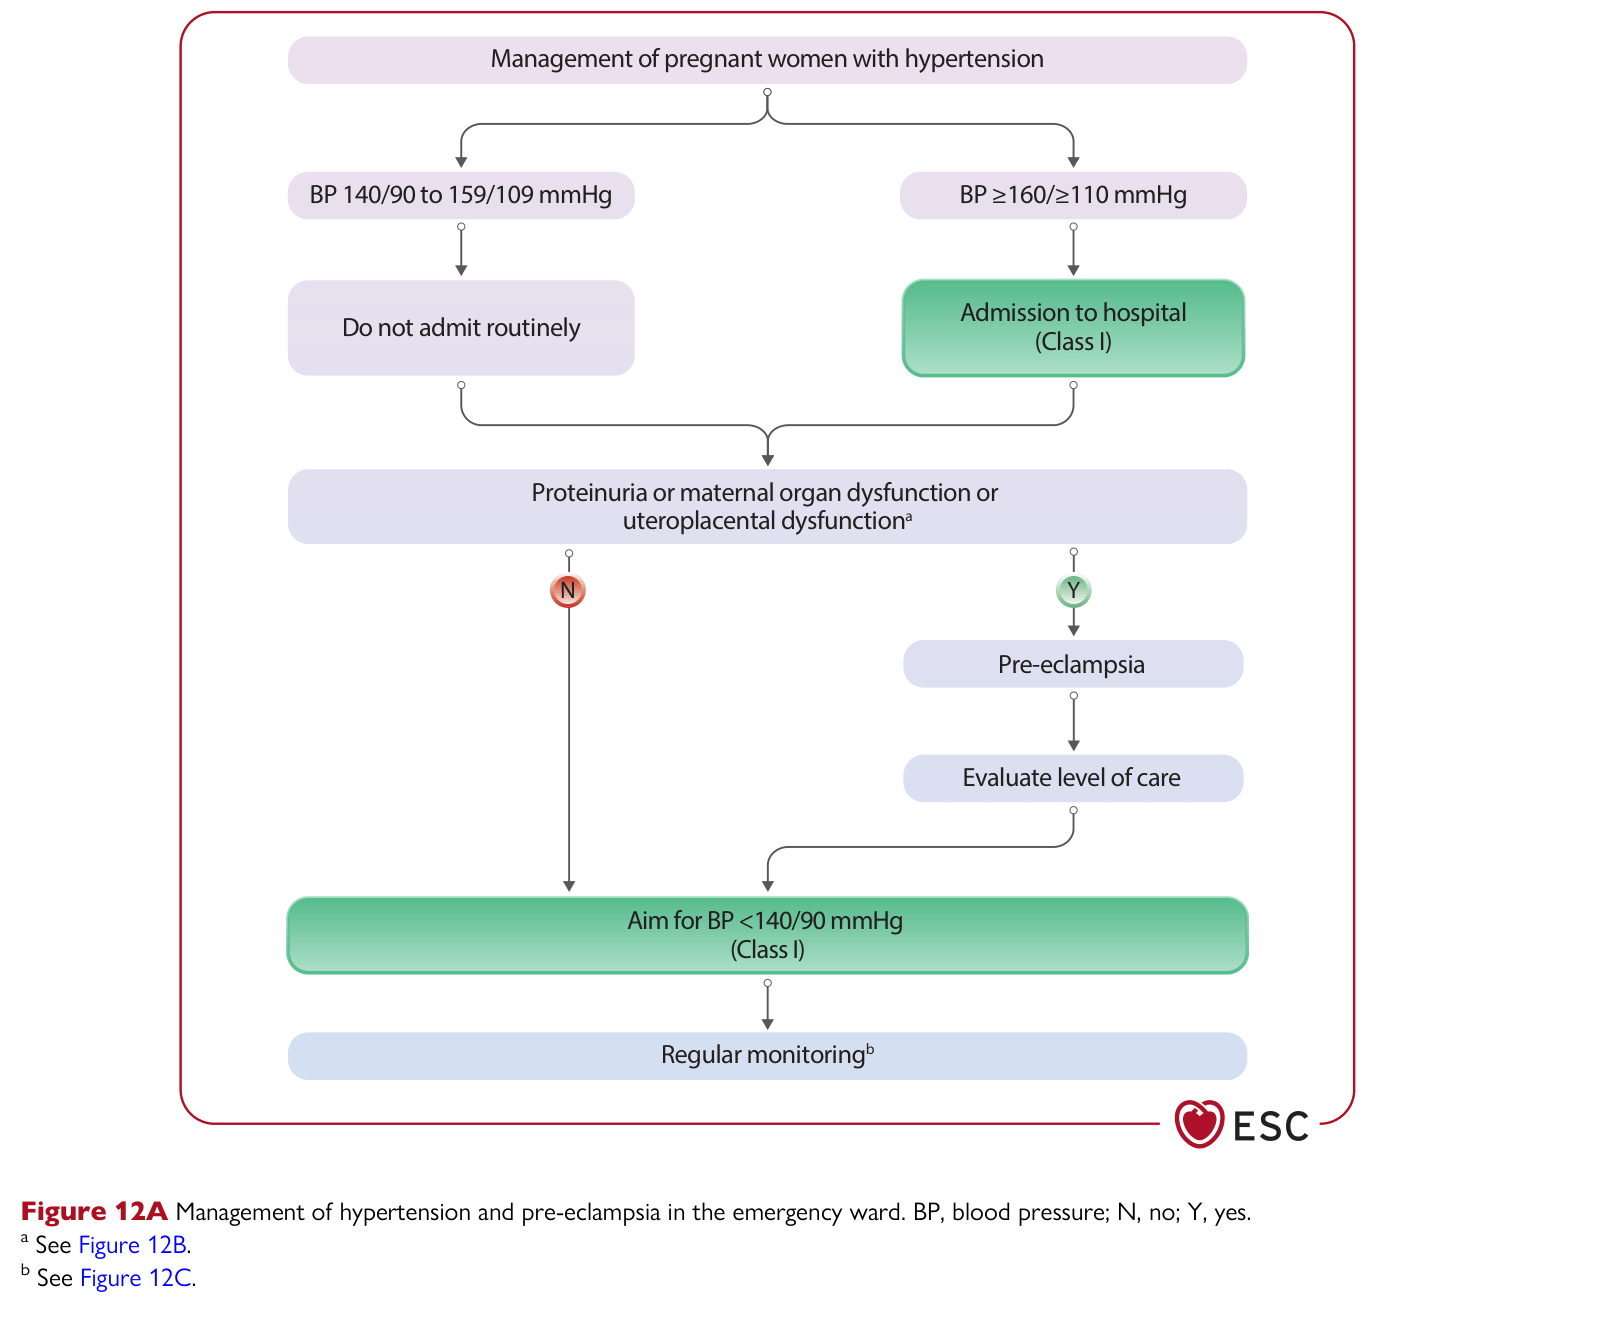
- Figure 12A/B/C 三張圖串成 HDP 完整流程:12A = 急診分流 → 12B = 蛋白尿/pre-eclampsia 診斷 → 12C = monitoring + treatment 矩陣。
🩸 §11 Venous Thromboembolism — 新版兩張獨立 algorithm
整體立場
- 妊娠 + 產後是 4-5 倍 baseline VTE 風險的時期,產後 6 週尤甚(10x)。
- 2025 版用專屬 algorithm(Fig 9 DVT、Fig 10 PE)取代 2018 散落的描述。
- 關鍵原則:不要等檢查、診斷不確定就先抗凝(anticipated diagnostic delay → empiric LMWH)。
🖼️ Figure 9 — DVT 診斷與治療 algorithm
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 9
這張圖在回答什麼問題:懷疑孕婦有 DVT,怎麼從 suspicion 走到 confirmed Dx + treatment?
- Positive → Diagnosis of DVT → 進 Step 5。
- Inconclusive → 進 Step 4。
- Negative → 進 Step 4。
容易踩雷的地方:
🖼️ Figure 10 — PE 診斷與治療(穩定 vs 不穩定分流)
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 10
分上下兩半:A = stable PE;B = unstable PE。
- Step A1:Administration of first therapeutic dose of LMWH if anticipated diagnostic delay IIa。同時 D-Dimer(用於 algorithm 排除策略,非單獨決策)。
- Step A2:Venous ultrasound(compression of infrainguinal + iliac)。Positive / Negative-or-inconclusive 分流。
- Step A3(if compression US +):Diagnosis of DVT 確認 → 治療同 Fig 9 Step 5。
- Step A4(if US -):If CTPA not available → Chest X-ray + perfusion lung scan(V/Q);若 CTPA available → 直接 CTPA。
- Step A5:Diagnosis of PE 確認 → Therapeutic dose LMWH I + PHT including vascular + haematologist consultation I。
- Step B1:Consultation with PHT including vascular + haematologist I。
- Step B2:Administration of first therapeutic dose of UFH or LMWH I(不等診斷確認)。
- Step B3:TTE 評估 RV dysfunction。
- Step B4:If RV dysfunction → CTPA → Diagnosis of PE → Therapeutic dose anticoagulation + Evaluation of reperfusion strategy(systemic thrombolysis、catheter-directed thrombolysis、surgical embolectomy 視臨床)。
- Step B5:If no RV dysfunction → Search for alternative causes of instability。
容易踩雷的地方:
💔 §12.1 – 12.2 妊娠胸痛與 CAD
妊娠 CAD 的特殊性
- 盛行率 1.5-10/100,000 妊娠,產後較孕期高。
- SCAD(spontaneous coronary artery dissection)是主因—妊娠 ACS 中 SCAD 佔 ≥40%(vs 一般族群 ~1%)。
- 典型 ASCVD ACS 較少(年輕)但仍可能(特別有家族史、HDP 史、亞洲族群)。
- MINOCA(myocardial infarction with non-obstructive coronary arteries)與 Takotsubo 也常見於孕期與產後。
🖼️ Figure 11 — 妊娠胸痛鑑別 algorithm
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 11
這張圖在回答什麼問題:妊娠期 + 產後 6 個月內出現 chest pain,如何 systematic 鑑別 + 處置?
- Other cause of chest pain:myocarditis、pericarditis、GE reflux、amniotic fluid embolism、musculoskeletal → 對應檢查與處置。
- Acute coronary syndrome (ACS) → Step 3 ACS branch。
- Pulmonary embolism → Go to algorithm on PE(Fig 10)。
- Acute aortic syndrome → CT + Consult aortic team(極緊急)。
- Non-high-risk → Selective invasive strategy(unstable angina or NSTEMI 風險中等)。
- High-risk → Inpatient invasive strategy。
- Very high-risk → Immediate invasive strategy(ongoing ischaemia, life-threatening arrhythmia, haemodynamic instability)。
- ASCVD → 標準 ACS 治療:BB + aspirin + statin(若 ASCVD)+ PCI/CABG(atherosclerotic disease)。Conservative or revascularization based on lesion.
- SCAD:分穩定不穩定 + ischaemic activity:
- Haemodynamically unstable or ongoing ischaemia → PCIa or urgent CABG。
- Haemodynamically stable → Conservative management(80-95% 自發 heal in 30 天)。
- MINOCA → Additional examinations(IVUS、OCT、CMR)找 root cause。
- Takotsubo → Supportive management + ACEi(避免妊娠用)or BB(safe)。
容易踩雷的地方:
CAD 重點 Recommendations
| 建議 | COR/LOE |
|---|---|
| 妊娠胸痛 → 排 PE、ACS(含 SCAD)、acute aortic syndrome | I C |
| DAPT 持續期同非孕婦(依 ischaemic vs bleed 個別評估) | I C |
| Statin 在 established ASCVD 可考慮繼續 | IIb C |
| P2Y12 首選 clopidogrel(妊娠資料最多) | IIa C |
🩺 §12.3 Hypertensive Disorders of Pregnancy (HDP)
HDP 分類(Table 14)
| 類型 | 定義 |
|---|---|
| Chronic hypertension | Pre-pregnancy 或 <20 週 BP ≥140/90,持續到產後 |
| Gestational hypertension | ≥20 週 new-onset BP ≥140/90,無 proteinuria 或 multi-organ dysfunction |
| Pre-eclampsia | ≥20 週 new-onset HTN + proteinuria 或 multi-organ dysfunction 或 uteroplacental dysfunction |
| Pre-eclampsia superimposed on chronic HTN | Chronic HTN + 新出現 proteinuria 或 organ dysfunction |
| Eclampsia | Pre-eclampsia + seizure |
| HELLP | Haemolysis、Elevated Liver enzymes、Low Platelets — pre-eclampsia 嚴重變化型 |
BP target 與 drug 建議(重大改變)
| 建議 | COR/LOE | vs 2018 |
|---|---|---|
| BP target SBP <140 mmHg + DBP <90 mmHg | I B | 2018 不明確或 <150/100 — 變更明確 |
| Severe HTN(≥160/110):IV labetalol / urapidil / nicardipine 或 oral nifedipine / methyldopa(IV hydralazine 二線) | I C | 更明確 drug list |
| Pre-eclampsia (≥20 wk) high-risk women 用 aspirin 預防(80-150 mg qd from 12-16w to 36w) | I A | 確認 |
| Magnesium sulfate for eclampsia + severe pre-eclampsia (seizure prevention) | I A | 確認 |
支撐 trial — 為什麼 BP target 變積極、為什麼 high-risk 要 aspirin
🧪 CHAP(2022, N Engl J Med)— 撐起「mild chronic HTN 也該積極降壓到 <140/90」
設計:open-label RCT,2,408 名 singleton、mild chronic hypertension(<160/110 mmHg)、孕週 <23 週的孕婦;隨機分 active treatment(門檻 140/90 mmHg 即啟動/調整降壓藥,首選 labetalol 或 extended-release nifedipine)vs control(不治療直到 SBP ≥160 或 DBP ≥105 才介入)。Primary composite = severe-feature pre-eclampsia + medically-indicated preterm <35 週 + placental abruption + fetal/neonatal death。
結果:primary composite 30.2% vs 37.0%,adjusted RR 0.82(95% CI 0.74–0.92;P<0.001)。安全性關鍵終點 SGA <10th percentile 11.2% vs 10.4%,adjusted RR 1.04(95% CI 0.82–1.31;P=0.76) — 積極降壓未增加胎兒生長受限。
臨床意義:直接撐起本指引 HDP「BP target SBP <140 + DBP <90」I B 的升級(2018 為 <150/100 或不明確)。它推翻了「積極降壓會犧牲 placental perfusion → fetal growth」的舊顧慮。限制/易踩雷:open-label(非雙盲);族群是 chronic HTN,不可外推到 gestational HTN / pre-eclampsia 的急性降壓門檻;多數受試者用 labetalol / nifedipine,並非每種降壓藥都驗證過。
🧪 ASPRE(2017, N Engl J Med)— 撐起「high-risk 孕婦 12–16 週起低劑量 aspirin 預防 preterm pre-eclampsia」
設計:multicenter、double-blind、placebo-controlled RCT;以 first-trimester combined screening 篩出 preterm pre-eclampsia 高風險的 singleton 孕婦 1,776 名,隨機分 aspirin 150 mg 每晚(孕 11–14 週起至 36 週)vs placebo。Primary outcome = preterm pre-eclampsia(<37 週分娩)。
結果:preterm pre-eclampsia 1.6%(13/798)vs 4.3%(35/822),OR 0.38(95% CI 0.20–0.74;P=0.004),相對風險下降約 62%。中性訊號要誠實寫:對 term pre-eclampsia 無顯著效果;安全性(出血、placental abruption)兩組相當。
臨床意義:撐起本指引 high-risk women 用 aspirin 80–150 mg qd、自 12–16 週用到 36 週預防 pre-eclampsia 的 I A 建議。限制/易踩雷:得益主要落在 preterm 而非 term pre-eclampsia;療效高度依賴 compliance(事後分析顯示遵從度 <90% 者效益消失)與睡前服用;且建立在 first-trimester 風險演算法篩選之上,與只用病史挑高風險的策略效益不完全等價。
🖼️ Figure 12A — 急診 HDP 急性處置流程
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 12A
- BP 140/90 to 159/109 mmHg → Do not admit routinely → 進 Step 3。
- BP ≥160/110 mmHg → Admission to hospital I → 進 Step 3。
- N(無) → 進 Step 5(直接 aim for BP)。
- Y(有) → Pre-eclampsia 診斷 → Evaluate level of care → 進 Step 5。
🖼️ Figure 12B — Pre-eclampsia 診斷詳細
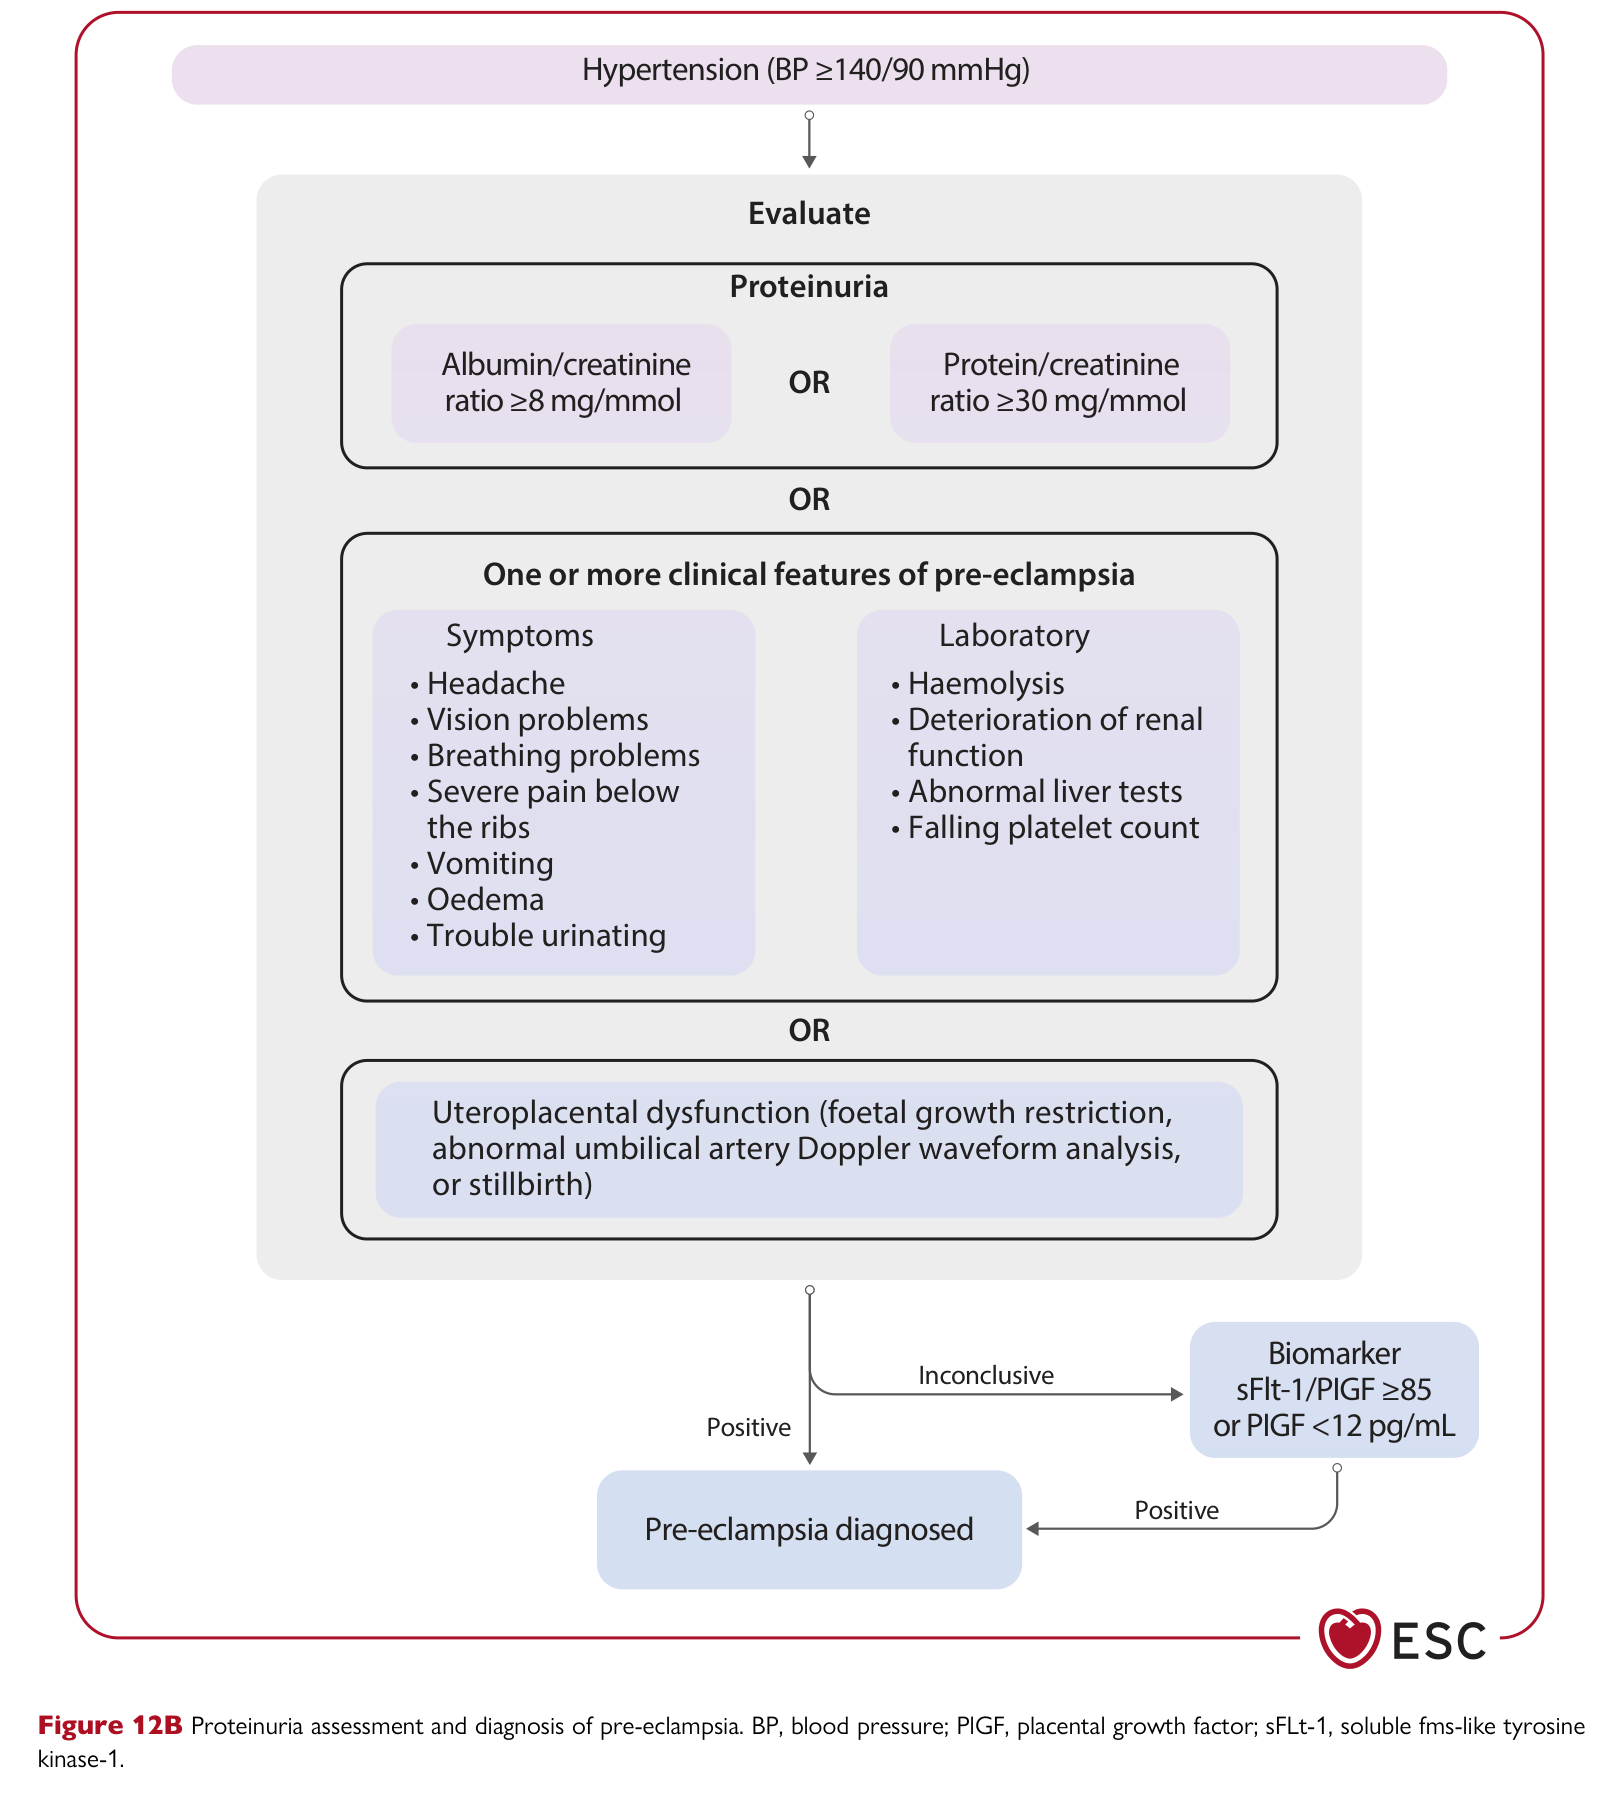
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 12B
- Symptoms:headache、vision problems、breathing problems、severe pain below the ribs、vomiting、oedema、trouble urinating
- Laboratory:haemolysis、deterioration of renal function、abnormal liver tests、falling platelet count
實務意涵:sFlt-1/PlGF 比值(angiogenic factor)在 inconclusive 情境是新的 biomarker tool。≥85 高度暗示 pre-eclampsia within 1-4 週,PlGF <12 也是強 predictor。NICE 已 endorsed 此 biomarker 策略。
🖼️ Figure 12C — Monitoring + treatment 矩陣
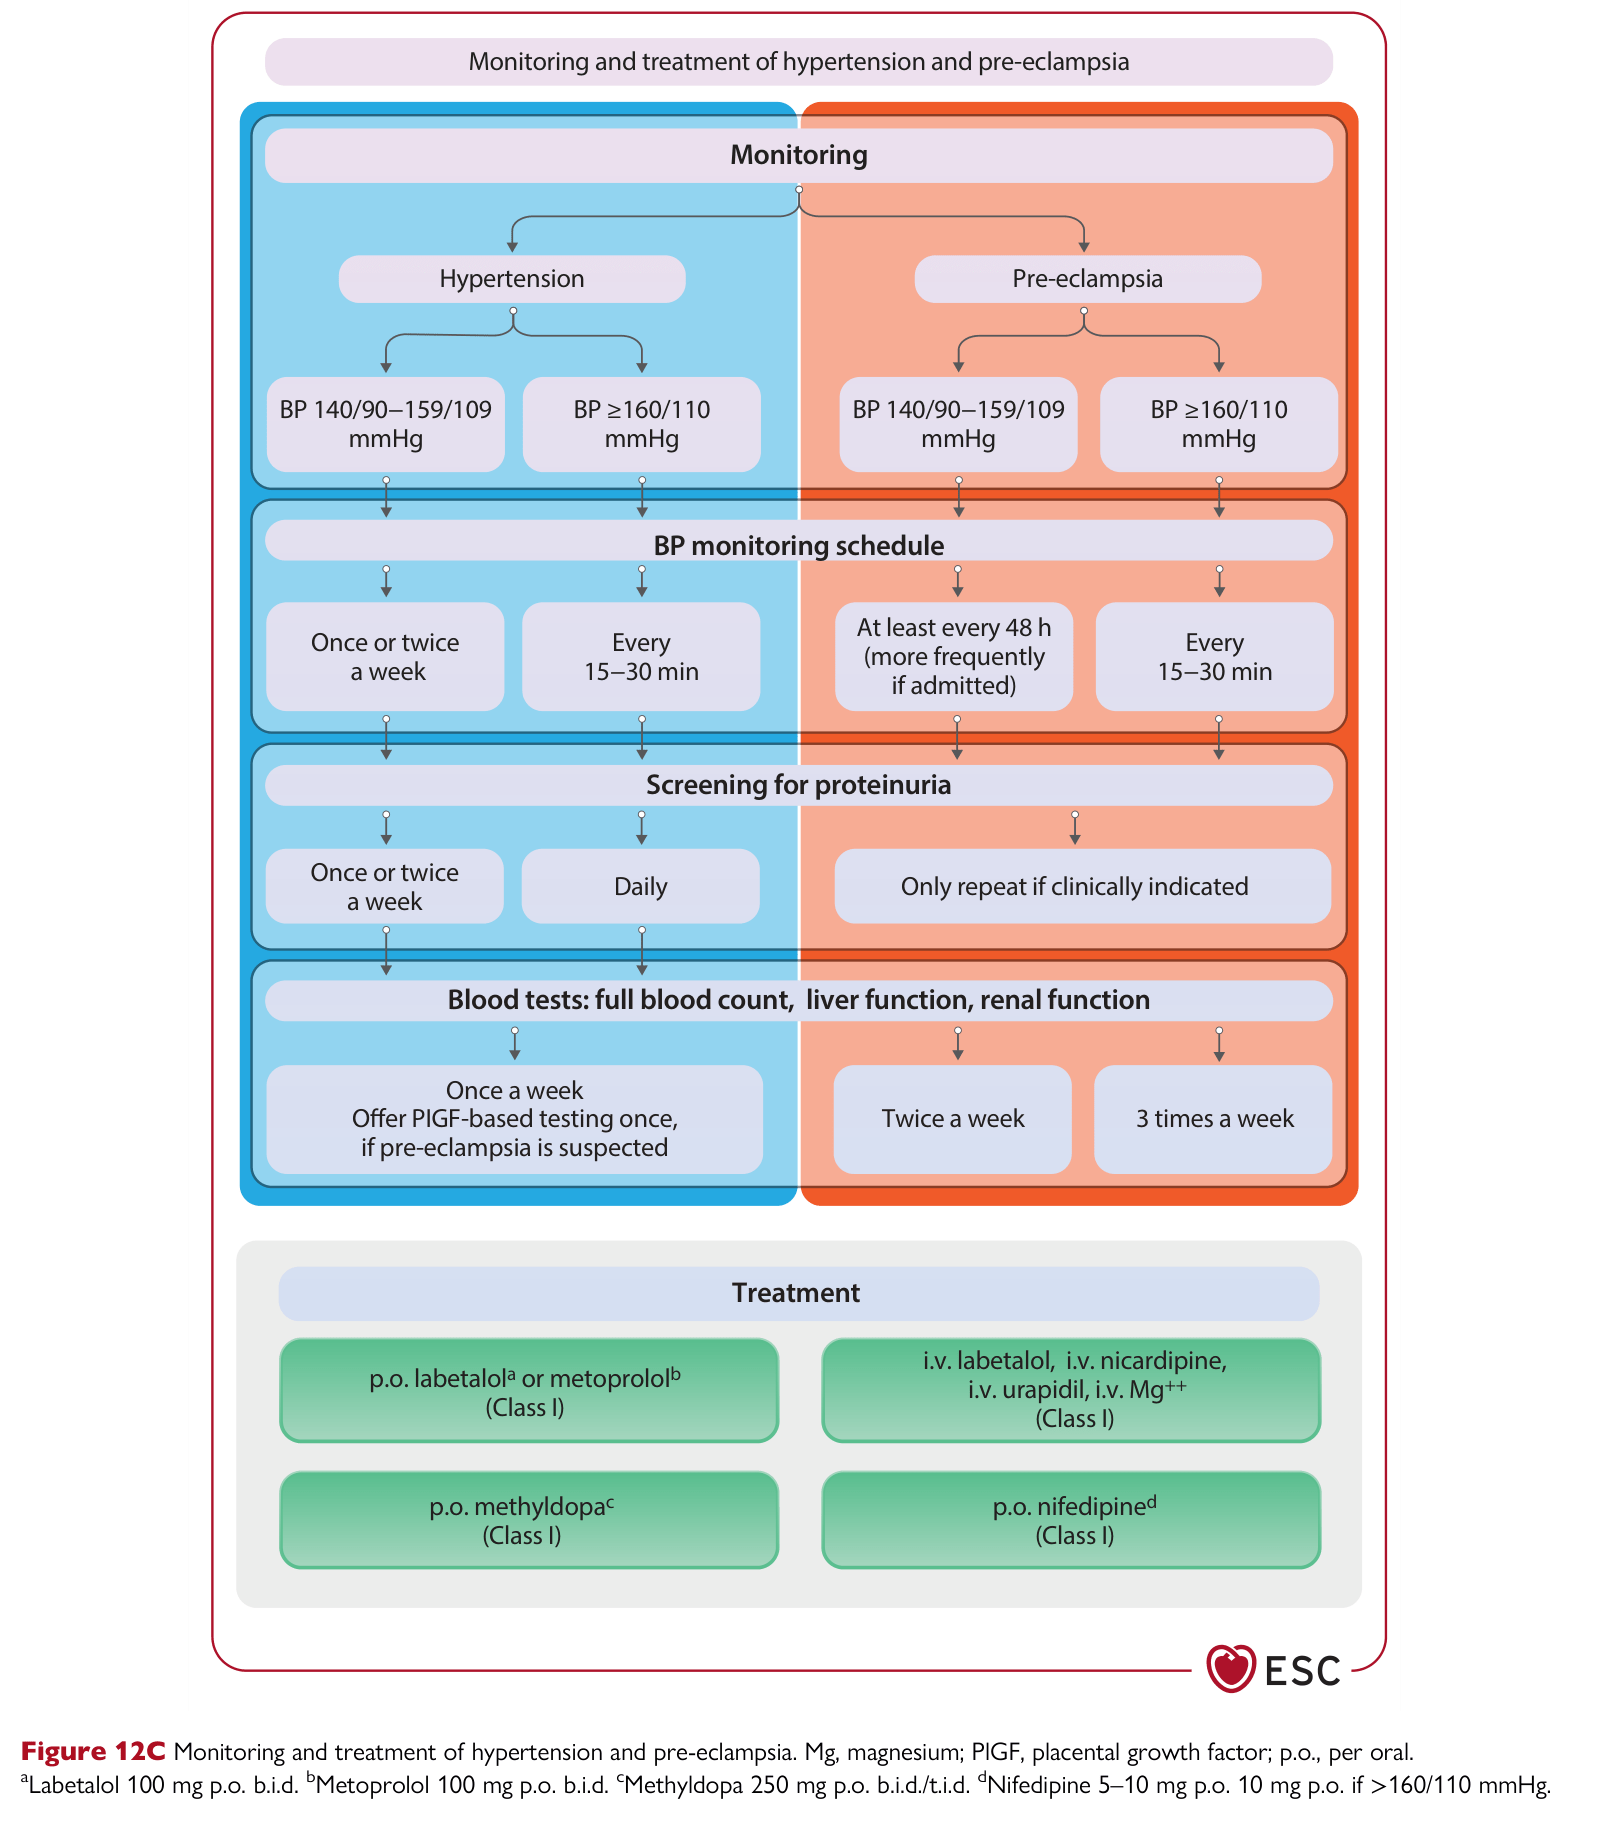
來源:2025 ESC Guidelines for the management of cardiovascular disease and pregnancy (Eur Heart J, doi:10.1093/eurheartj/ehaf193) — 個人教學使用,原始版權屬 ESC。
🧭 圖表逐步解析:Figure 12C
分上下兩段:上 = Monitoring;下 = Treatment。
| 項目 | HTN BP 140/90-159/109 | HTN BP ≥160/110 | Pre-eclampsia BP 140/90-159/109 | Pre-eclampsia BP ≥160/110 |
|---|---|---|---|---|
| BP monitoring | 每週 1-2 次 | 每 15-30 min | 至少 48h 內每 4h(住院更頻密) | 每 15-30 min |
| Proteinuria screening | 每週 1-2 次 | Daily | — | 視需要 |
| Blood tests | 每週 1 次;suspected pre-eclampsia 時加 PlGF-based | — | 每週 2 次 | 每週 3 次 |
| BP 範圍 | 一線藥物 |
|---|---|
| 140/90-159/109 | p.o. labetalola(Class I);p.o. methyldopac(Class I) |
| ≥160/110 | i.v. labetalol、i.v. nicardipine、i.v. urapidil、i.v. Mg++(Class I);p.o. nifedipine 5-10 mgd(Class I) |
標註:
- aLabetalol 100 mg po bid
- bMetoprolol 100 mg po bid(避免在 HDP,主要 LQTS 用)
- cMethyldopa 250 mg po tid/qid
- dNifedipine 5-10 mg po q10 min if >160/110 mmHg
容易踩雷的地方:
📋 §11-12.3 重點 Recommendations 整理
| 主題 | 2025 建議 | COR/LOE | vs 2018 |
|---|---|---|---|
| VTE:immediate formal diagnostic assessment | 不可拖延,suspected → 立即評估 | I B | 新加 |
| Anticipated diagnostic delay → first LMWH dose | VTE 高度懷疑但 imaging 延遲 | IIa | 新加 |
| Chest pain → 排 PE / ACS / aortic syndrome | 胸痛系統性鑑別 | I C | 新加 |
| DAPT duration same as non-pregnant | 依 ischaemic vs bleed 個別評估 | I C | 新加 |
| Statin in established ASCVD | 可考慮繼續 | IIb C | 新加 |
| BP target SBP <140 + DBP <90 | 全部 HDP 適用 | I B | 升級(CHAP) |
| Severe HTN drugs | i.v. labetalol / urapidil / nicardipine 或 oral short-acting nifedipine / methyldopa | I C | 明確化 |
| Pre-eclampsia prevention aspirin | High-risk women,80-150 mg qd from 12-16w to 36w | I A | 延續 |
| Magnesium sulfate | Eclampsia + severe pre-eclampsia seizure prevention | I A | 延續 |
- VTE(Fig 9/10):不要等檢查,suspected + anticipated delay → first LMWH dose IIa;compression US 含 iliac veins、confirmed → therapeutic LMWH + PHT consult。
- Chest pain(Fig 11):四鑑別軸(ACS / PE / aortic syndrome / other);SCAD 是妊娠 ACS 主因(≥40%),多數 conservative;ASCVD 標準治療;clopidogrel 為首選 P2Y12。
- HDP(Fig 12A/B/C):BP target <140/90(CHAP-supported, I B);severe HTN i.v. labetalol/urapidil/nicardipine;sFlt-1/PlGF 用於 inconclusive;aspirin 預防 high-risk pre-eclampsia;Mg seizure prevention。
- 共通禁忌:ACEi/ARB/ARNI/MRA/SGLT2i/sublingual nifedipine/DOAC 全部禁用。
📖 References
- De Backer J, Haugaa KH, Hasselberg NE, et al. 2025 ESC Guidelines for the management of cardiovascular disease and pregnancy. Eur Heart J 2025;46(43):4462–4568. doi:10.1093/eurheartj/ehaf193
- Tita AT, Szychowski JM, Boggess K, et al. Treatment for Mild Chronic Hypertension during Pregnancy (CHAP). N Engl J Med 2022;386:1781–1792. doi:10.1056/NEJMoa2201295
- Rolnik DL, Wright D, Poon LC, et al. Aspirin versus Placebo in Pregnancies at High Risk for Preterm Preeclampsia (ASPRE). N Engl J Med 2017;377:613–622. doi:10.1056/NEJMoa1704559
- Hayes SN, Kim ESH, Saw J, et al. Spontaneous Coronary Artery Dissection: Current State of the Science (AHA Scientific Statement). Circulation 2018;137:e523-e557.
- Konstantinides SV, Meyer G, Becattini C, et al. 2019 ESC Guidelines for the diagnosis and management of acute pulmonary embolism. Eur Heart J 2020;41:543-603.
- Chan WS, Spencer FA, Ginsberg JS. Anatomic distribution of deep vein thrombosis in pregnancy. CMAJ 2010;182:657-660.
- Stepan H, Hund M, Andraczek T. Combining biomarkers to predict pregnancy complications and redefine preeclampsia (PROGNOSIS Asia). Hypertension 2020;75:918-926.
- Magee LA, von Dadelszen P, Rey E, et al. Less-tight versus tight control of hypertension in pregnancy (CHIPS). N Engl J Med 2015;372:407-417.
本文以教學為目的整理 2025 ESC Guidelines for the management of cardiovascular disease and pregnancy;所有原文 Figure 之版權屬 ESC。商業使用請洽 ESC 取得授權。
